1.1.1 - Kidney Failure Pharmacology Context
Kidney Failure Pharmacology Context
What you'll learn
- Explain how reduced glomerular filtration, uremia, and volume shifts alter pharmacokinetics and pharmacodynamics in transplant candidates.
- Apply a pharmacist decision framework for renal dose adjustment, dialysis-related dosing, and medication safety review.
- Distinguish kidney failure effects from other causes of altered drug exposure that appear in transplant stems.
- Recognize high-yield medication classes that require special handling in advanced kidney disease before kidney transplant.
- Recommend monitoring plans for efficacy, toxicity, and transitions of care in patients with end-stage kidney disease.
- DOMAIN: Clinical decision-making in transplant pharmacotherapy → Subskill: renal function-based dose adjustment in transplant candidates and recipients
- DOMAIN: Therapeutic drug monitoring → Subskill: interpret kidney function, dialysis status, and timing when evaluating medication concentrations
- DOMAIN: Drug interactions and adverse effects → Subskill: identify nephrotoxic, renally cleared, and accumulation-prone medications in kidney failure
- DOMAIN: Medication safety and transitions of care → Subskill: reconcile home medications, OTCs, and dialysis-era regimens during transplant evaluation and peri-transplant transition
- DOMAIN: Organ-specific transplant medication management → Subskill: connect pre-transplant kidney failure physiology to post-transplant immunosuppressant planning
Why it matters
- Kidney failure changes more than serum creatinine; it changes clearance, protein binding, volume status, toxin exposure, and the reliability of drug-response assumptions.
- Board questions often hide the real task inside a transplant scenario: the best answer is not the diagnosis, but the safest medication-related recommendation.
- Many wrong answers are “almost right” except for one renal adjustment issue, one dialysis timing issue, or one nephrotoxic interaction.
- These concepts become the foundation for tacrolimus, valganciclovir, TMP-SMX, antifungal, and antimicrobial dosing throughout the course.
Key Terms & Must-Know Facts
1.1.1.1 Key terms
- CKD: Chronic kidney disease with persistent structural or functional kidney abnormality.
- ESKD: End-stage kidney disease requiring dialysis or kidney replacement consideration.
- GFR: Best overall index of kidney filtration capacity for many dosing decisions.
- Creatinine clearance: Estimate used in many drug labels and historic dose recommendations.
- Uremia: Clinical syndrome of retained solutes affecting organ function and drug response.
- Protein binding: Fraction of drug bound to albumin or other proteins; unbound drug is pharmacologically active.
- Volume of distribution: Apparent distribution of drug into body compartments; altered by edema, ascites, obesity, and muscle mass.
- Dialyzability: Likelihood a drug is removed by dialysis, influenced by molecular size, protein binding, water solubility, and \(V_d\).
- Nephrotoxin: Drug that can worsen kidney injury or accelerate residual function loss.
- Residual renal function: Remaining kidney clearance in dialysis patients; may still matter for dosing.
- Renally cleared metabolite: Active or toxic metabolite that accumulates when kidney function falls.
- Preemptive transplant candidate: Candidate approaching kidney transplant before dialysis initiation.
- Therapeutic drug monitoring: Use of measured concentrations plus timing and clinical context to guide dosing.
1.1.1.2 Must-know facts
- Serum creatinine alone can mislead in low muscle mass, sarcopenia, amputation, cachexia, or fluid overload.
- Many exam stems test whether you know that eGFR and Cockcroft-Gault are not interchangeable for every drug label.
- Dialysis does not automatically “fix” medication accumulation; some drugs are barely removed.
- Uremia can increase bleeding risk and alter platelet function independent of anticoagulant use.
- Hypoalbuminemia can increase free concentrations of highly protein-bound drugs.
- Avoid reflexively holding all renally cleared drugs; some require dose reduction, timing adjustment, or monitoring rather than discontinuation.
- In transplant candidates, medication safety includes preserving residual kidney function and avoiding avoidable nephrotoxins.
- A “normal” creatinine after transplantation may not mean normal drug handling if delayed graft function or dialysis persists.
Core content
Exam takeaway: Use this sequence to decide whether the dosing problem is filtration, dialysis removal, protein binding, or nephrotoxicity.
flowchart TD
A[Medication question in kidney failure] --> B{What drives exposure?}
B --> C[Renal clearance]
B --> D[Dialysis removal]
B --> E[Protein binding and uremia]
B --> F[Nephrotoxic potential]
C --> G[Adjust dose or interval]
D --> H[Time dose before or after dialysis]
E --> I[Interpret total vs free effect carefully]
F --> J[Choose safer alternative and monitor] Exam takeaway: The key stem clue is whether the drug is removed by dialysis and whether the dose should be scheduled after the session.
flowchart TD
A[Patient on dialysis] --> B{Is drug significantly dialyzable?}
B -->|Yes| C[Consider post-dialysis supplemental dose]
B -->|No| D[Dose by residual renal function and standard interval]
C --> E{Intermittent HD today?}
E -->|Yes| F[Schedule after session]
E -->|No| G[Use non-HD plan]
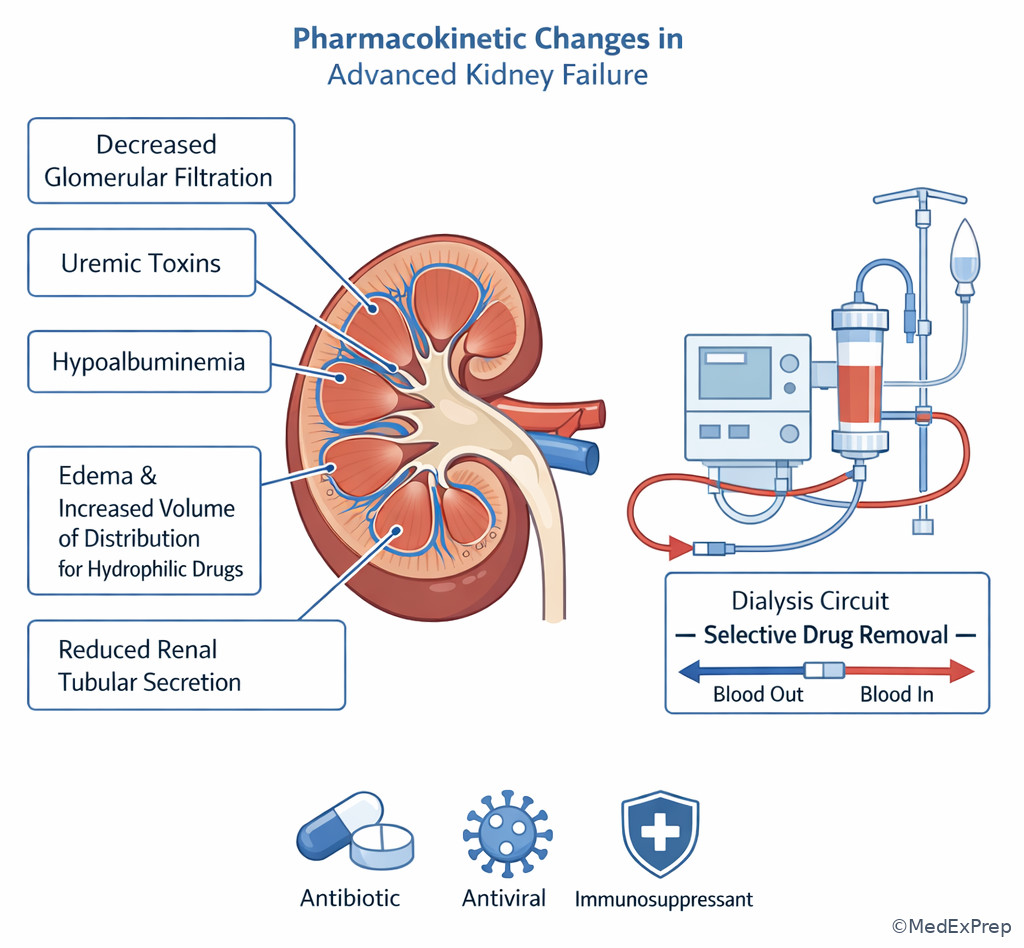
D --> H[Monitor accumulation and efficacy] Exam takeaway: Visualize how low GFR, edema, and hypoalbuminemia shift clearance, distribution, and free drug exposure.
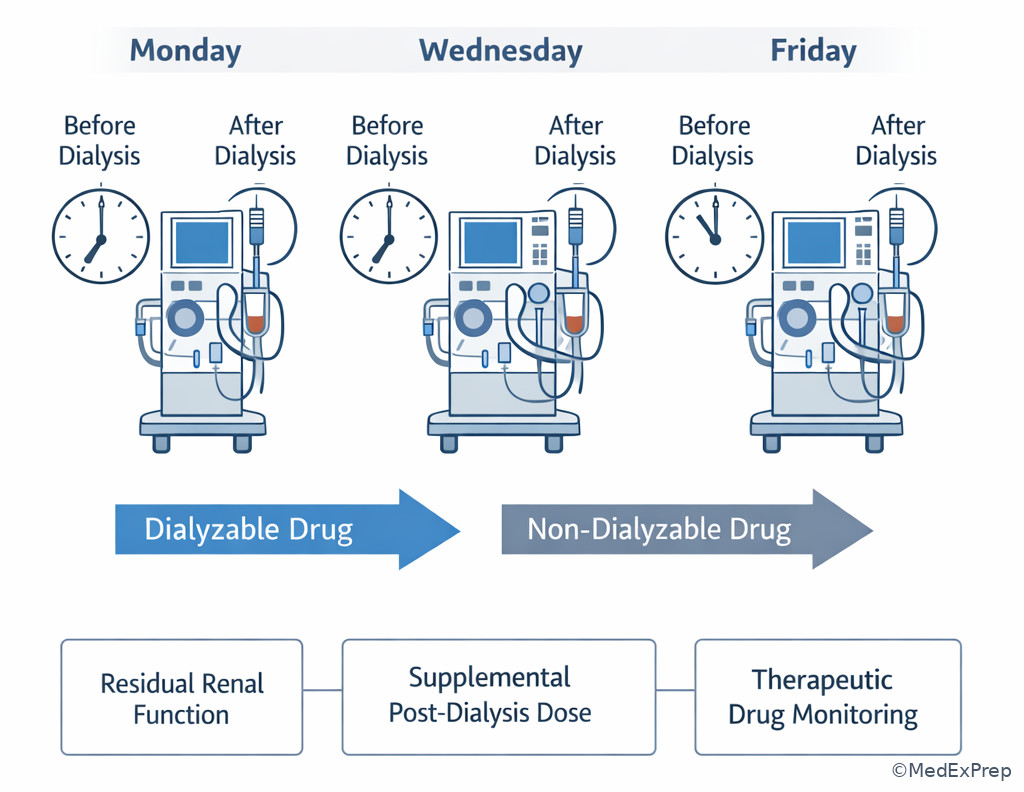
Exam takeaway: When a stem gives a dialysis schedule, use it to decide whether the dose belongs before, after, or independent of the session.
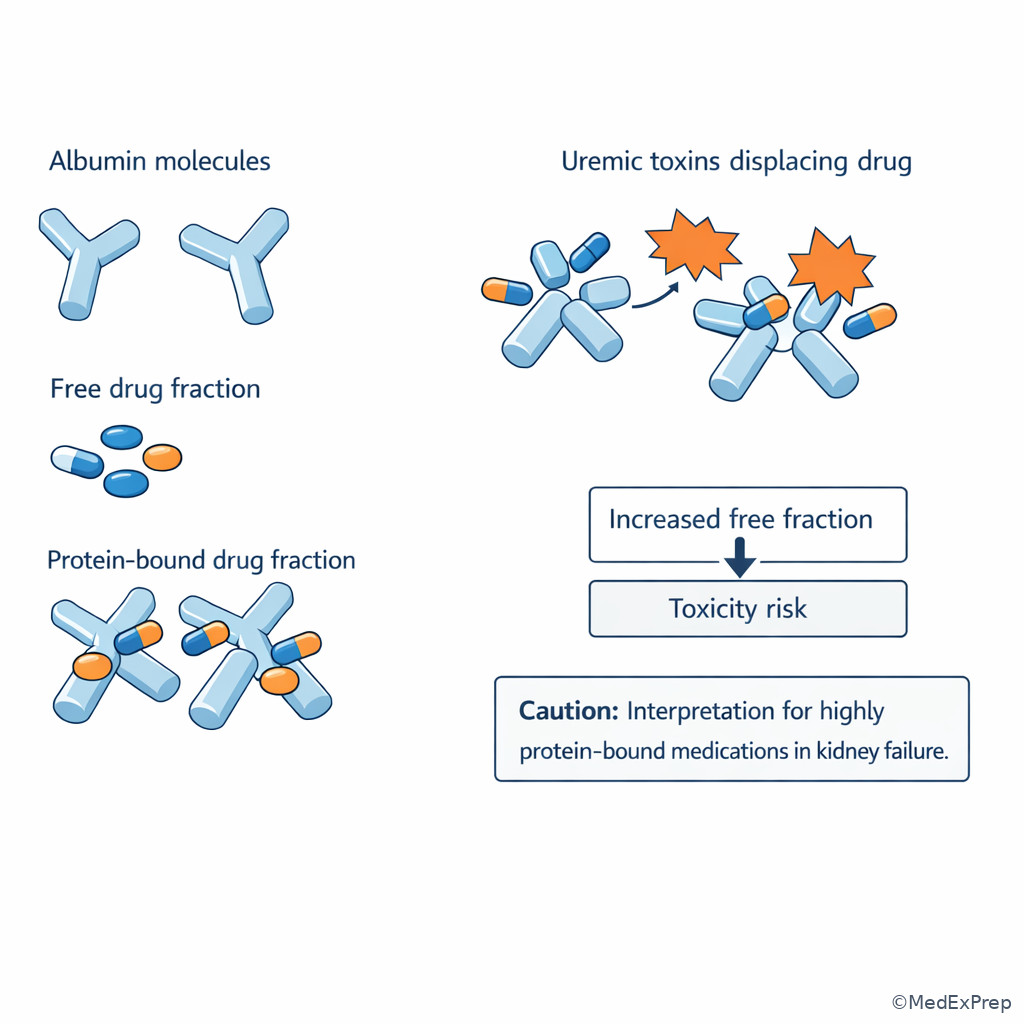
Exam takeaway: In advanced kidney disease, altered protein binding can make total concentration data less reliable than the clinical picture.
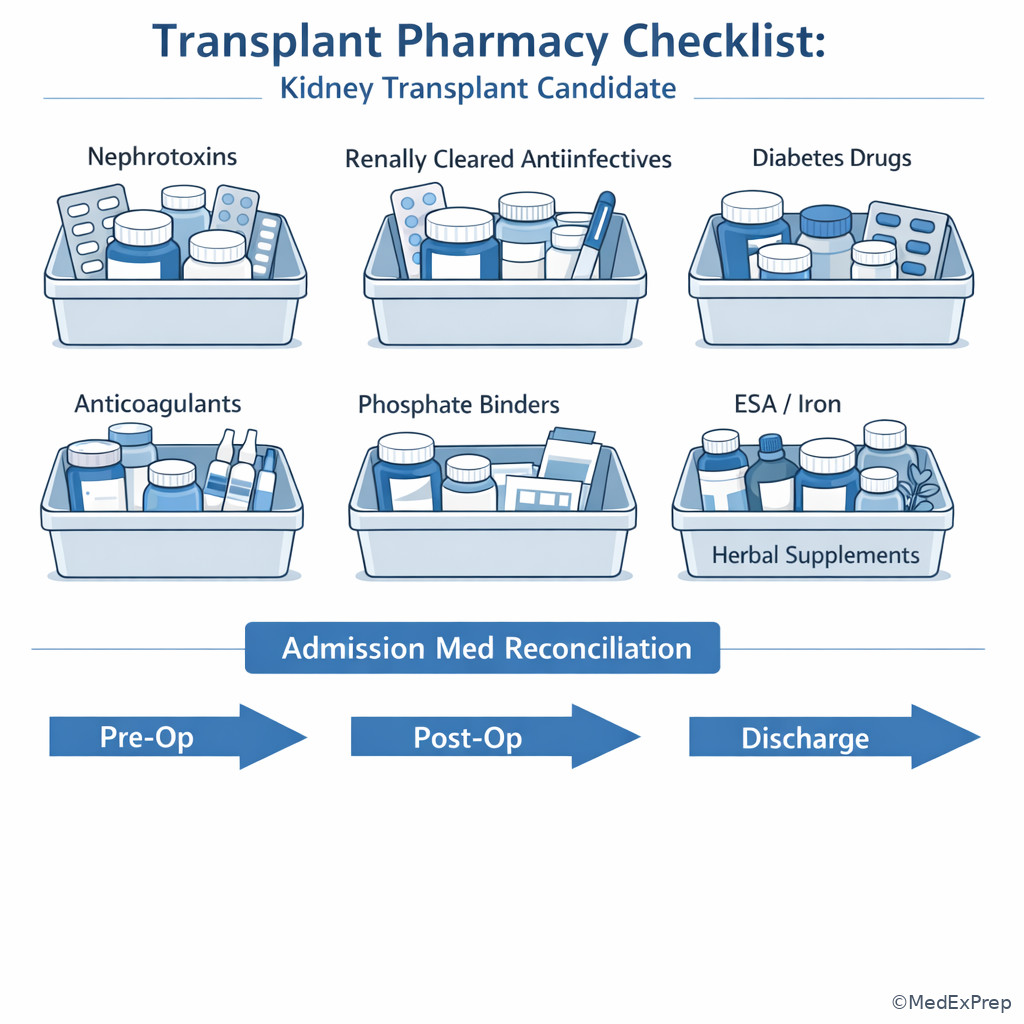
Exam takeaway: In pre-kidney transplant patients, the safest pharmacist action is usually to reconcile nephrotoxins, renally cleared drugs, and dialysis-era medications before surgery.
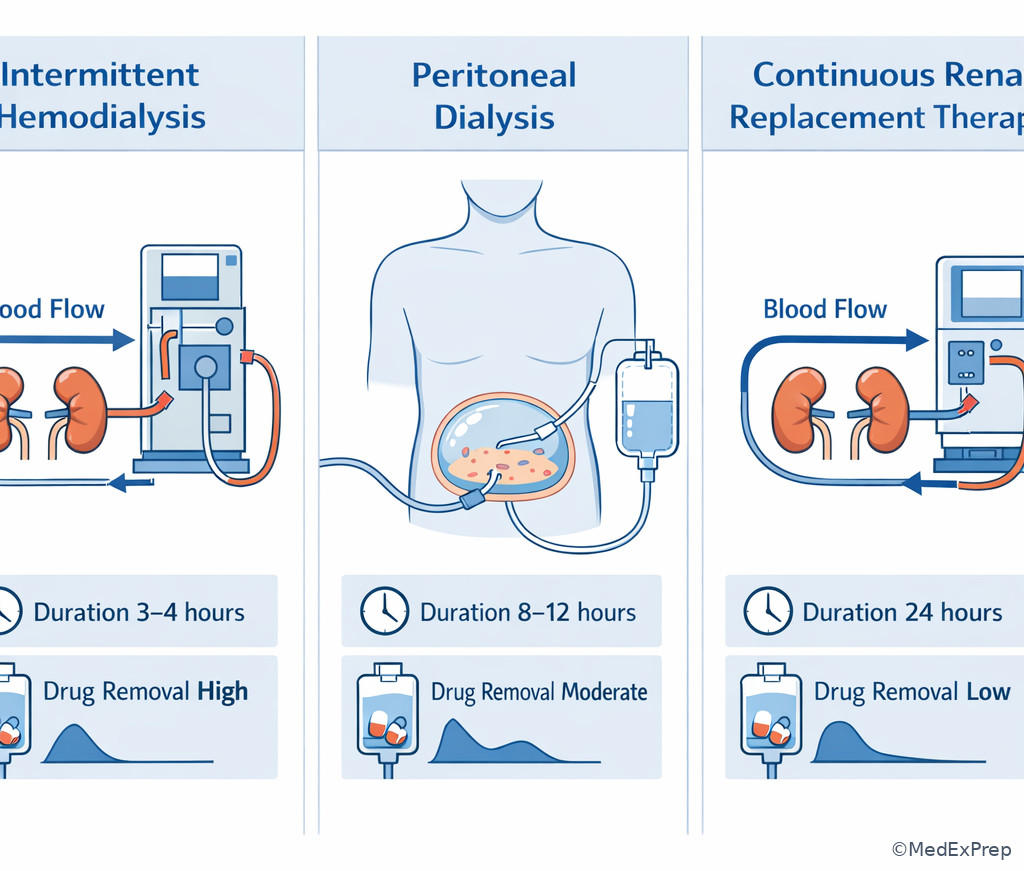
Exam takeaway: Different dialysis modalities create different assumptions about drug removal, so do not apply intermittent hemodialysis rules to all patients.
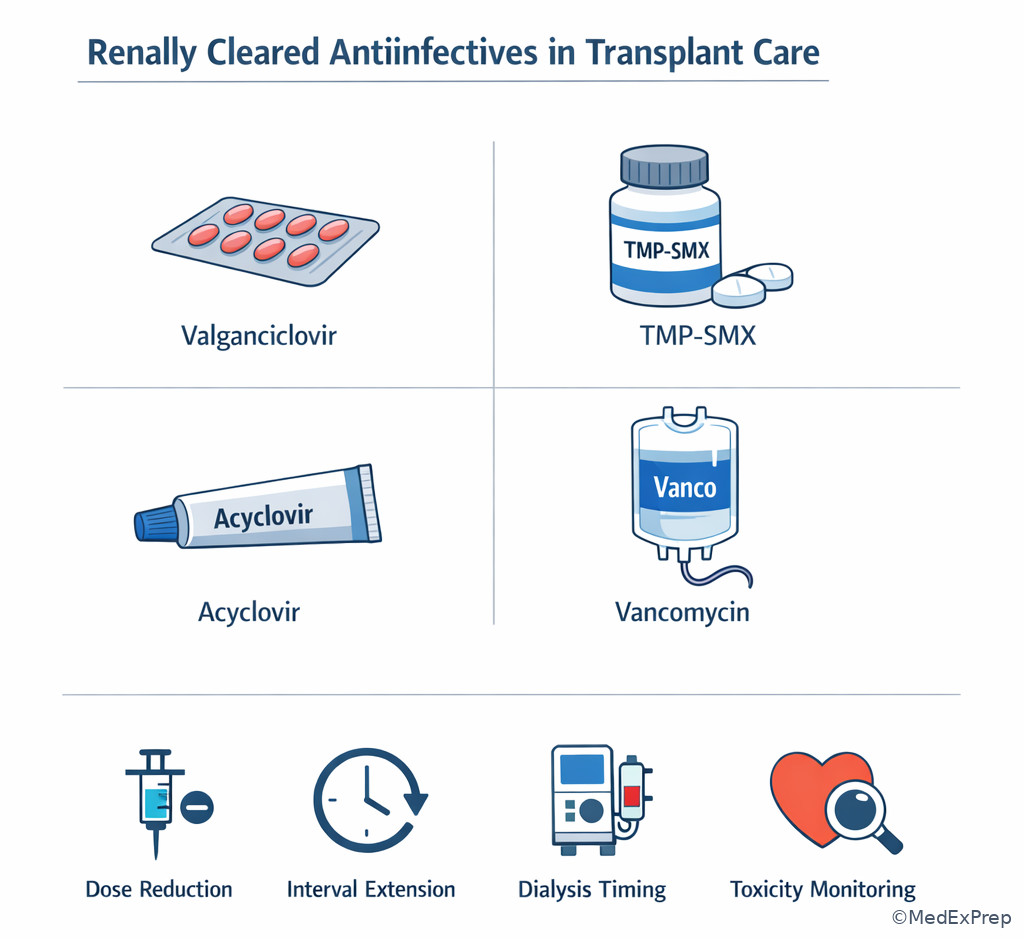
Exam takeaway: Antiinfectives are frequent exam targets because efficacy failure and toxicity can both result from incorrect renal adjustment.
Exam takeaway: When kidney function worsens, separate hemodynamic effects, intrinsic nephrotoxicity, and exposure-related injury before changing therapy.
flowchart LR
A[Creatinine rises] --> B[Volume depletion or low perfusion]
A --> C[Drug nephrotoxicity]
A --> D[Obstruction or other non-drug issue]
C --> E[CNI effect]
C --> F[NSAID]
C --> G[ACEI or ARB hemodynamic change]
C --> H[Antimicrobial toxicity]
B --> I[Review BP, diuretics, intake]
D --> J[Escalate for non-pharmacist evaluation]
1.1.1.3 Foundational PK changes in kidney failure
A Explanation
The decision conflict in early kidney failure questions is usually this: should you treat the patient as if only renal clearance changed, or should you also account for altered distribution and protein binding? The single resolving rule is to first identify whether the drug is primarily renally eliminated, highly hydrophilic, or highly protein bound. Reduced GFR slows elimination of many parent drugs and metabolites, but that is only part of the exposure story. Edema can expand the volume of distribution of water-soluble drugs, delaying attainment of target concentrations and sometimes justifying a usual loading dose even when the maintenance dose must be reduced. Uremia and hypoalbuminemia can increase the free fraction of highly protein-bound drugs, making “total level” interpretation less intuitive. See Fig 1 and Fig 5.
WHY THIS IS TESTED: Board items often present a low eGFR and ask for the most appropriate next step, but the correct answer depends on whether the medication problem is under-clearance, altered free drug exposure, or a distribution issue. Choose the standard loading dose for serious infection when rapid target attainment matters; reject automatic maintenance-dose equivalence. Choose closer toxicity monitoring when the drug is highly protein bound and the patient has severe uremia; reject blind reliance on total concentrations or standard adult dosing.
B Worked example
A 59-year-old man undergoing kidney transplant evaluation has diabetic nephropathy, heart failure with preserved ejection fraction, and obesity. He is admitted with pneumonia and is prescribed a renally cleared IV antibiotic. His serum creatinine is 6.8 mg/dL, albumin 2.6 g/dL, and he has marked peripheral edema. A team member suggests reducing both the loading dose and the maintenance dose because “his kidneys do not work.” A mildly elevated AST appears in the stem as a distractor.
Reasoning chain: Identify the task: choose the safest initial dosing strategy. Extract key facts: severe kidney failure, edema, hypoalbuminemia, serious infection, renally cleared hydrophilic drug. Apply the rule: serious infection still needs adequate early exposure, so the loading dose is often preserved; maintenance is reduced or interval extended because clearance is impaired. Eliminate distractors: the mildly elevated AST is tempting because hepatic dysfunction can also alter exposure, but this stem is driven by renal clearance and distribution. Verify: recommend a usual loading dose if appropriate for the agent, adjust maintenance by kidney function, and monitor drug-specific efficacy and toxicity.
C Exam trap
D Checkpoint
Question: A pre-kidney transplant candidate with ESKD, anasarca, and a severe bacterial infection needs a hydrophilic renally cleared antibiotic. What is the most appropriate dosing principle?
- Reduce both the loading dose and maintenance dose because renal clearance is reduced.
- Use a standard loading dose, then reduce maintenance exposure based on renal function.
- Avoid the drug entirely because edema makes dosing impossible.
- Keep the maintenance dose unchanged and only prolong therapy duration.
- A: Tempting because low kidney function does require maintenance adjustment, but wrong because loading dose is based more on distribution and target attainment.
- B: Tempting because it seems aggressive, and correct because edema may expand distribution while poor renal clearance requires lower maintenance exposure.
- C: Tempting when edema creates uncertainty, but wrong because many such drugs remain usable with adjusted maintenance dosing and monitoring.
- D: Tempting if one thinks infection severity requires “full treatment,” but wrong because unchanged maintenance in severe kidney failure risks accumulation and toxicity.
1.1.1.4 Estimating renal function for medication decisions
A Explanation
The decision conflict here is whether to use serum creatinine at face value or interpret kidney function through the lens of the dosing method specified for the medication. The single rule that resolves most board stems is: use the renal function estimate that best matches the drug’s labeling or validated dosing data, while recognizing clinical situations where creatinine-based estimates are unreliable. Cockcroft-Gault historically underpins many dose recommendations, while eGFR is commonly reported by the laboratory and useful for CKD staging. In sarcopenia, cachexia, amputation, advanced age, cirrhosis, or fluid overload, serum creatinine can underestimate the severity of kidney dysfunction because creatinine generation is low. In those stems, the safer pharmacist action is to question apparently “acceptable” dosing, not to celebrate a deceptively low creatinine. See Fig 3.
WHY THIS IS TESTED: Questions often tempt you to anchor on a creatinine value instead of the patient’s physiology. Choose cautious interpretation when the patient has low muscle mass or acute changes; reject full-dose renally cleared therapy based only on an apparently modest serum creatinine. If the medication label uses creatinine clearance thresholds, pick the answer that aligns with those thresholds unless the stem gives a reason that creatinine is unreliable.
B Worked example
A 71-year-old woman listed for kidney transplant has long-standing hypertension, sarcopenia, and a below-knee amputation. She is receiving valganciclovir prophylaxis planning in a simulated board-style case. Her serum creatinine is 1.1 mg/dL, weight is low, and she has little muscle mass. A distractor note says she “looks clinically well.”
Reasoning chain: Identify the task: determine whether the apparent creatinine supports standard dosing. Extract key facts: older age, low muscle mass, amputation, transplant candidate, renally cleared antiviral. Apply the rule: creatinine-based estimates may overstate function in low creatinine production states, so aggressive full-dose interpretation is unsafe. Eliminate distractors: “clinically well” does not rescue an unreliable renal estimate. Verify: recommend using the drug’s validated renal dosing framework with conservative interpretation and close monitoring rather than assuming preserved kidney function.
C Exam trap
D Checkpoint
Question: Which patient most requires caution when using serum creatinine alone to guide dosing of a renally cleared transplant medication?
- A muscular 35-year-old on no dialysis with stable creatinine and unchanged weight.
- A 68-year-old cachectic patient with low muscle mass and major fluid overload.
- A 44-year-old with stable CKD and serial outpatient renal values over 6 months.
- A 56-year-old with obesity and no recent change in renal status.
- A: Tempting because all renal dosing requires thought, but wrong because the creatinine is more likely to reflect production accurately in this setting.
- B: Tempting because multiple confounders are present, and correct because cachexia and fluid overload can make creatinine deceptively reassuring.
- C: Tempting because CKD itself affects dosing, but wrong because the issue here is reliability of creatinine, not merely chronic impairment.
- D: Tempting because body size complicates equations, but wrong because low muscle mass and fluid overload are stronger misleading factors in this context.
- The most common reason serum creatinine misleads in frail patients is reduced creatinine production.
- True or False: A near-normal serum creatinine always means standard renal dosing is appropriate. False.
- Name the 3 key confounders: low muscle mass, fluid overload, recent acute change.
1.1.1.5 Dialysis and medication timing
A Explanation
The core conflict in dialysis stems is whether the medication should be dose-reduced, post-dialysis supplemented, or left unchanged by the session. The single resolving rule is to determine dialyzability first. Drugs that are small, water soluble, have low protein binding, and low volume of distribution are more likely to be removed by intermittent hemodialysis. If significantly removed, the best medication-related action is often to dose after dialysis or provide a supplemental post-dialysis dose. If poorly dialyzable, dosing may be based more on residual kidney function and the usual interval strategy. Do not assume every drug needs a post-HD dose. See Fig 2 and Fig 4.
WHY THIS IS TESTED: The exam loves schedule details: Monday/Wednesday/Friday hemodialysis, peritoneal dialysis at home, or delayed graft function with ongoing dialysis after transplant. Choose the answer that uses the modality and drug properties; reject “dose after dialysis” as a reflex. Also remember that residual kidney function still matters, especially in peritoneal dialysis or earlier ESKD, and that continuous therapies are not interchangeable with intermittent hemodialysis for dosing logic.
B Worked example
A 48-year-old man on Monday/Wednesday/Friday hemodialysis is admitted for transplant workup with CMV risk discussion and receives a renally cleared antimicrobial in a case vignette. He also has atrial fibrillation and gout. The stem mentions a mildly prolonged QT interval to tempt focus away from the true issue. The team asks whether the dose should be administered at 0800, but dialysis starts at 0900.
Reasoning chain: Identify the task: optimize timing around dialysis. Extract key facts: intermittent HD today, medication is significantly dialyzable, and efficacy depends on preserving exposure. Apply the rule: avoid dosing immediately before the session if the drug will be removed; schedule after HD or provide a supplemental post-HD dose depending on the agent. Eliminate distractors: atrial fibrillation and gout are real comorbidities but do not determine this dosing question. Verify: document dialysis-aware administration timing and monitoring.
C Exam trap
D Checkpoint
Question: A medication is low protein bound, water soluble, and has a low volume of distribution. A patient receives intermittent hemodialysis at 1 PM. What is the most appropriate general dosing principle?
- Give the dose immediately before dialysis to maximize early peak.
- Schedule the dose after dialysis because the session is likely to remove the drug.
- Stop the medication because any dialyzable drug is ineffective in dialysis.
- Ignore dialysis timing and use only serum creatinine to guide dosing.
- A: Tempting because early dosing seems efficient, but wrong because a substantially dialyzable drug may be removed before meaningful exposure is maintained.
- B: Tempting because it complicates scheduling, and correct because the described PK features suggest dialysis removal.
- C: Tempting if one overestimates dialysis impact, but wrong because many dialyzable drugs remain appropriate when timing is adjusted.
- D: Tempting because serum creatinine matters in CKD, but wrong because dialysis timing is the key discriminator in this case.
1.1.1.6 High-risk medication classes in kidney failure
A Explanation
The decision conflict in medication-review stems is whether a drug is dangerous because it worsens kidney function, accumulates to toxicity, or both. The single rule is to classify each medication by one of three pathways: nephrotoxic effect, renal accumulation, or accumulation of an active/toxic metabolite. NSAIDs, IV contrast-related scenarios, and some antiinfectives are frequent nephrotoxic clues. Gabapentinoids, baclofen, morphine metabolites, and many antiinfectives are accumulation traps. TMP-SMX, valganciclovir, acyclovir, vancomycin, and fluconazole frequently appear in transplant-relevant questions because underdosing risks failure while overdosing risks toxicity. In pre-transplant patients, the safest pharmacist role is to reconcile, recommend adjustment, and monitor; not every agent should be stopped, but every high-risk agent should be reconsidered. See Fig 6.
WHY THIS IS TESTED: Board questions often hide one tempting medication among many. Choose the agent that best preserves safety without sacrificing required prophylaxis or treatment. Reject answers that remove essential prophylaxis entirely when dose adjustment would solve the problem. Also reject complacency about “chronic home meds” that were appropriate years ago but are now unsafe in advanced kidney failure.
B Worked example
A 63-year-old woman with ESKD on peritoneal dialysis is being prepared for transplant evaluation. Her home medication list includes ibuprofen 600 mg three times daily, baclofen 10 mg three times daily, gabapentin 300 mg three times daily, and TMP-SMX single-strength daily from a prior prophylaxis plan. She also has insomnia and restless legs, which are distracting but nondecisive details.
Reasoning chain: Identify the task: prioritize medication safety concerns. Extract key facts: dialysis-dependent kidney failure, multiple renally cleared or neurotoxic accumulation-prone agents, chronic NSAID use. Apply the rule: ibuprofen threatens residual renal/hemodynamic stability; baclofen and gabapentin can accumulate and cause neurotoxicity; TMP-SMX may remain appropriate but requires renal-aware dosing depending on indication and residual function. Eliminate distractors: insomnia does not explain away medication risk. Verify: recommend stopping or avoiding unnecessary nephrotoxins, adjusting renally cleared neuroactive agents, and confirming prophylaxis indication and dose.
C Exam trap
D Checkpoint
Question: In an ESKD patient awaiting transplant, which medication category most strongly signals a need to distinguish nephrotoxicity from accumulation toxicity rather than simply “renal dose adjust everything”?
- NSAIDs and baclofen
- Topical emollients and saline nasal spray
- A multivitamin and calcium carbonate alone
- A stable proton pump inhibitor and stool softener
- A: Tempting because both are common, and correct because NSAIDs can worsen kidney injury while baclofen can accumulate and cause neurotoxicity.
- B: Tempting because all meds deserve review, but wrong because these agents are not the classic kidney failure danger pattern here.
- C: Tempting because supplements can matter in transplant, but wrong because the stem asks for the strongest nephrotoxicity-versus-accumulation contrast.
- D: Tempting because chronic meds may require reassessment, but wrong because they are less characteristic high-risk renal traps than the correct pair.
- The most common anti-inflammatory nephrotoxin tested in home med lists is an NSAID.
- True or False: All prophylactic antiinfectives should be stopped in dialysis patients. False.
- Name 3 accumulation-prone neuroactive drugs often needing renal caution: baclofen, gabapentin, pregabalin.
1.1.1.7 Pre-transplant to post-transplant medication transition in kidney failure
A Explanation
The integration conflict is whether to carry dialysis-era medication assumptions straight into the peri-transplant period. The single rule is: once transplantation occurs, every chronic kidney failure medication and every renal dose adjustment must be actively reverified against graft function trajectory, delayed graft function status, and immediate post-operative orders. Some pre-transplant agents become unnecessary, such as certain phosphate binders or dialysis-timed regimens if graft function is adequate. Other medications remain necessary but require rapid dose re-escalation as kidney function improves. The transplant pharmacist’s safest move is a structured reconciliation: identify what was used because of ESKD, what was reduced only because of ESKD, and what must now be retimed around new immunosuppressive and prophylactic therapy. Delayed graft function complicates this by creating a “post-transplant patient who still behaves pharmacologically like a dialysis patient” for some drugs.
WHY THIS IS TESTED: BCTXP stems frequently ask for the best medication-related action after kidney transplant when creatinine is changing daily. Choose re-evaluation of antiviral, antibacterial, antifungal, antidiabetic, and antihypertensive dosing; reject autopilot continuation of pre-transplant reduced doses or dialysis-era schedules. Conversely, reject immediate full-dose escalation if delayed graft function or ongoing dialysis persists.
B Worked example
A 52-year-old man receives a deceased donor kidney transplant. Before surgery he was on hemodialysis, sevelamer, epoetin alfa, valganciclovir planning at a dialysis-adjusted dose, and gabapentin 100 mg nightly. On post-operative day 2, urine output improves and creatinine falls quickly, but he still has mild edema. A distractor note mentions a healing surgical drain.
Reasoning chain: Identify the task: choose the best medication-related transition action. Extract key facts: pre-transplant dialysis medications, improving graft function, renally cleared prophylaxis, and a low pre-transplant gabapentin dose that may become subtherapeutic or still unnecessary depending on indication. Apply the rule: reassess every renal adjustment; some ESKD-supportive drugs may stop, while prophylaxis may need upward retitration as kidney function improves. Eliminate distractors: the surgical drain does not govern pharmacokinetic dosing. Verify: recommend active med reconciliation rather than blind continuation of dialysis-era doses.
C Exam trap
D Checkpoint
Question: A newly transplanted kidney recipient had several medications reduced only because of dialysis-dependent kidney failure. What is the most appropriate pharmacist recommendation when graft function begins improving over the first 48–72 hours?
- Continue all dialysis-era dose reductions unchanged until one month after transplant.
- Reassess each renal dose adjustment against current graft function and ongoing dialysis status.
- Immediately convert all medications to normal renal function doses regardless of urine output.
- Focus only on tacrolimus because non-immunosuppressant medications are less urgent.
- A: Tempting because conservative dosing feels safe, but wrong because underexposure of prophylaxis or treatment drugs may occur as renal function improves.
- B: Tempting because it requires more work, and correct because post-transplant kidney function is dynamic and medication adjustments must track it.
- C: Tempting because a successful transplant suggests recovery, but wrong because delayed graft function or partial recovery can still limit clearance.
- D: Tempting because tacrolimus is high stakes, but wrong because prophylaxis, antimicrobials, diabetes therapies, and home medications also require active reassessment.
Exam Traps & Differentiators
| Stem clue | Think | Reject | Why the reject option is tempting |
|---|---|---|---|
| Severe infection + edema + low GFR | Usual loading dose, renal-adjusted maintenance | Reduce loading dose automatically | “Bad kidneys mean lower dose” is only half the PK story |
| Sarcopenia, amputation, cachexia, or fluid overload | Creatinine may overestimate function | Standard dosing from serum creatinine alone | The lab number may look reassuring |
| Intermittent HD soon after scheduled dose | Assess dialyzability and dose after HD if removed | Routine pre-HD administration | Consistency of schedule seems convenient |
| NSAID on home med list in ESKD | Reassess for avoidable nephrotoxicity | Continue because residual function is already low | Learners assume “there is no kidney function left to lose” |
| Rapidly improving kidney function after transplant | Retitrate renally cleared drugs | Keep dialysis-era doses until first clinic visit | Conservative dosing feels safer than underexposure sounds |
1.1.1.8 Looks similar but isn't
| Look-alike pair | Discriminator | What the pharmacist should do |
|---|---|---|
| High creatinine vs misleadingly normal creatinine in cachexia | Muscle mass and creatinine production | Question the estimate; use validated dosing method and clinical judgment |
| Dialysis patient vs dialyzable drug | Drug properties and modality, not dialysis label alone | Check whether the session removes enough drug to matter |
| Nephrotoxicity vs drug accumulation | Injury mechanism versus reduced clearance | Stop/avoid the nephrotoxin or adjust the accumulation-prone drug appropriately |
| Post-transplant improving function vs delayed graft function | Urine output, creatinine trend, ongoing dialysis | Retitrate only to the degree graft function has actually recovered |
1.1.1.9 If the stem says ___, think ___
- If the stem says “anasarca”, think hydrophilic drug distribution may be larger; loading dose logic may differ from maintenance logic.
- If the stem says “frail, cachectic, amputee”, think serum creatinine may be falsely reassuring.
- If the stem says “Monday/Wednesday/Friday hemodialysis”, think timing around intermittent HD may be the actual medication question.
- If the stem says “home ibuprofen”, think avoidable nephrotoxicity and medication reconciliation.
- If the stem says “post-op day 2, urine output rising”, think reassess every renal adjustment now.
- If the stem says “delayed graft function with dialysis”, think do not jump to normal post-transplant dosing.
Tables
| Key fact / value | Why it matters in exam stems | Best pharmacist response |
|---|---|---|
| Serum creatinine can be misleading in low muscle mass | Apparent renal function may be overestimated | Use validated dosing framework and interpret conservatively |
| Loading dose depends mainly on target and \(V_d\) | Edematous ESKD patient may still need full loading dose | Do not automatically reduce the loading dose |
| Maintenance dose depends mainly on clearance | Severe CKD increases accumulation risk | Reduce dose, extend interval, or both |
| Dialysis removal depends on protein binding and \(V_d\) | Some doses should be given after HD | Check dialyzability before scheduling |
| Uremia alters protein binding and platelet function | Total concentrations and bleeding risk may mislead | Interpret clinical effect, free fraction concerns, and safety context |
| Post-transplant graft recovery can be rapid | Dialysis-era doses may become subtherapeutic | Reassess daily in the immediate post-op period |
| Comparison | Primary concern | Typical action | High-yield example |
|---|---|---|---|
| Nephrotoxic drug | Worsens kidney injury or perfusion | Avoid, stop, or substitute if benefit is low | NSAID |
| Renally cleared parent drug | Accumulation from reduced clearance | Dose reduce or extend interval | Fluconazole |
| Renally cleared active or toxic metabolite | Neurotoxicity or prolonged effect despite parent dosing focus | Avoid or use much more cautiously | Morphine metabolites, baclofen |
| Highly dialyzable drug | Drug removal during HD session | Schedule after dialysis or replace | Selected water-soluble antimicrobials |
| Poorly dialyzable drug | Dialysis session has little dosing impact | Adjust for residual function rather than timing alone | Highly protein-bound agents |
| Differential / classification pattern | Single best clue | Likely medication problem | Most defensible pharmacist action |
|---|---|---|---|
| Cachectic patient with “normal” creatinine | Low muscle mass | Overestimated renal function | Clarify dosing method and avoid reflex standard dosing |
| Drug scheduled just before HD | Low protein binding, low \(V_d\) | Dialysis removal | Retime after HD or add replacement strategy |
| ESKD patient with confusion on baclofen | Renally cleared neuroactive agent | Accumulation toxicity | Recommend avoidance or major adjustment; monitor neurostatus |
| Rising urine output after transplant | Rapidly changing clearance | Outdated renal dose reduction | Reassess all renally adjusted medications daily |
| Home NSAID in transplant candidate | Avoidable nephrotoxin | Medication-related kidney injury risk | Recommend discontinuation or safer alternative |
Algorithm / Approach
Rapid Review
- Loading dose in kidney failure → tied to target concentration and \(V_d\), not just eGFR
- Maintenance dose in kidney failure → tied to clearance and accumulation risk
- Sarcopenic patient with “good” creatinine → renal function may be overestimated
- Intermittent HD timing clue → assess dialyzability before scheduling
- Low protein binding + low \(V_d\) → more likely HD removal
- Highly protein-bound drug in uremia → total concentration may mislead
- NSAID on med list → think avoidable nephrotoxic exposure
- Baclofen in ESKD → think neurotoxicity from accumulation
- Pre-transplant dialysis dose after graft recovery → risk of underexposure
- Delayed graft function after transplant → patient may still require kidney failure dosing logic
- Residual renal function on dialysis → still relevant for some dosing decisions
- Renally cleared prophylaxis drug → do not stop reflexively; adjust deliberately
- Normal-looking creatinine in amputee → not proof of normal filtration
- Board-style best action → reconcile, recommend, monitor, and clarify; stay within pharmacist scope
Self-check quiz
1.1.1.10 Question 1
A 61-year-old man with ESKD on hemodialysis, hypertension, and edema is started on a hydrophilic renally cleared IV antibiotic for pneumonia. The pharmacist is asked for the most appropriate initial dosing principle. Which recommendation is best?
- Reduce both the loading dose and maintenance dose because the serum creatinine is markedly elevated.
- Use a standard loading dose, then adjust maintenance exposure for renal function and dialysis status.
- Use the standard maintenance dose but hold all future doses on dialysis days.
- Avoid the antibiotic because renally cleared agents are ineffective in dialysis patients.
1.1.1.11 Question 2
A 73-year-old woman listed for kidney transplant has sarcopenia, a low body weight, and serum creatinine of 1.0 mg/dL while receiving a renally cleared antiviral plan. Which factor most requires immediate clarification before standard-dose use?
- Low muscle mass making serum creatinine falsely reassuring
- Age above 70 years alone
- Female sex alone
- History of controlled hypothyroidism
1.1.1.12 Question 3
A 49-year-old kidney transplant candidate on Monday/Wednesday/Friday hemodialysis has diabetes and atrial fibrillation. A low protein-bound, water-soluble antimicrobial is scheduled for 8 AM, and dialysis begins at 9 AM. Which pharmacist recommendation is the most appropriate next step?
- Administer the dose at 8 AM as scheduled because early peak matters most
- Move the dose to after dialysis because the session is likely to remove a substantial amount
- Double the pre-dialysis dose to compensate for removal
- Cancel the medication and switch to a hepatically cleared agent regardless of indication
1.1.1.13 Question 4
A 66-year-old woman with ESKD on peritoneal dialysis, neuropathy, and osteoarthritis presents for transplant evaluation. Home medications include ibuprofen 600 mg by mouth three times daily, baclofen 10 mg by mouth three times daily, gabapentin 300 mg by mouth three times daily, and omeprazole 20 mg daily. Which medication-related problem is most important for the pharmacist to prioritize?
- Continue the regimen because all doses are chronic and therefore tolerated
- Identify NSAID nephrotoxicity risk and accumulation toxicity risk from baclofen and gabapentin
- Only discontinue omeprazole because it has the highest renal toxicity risk
- Increase gabapentin because dialysis patients often need more symptom control
1.1.1.14 Question 5
A 54-year-old man receives a deceased donor kidney transplant after years of hemodialysis. On post-operative day 2, urine output increases and serum creatinine falls from 8.1 to 3.2 mg/dL. He is receiving tacrolimus, mycophenolate, prednisone, and a renally adjusted prophylactic antiviral. Which recommendation is the best medication-related action?
- Continue all dialysis-era renal dose reductions unchanged until discharge
- Reassess each renally adjusted medication daily as graft function changes
- Return all medications immediately to normal renal function doses
- Ignore non-immunosuppressant doses until the tacrolimus trough is stable
1.1.1.15 Question 6
A 58-year-old kidney transplant candidate with diabetic nephropathy, severe edema, and albumin 2.5 g/dL is admitted with sepsis. A renally cleared hydrophilic antibiotic is ordered. One resident recommends reducing the loading dose because of kidney failure; another recommends a standard loading dose with reduced maintenance dosing. Which option is the most appropriate pharmacist recommendation?
- Standard loading dose, then renal-adjusted maintenance dosing with efficacy and toxicity monitoring
- Reduced loading dose and reduced maintenance dosing because both depend on GFR
- Reduced loading dose only, then standard maintenance because infection is severe
- Standard loading and standard maintenance because edema dilutes the drug
1.1.1.16 Question 7
A 70-year-old cachectic man with an above-knee amputation, CKD stage 5, and poor oral intake is being considered for valganciclovir after transplant-related viral risk assessment. His serum creatinine is 1.1 mg/dL, and a trainee recommends standard dosing because the value appears near normal. Which pharmacist response is most defensible?
- Accept standard dosing because the serum creatinine is not elevated
- Recommend conservative interpretation of renal function because low creatinine production may overestimate clearance
- Use standard dosing but monitor only if leukopenia develops
- Avoid all antiviral prophylaxis because renal function is uncertain
1.1.1.17 Question 8
A 47-year-old man undergoes kidney transplant but has delayed graft function and requires intermittent hemodialysis on post-operative day 3. He is receiving tacrolimus, mycophenolate, prednisone, and a renally cleared antiinfective that is substantially removed by hemodialysis. Which recommendation is the most appropriate?
- Convert all renally adjusted medications to normal kidney function doses because the transplant has occurred
- Continue pre-transplant dialysis-based timing logic for the dialyzable antiinfective until graft function actually recovers
- Hold the antiinfective completely because immunosuppression is the higher priority
- Ignore the dialysis session because tacrolimus dosing is the only transplant medication timing issue
Answer key
1.1.1.18 Question 1: B
- A: Tempting because severe kidney failure does require maintenance adjustment. Incorrect for this scenario because loading dose is driven mainly by target attainment and distribution, especially in edema; the single clue is severe infection in an edematous patient. Supported by pharmacokinetic principles in DiPiro and standard antimicrobial dosing references.
- B: Tempting because it seems more aggressive, but correct because hydrophilic drugs in edematous patients still often need a standard loading dose while maintenance must be reduced for renal failure and dialysis. The discriminating clue is edema plus severe infection. Supported by DiPiro, AHFS Drug Information, and Lexicomp renal dosing principles.
- C: Tempting because dialysis days feel like a natural schedule modifier. Incorrect because holding all doses on dialysis days ignores the drug’s PK and can underexpose the patient; the clue is that the question asks for initial dosing principle, not a blanket hold strategy. Supported by Lexicomp and Clinical Pharmacology dosing guidance.
- D: Tempting if the learner overgeneralizes that dialysis removes efficacy. Incorrect because many renally cleared agents are effective when appropriately adjusted; the clue is no contraindication to using the drug class was given. Supported by AHFS and antimicrobial dosing references.
1.1.1.19 Question 2: A
- A: Tempting because it complicates an otherwise straightforward lab interpretation, and correct because low muscle mass can make serum creatinine underestimate the degree of kidney dysfunction. The discriminating clue is sarcopenia with low body weight. Supported by DiPiro, KDIGO-informed renal assessment principles, and Lexicomp dosing cautions.
- B: Tempting because age affects PK. Incorrect because age alone does not explain falsely reassuring creatinine as specifically as sarcopenia does. The clue eliminating it is the explicit muscle-mass issue. Supported by pharmacokinetic texts.
- C: Tempting because sex is included in renal equations. Incorrect because female sex alone is not the main reason the creatinine is unreliable here; the clue is sarcopenia. Supported by dose-estimation references.
- D: Tempting because comorbidities can alter PK. Incorrect because controlled hypothyroidism is not the key discriminator for creatinine unreliability in this stem. The clue is low muscle mass. Supported by standard pharmacotherapy references.
1.1.1.20 Question 3: B
- A: Tempting because early administration feels efficient and serious infection can favor prompt therapy. Incorrect because the drug is low protein bound and water soluble, making HD removal likely; the discriminating clue is dialysis starting one hour later. Supported by Lexicomp and Clinical Pharmacology dialysis dosing guidance.
- B: Tempting because it disrupts routine scheduling, and correct because the described PK profile predicts substantial intermittent HD removal. The single clue is the combination of low protein binding, water solubility, and immediate pre-HD timing. Supported by AHFS, Lexicomp, and standard dialysis PK principles.
- C: Tempting because it attempts to compensate for dialysis. Incorrect because doubling before dialysis is not the general safest strategy and risks unpredictable exposure; the clue is the question asks for the most appropriate next step, which is timing adjustment. Supported by dosing references.
- D: Tempting because hepatically cleared alternatives may avoid dialysis timing issues. Incorrect because substitution regardless of indication is not justified; the clue is no efficacy or safety reason to abandon the selected antimicrobial class. Supported by pharmacotherapy standards.
1.1.1.21 Question 4: B
- A: Tempting because chronic use suggests tolerance. Incorrect because chronicity does not neutralize renal accumulation or nephrotoxicity, especially with ibuprofen, baclofen, and gabapentin in ESKD. The discriminating clue is dialysis-dependent kidney failure plus these specific agents. Supported by Lexicomp, AHFS, and renal dosing references.
- B: Tempting because it identifies more than one problem, and correct because ibuprofen represents avoidable nephrotoxic exposure while baclofen and gabapentin are classic accumulation-toxicity traps in advanced kidney disease. The single clue is the medication list itself. Supported by drug labeling, Lexicomp, and DiPiro.
- C: Tempting because proton pump inhibitors have adverse-effect discussions in many settings. Incorrect because omeprazole is not the highest-yield renal danger on this list; the clue is the presence of NSAID and renally cleared neuroactive agents. Supported by standard references.
- D: Tempting because symptom control matters. Incorrect because gabapentin commonly requires reduction, not escalation, in ESKD due to neurotoxicity risk. The clue is existing TID dosing in peritoneal dialysis. Supported by Lexicomp and FDA labeling.
1.1.1.22 Question 5: B
- A: Tempting because conservative dosing seems safer after transplant. Incorrect because improving graft function can make continued dialysis-era reductions subtherapeutic. The discriminating clue is the rapidly falling creatinine and increasing urine output. Supported by transplant pharmacotherapy references and Lexicomp renal dosing principles.
- B: Tempting because it requires active follow-up, and correct because immediate post-transplant renal function changes quickly and all renally adjusted medications should be reassessed against current graft function. The clue is change over the first 48 hours. Supported by transplant medication management principles in DiPiro and clinical references.
- C: Tempting because a transplant implies restored kidney function. Incorrect because not all patients recover instantly, and overshooting doses can cause toxicity; the clue is that function is improving but not normalized. Supported by renal dosing guidance.
- D: Tempting because tacrolimus is high stakes. Incorrect because prophylaxis and other renally adjusted drugs also matter immediately after transplant. The clue is a renally adjusted prophylactic antiviral is already in use. Supported by transplant pharmacy standards.
1.1.1.23 Question 6: A
- A: Tempting because it preserves higher early exposure in a patient with poor renal function, and correct because severe infection plus edema supports a standard loading dose for a hydrophilic drug, followed by renal-adjusted maintenance. The discriminating clue is sepsis with severe edema. Supported by DiPiro, AHFS, and antimicrobial PK guidance.
- B: Tempting because both doses seem linked to kidney function. Incorrect because loading dose is not primarily a GFR question; the clue is the patient needs prompt target attainment. Supported by pharmacokinetic references.
- C: Tempting because it appears to split the difference. Incorrect because standard maintenance despite severe kidney failure risks accumulation; the clue is markedly impaired renal clearance. Supported by Lexicomp renal dosing guidance.
- D: Tempting because edema can dilute hydrophilic drugs. Incorrect because maintenance dosing still depends on clearance, not dilution alone; the clue is advanced kidney failure. Supported by standard PK texts.
1.1.1.24 Question 7: B
- A: Tempting because the creatinine looks near normal. Incorrect because cachexia and amputation reduce creatinine generation, so the value may overestimate kidney function. The discriminating clue is low creatinine production. Supported by renal assessment principles in DiPiro and drug-dosing references.
- B: Tempting because it introduces uncertainty into dosing, and correct because conservative interpretation is safest when serum creatinine is falsely reassuring in a cachectic amputee. The clue is the body composition history. Supported by Lexicomp, Clinical Pharmacology, and KDIGO-aligned assessment principles.
- C: Tempting because leukopenia is a known antiviral toxicity to monitor. Incorrect because waiting for toxicity does not fix the underlying dosing estimation problem; the clue is uncertainty exists before therapy starts. Supported by FDA labeling and antiviral references.
- D: Tempting because renal uncertainty raises safety concern. Incorrect because prophylaxis may still be indicated; the proper response is renal-aware dosing, not blanket omission. The clue is the question asks for the most defensible pharmacist response, not abandonment of indicated care. Supported by antiviral dosing references.
1.1.1.25 Question 8: B
- A: Tempting because transplantation suggests a new kidney is present. Incorrect because delayed graft function with ongoing hemodialysis means the patient still behaves like a dialysis patient for many renally handled drugs. The discriminating clue is ongoing intermittent HD on post-op day 3. Supported by transplant pharmacotherapy and renal dosing references.
- B: Tempting because it preserves older restrictions longer than some clinicians prefer, and correct because dialyzable antiinfective timing should still follow dialysis-based logic until graft function truly recovers. The clue is delayed graft function plus a substantially dialyzable drug. Supported by Lexicomp, AHFS, and transplant medication management principles.
- C: Tempting because immunosuppression is critical after transplant. Incorrect because holding needed antiinfective therapy ignores infection prevention/treatment priorities and the problem can be solved by timing adjustment. Supported by transplant infection management principles.
- D: Tempting because tacrolimus monitoring is central post-transplant. Incorrect because non-immunosuppressant dialysis timing issues remain clinically important; the clue is the antiinfective is substantially removed by HD. Supported by pharmacotherapy guidance.
Keep going with the full BCTXP Prep Course (BCTXP)
You just studied the way members do, in the same lesson interface. Full access unlocks every lesson, the question bank and flashcards for a full year.
One payment · 1 year of access · No auto-renewal