1.1.1 - Pain Etiology And Pathways
Why it matters
- BCPMP questions often test the mechanism-treatment match, not just memorized drug names. A regimen can be generally reasonable yet wrong for the specific pathway.
- Pain stems frequently include distracting details such as old imaging findings, mild lab abnormalities, or a history of “tolerance.” The scoring clue is often the type of signal being generated and amplified.
- Pharmacists must recognize when analgesic failure reflects wrong mechanism targeting, poor dosing, unsafe comorbidity overlap, or a need for referral/escalation rather than simple intensification.
- This topic sets up the next two lessons: the classifications of pain and the acute-versus-chronic framework build directly on the pathways covered here.
Key Terms & Must-Know Facts
1.1.1.1 Key terms
- Transduction — conversion of a noxious stimulus into an electrical signal at the peripheral nociceptor.
- Transmission — propagation of the pain signal through peripheral nerves, spinal cord, and ascending tracts.
- Modulation — amplification or suppression of pain signaling, especially in the dorsal horn and descending pathways.
- Perception — conscious experience of pain in higher brain centers.
- Nociceptor — sensory receptor activated by mechanical, thermal, or chemical injury.
- Peripheral sensitization — lowered activation threshold at the injury site due to inflammatory mediators.
- Central sensitization — increased excitability within the CNS causing amplified pain responses.
- A-delta fibers — thinly myelinated fibers carrying fast, sharp, localized pain.
- C fibers — unmyelinated fibers carrying slow, dull, burning, diffuse pain.
- Dorsal horn — spinal cord relay site where primary afferent input is processed and modulated.
- Ascending tract — pathway carrying pain signals from the spinal cord to the brain.
- Descending inhibition — top-down inhibitory control using serotonin, norepinephrine, and endogenous opioids.
- Hyperalgesia — exaggerated response to a painful stimulus.
- Allodynia — pain caused by a normally nonpainful stimulus.
1.1.1.2 Must-know facts
- Inflammatory mediators such as prostaglandins and bradykinin primarily drive transduction and peripheral sensitization.
- NSAIDs best fit situations where peripheral inflammatory signaling is a major driver.
- Opioids work at multiple levels but are especially relevant to transmission and modulation.
- SNRIs, TCAs, and some adjuvants matter when descending inhibitory pathways or abnormal neuronal firing are involved.
- Sharp, well-localized pain suggests more A-delta involvement; burning, aching, diffuse pain suggests more C-fiber or centrally amplified processing.
- Allodynia and hyperalgesia are strong clues for sensitization, especially central sensitization.
- A poor response to one drug class does not always equal severe disease; it may indicate mechanism mismatch.
- Duration alone does not define mechanism; acute pain can include nerve injury, and chronic pain can still have inflammatory components.
Core content
1.1.1.3 Foundational map of the pain pathway
A Explanation
The first board-style decision conflict is simple but high yield: is the stem asking you to treat where the pain signal starts, where it travels, or where it gets amplified? The single rule that resolves this is to place the patient’s clue into the pathway step: tissue injury points to transduction; radiating or shooting signal suggests transmission; allodynia/hyperalgesia suggests modulation failure; distress, sleep disruption, and central amplification raise perception and higher-order processing considerations. See Fig 1.
WHY THIS IS TESTED: Many wrong answers are not “bad analgesics”; they are wrong-level analgesics. An anti-inflammatory choice is tempting in pain that sounds severe, but if the clue is sensory abnormality rather than inflammation, the mechanism mismatch matters more than intensity.
Transduction begins when damaged tissue releases prostaglandins, cytokines, bradykinin, hydrogen ions, and other mediators that lower nociceptor threshold. Transmission then carries the signal along A-delta and C fibers to the dorsal horn, then upward through ascending pathways. Modulation occurs in the spinal cord and brainstem, where the signal may be inhibited or amplified. Perception is the conscious experience shaped by cortical interpretation, mood, attention, memory, and context. Pharmacists are rarely asked to localize every anatomic tract in detail; they are asked to identify which stage best explains the symptom pattern and therefore which class is most likely to help.
Exam takeaway: Match the patient clue to the pathway level before choosing a drug class.
flowchart LR
A[Tissue injury or trigger] --> B[Transduction at nociceptor]
B --> C[Transmission via A-delta and C fibers]
C --> D[Dorsal horn processing]
D --> E[Ascending pathways to brain]
E --> F[Perception of pain]
G[Descending inhibition] --> D
H[Peripheral inflammation] --> B
I[Central sensitization] --> D
B Worked example
A 59-year-old man with osteoarthritis, type 2 diabetes, and stage 3a CKD reports “burning and painful skin sensitivity” in the feet for 4 months. Current medications include acetaminophen 1,000 mg by mouth three times daily, ibuprofen 400 mg by mouth as needed most evenings, metformin, and lisinopril. A1c is 8.6%. ESR is mildly elevated after a recent viral illness. He asks whether increasing ibuprofen is the most appropriate next step because the pain is now 8/10.
Identify task: determine whether current therapy is mismatched to the main pain pathway. Extract key facts: burning quality, skin sensitivity, chronicity, diabetes, and poor glycemic control suggest abnormal neuronal signaling rather than pure peripheral inflammation. Apply rule: when the clue is sensory abnormality and burning pain, reject escalation of NSAID intensity as the primary mechanism-based answer. Eliminate distractors: the elevated ESR is noise; it may tempt an inflammatory interpretation, but the symptom pattern is more decisive. CKD also makes chronic NSAID escalation less attractive. Verify: recommend reassessing likely neuropathic mechanism, reviewing renal safety, and discussing an adjuvant option with monitoring rather than simply increasing ibuprofen.
C Exam trap
D Checkpoint
Question: A patient describes pain as “sharp at first, then lingering and dull for hours after the injury.” Which pairing best matches the dominant fiber types involved?
- A-delta first, then C fibers
- C fibers first, then A-delta fibers
- Only A-delta fibers throughout
- Only motor fibers throughout
Answer: A. A-delta fibers first, then C fibers.
- A. Tempting because the stem describes fast pain followed by slow pain; it is right because A-delta fibers carry sharp immediate pain and C fibers carry dull lingering pain.
- B. Tempting if you remember that C fibers are common in chronic pain; it is wrong because the initial sharp, localized phase is the classic A-delta clue.
- C. Tempting if you focus only on the first word “sharp”; it is wrong because the prolonged dull component requires a slower pathway.
- D. Tempting only if the learner confuses peripheral nerve types broadly; it is wrong because motor fibers do not mediate nociceptive pain signaling.
1.1.1.4 Peripheral sensitization and inflammatory signaling
A Explanation
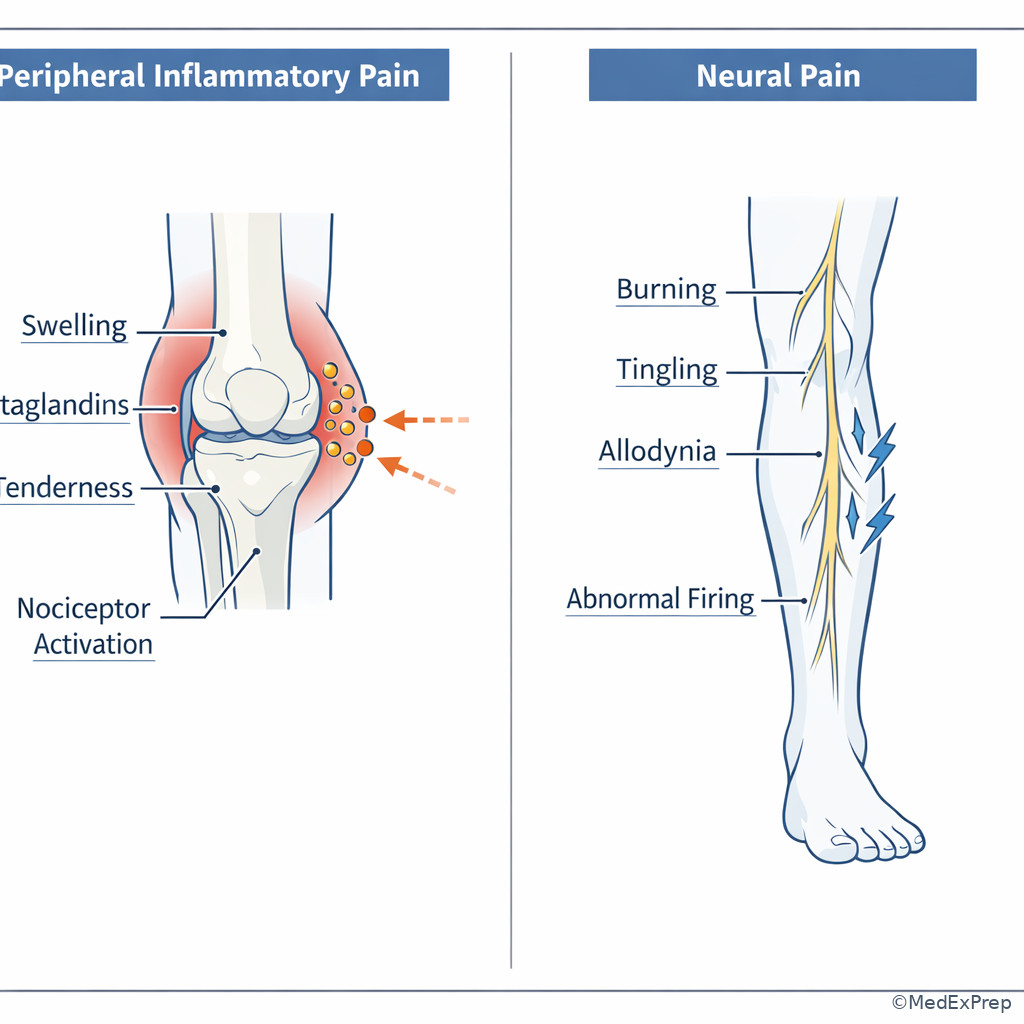
The decision conflict here is choose anti-inflammatory targeting versus reject it when inflammation is not the main driver. The single resolving rule is this: if the stem emphasizes tissue injury, swelling, warmth, tenderness, movement-provoked pain, or inflammatory conditions, think transduction and peripheral sensitization first. See Fig 2. Peripheral sensitization occurs when mediators such as prostaglandins, bradykinin, histamine, and cytokines reduce nociceptor threshold, so ordinary movement of damaged tissue produces greater pain.
WHY THIS IS TESTED: exam questions often force a choice between an anti-inflammatory and a centrally acting alternative. The best answer depends less on “how much pain” and more on what biology the stem is signaling. NSAIDs and acetaminophen are often considered together, but they are not interchangeable in every pathway. NSAIDs are especially useful where prostaglandin-driven peripheral signaling is prominent. Acetaminophen may still help mild-to-moderate pain but does not offer the same peripheral anti-inflammatory effect.
Peripheral sensitization also explains why inflamed tissue feels unusually tender and why pain improves when the inflammatory trigger is reduced. In pharmacist practice, this matters for regimen matching and safety review. A patient with peripheral inflammatory pain may benefit from an NSAID strategy if renal function, GI risk, cardiovascular risk, age, and concomitant anticoagulation permit. A patient with burning dysesthesia and minimal inflammatory clues should push you away from reflexive NSAID escalation. See Fig 3 for a medication-mechanism comparison.
Exam takeaway: Inflammatory mediators lowering nociceptor threshold make anti-inflammatory strategies more plausible.
flowchart TD
A[Tissue damage] --> B[Release of prostaglandins bradykinin cytokines]
B --> C[Lowered nociceptor threshold]
C --> D[More firing with movement or pressure]
D --> E[Tenderness and amplified local pain]
F[NSAID or anti-inflammatory strategy] --> B
Exam takeaway: Localized swollen tender tissue supports anti-inflammatory targeting more than burning sensory distortion does.
B Worked example
A 72-year-old woman with osteoarthritis, HFpEF, atrial fibrillation on apixaban, and hypertension reports acute knee swelling and pain after gardening. Home medications include acetaminophen 650 mg by mouth every 8 hours, apixaban 5 mg by mouth twice daily, furosemide, losartan, and topical diclofenac used intermittently. She asks whether ibuprofen 600 mg by mouth three times daily for a week is the best initial therapy because the pain worsens with walking. Her foot tingling from chronic diabetes is unchanged.
Identify task: mechanism-fit plus safety assessment. Extract key facts: acute swollen tender joint with movement-provoked pain supports inflammatory transduction. Apply rule: an NSAID mechanism fits the pathway, but systemic ibuprofen is unsafe here because of anticoagulation, HF, and renal-hemodynamic risk. Eliminate distractors: her diabetic foot tingling is a tempting clue toward a neuropathic agent, but it is chronic and unchanged; it does not explain the current flare. Verify: recommend safer localized strategies and communication with the prescriber regarding anti-inflammatory options that minimize systemic harm.
C Exam trap
D Checkpoint
Question: Which finding most strongly supports peripheral sensitization as the dominant current mechanism?
- Localized joint warmth and tenderness after tissue strain
- Light touch causing burning pain over both feet for months
- Diffuse pain with fatigue and nonrestorative sleep
- Sudden electric shock pain radiating down one leg
Answer: A. Localized joint warmth and tenderness after tissue strain.
- A. Tempting because it describes a familiar inflammatory picture; it is right because local warmth and tenderness after strain match inflammatory mediator-driven nociceptor sensitization.
- B. Tempting because it signals severe pain; it is wrong because allodynia and burning in both feet suggest neuropathic or centrally amplified processing rather than local inflammatory transduction.
- C. Tempting because diffuse pain can be severe and chronic; it is wrong because the symptom cluster points more toward nociplastic central amplification.
- D. Tempting because radiating pain is common in musculoskeletal complaints; it is wrong because electric shock radiation is more consistent with nerve transmission pathology.
- The pathway step most directly reduced by prostaglandin inhibition is transduction.
- True or False: High pain intensity alone proves an NSAID is the best mechanism-based choice. False.
- Name 3 inflammatory clues: swelling, warmth, tenderness with movement.
1.1.1.5 Transmission, dorsal horn processing, and descending modulation
A Explanation
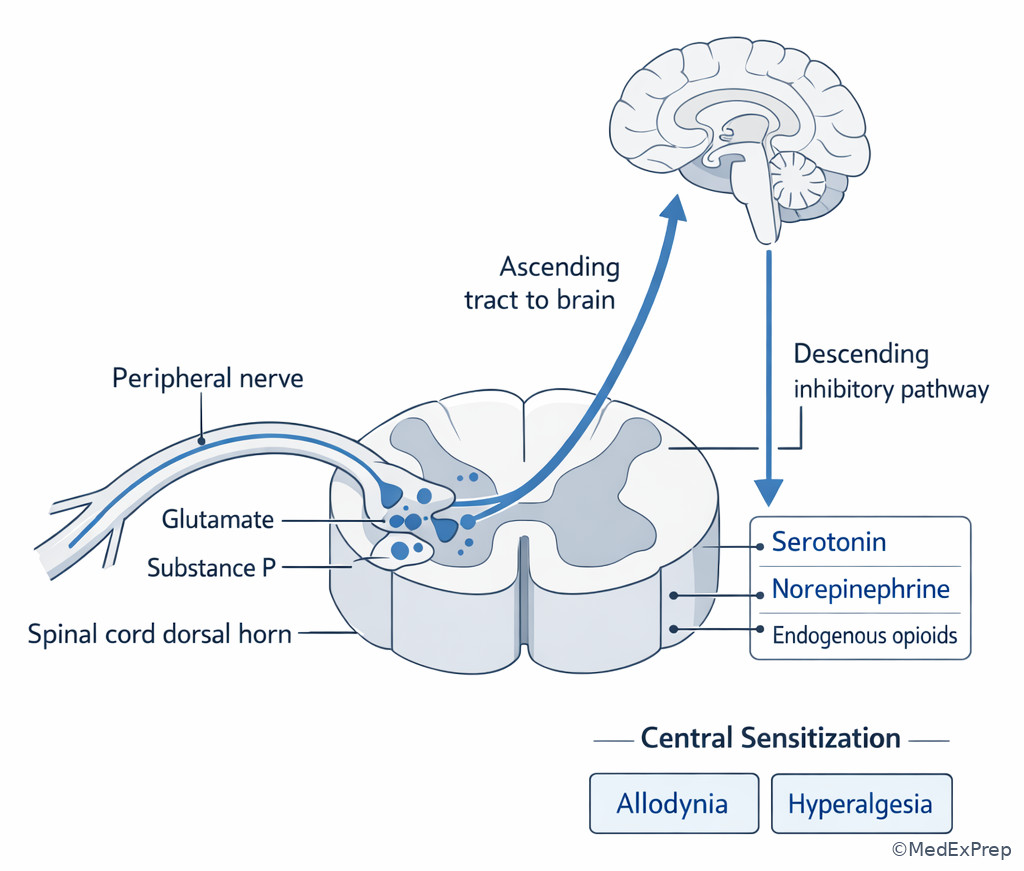
The key decision conflict is choose a strategy that affects neuronal transmission/modulation versus reject a purely peripheral strategy. The single finding that resolves this is the presence of nerve-like descriptors or signs of amplified spinal processing: burning, electric, shooting, radiating pain; allodynia; hyperalgesia; pain out of proportion to tissue findings. See Fig 4. Transmission refers to signal movement from nociceptor to spinal cord and upward; modulation refers to what happens to that signal in the dorsal horn and descending inhibitory systems.
WHY THIS IS TESTED: many analgesics affect more than one part of the pathway, so exams test whether you can identify the dominant mismatch. A patient whose main clue is altered sensory processing may still have some inflammation, but the mechanism-based answer often shifts toward adjuvant or centrally active therapy because the pain is being sustained by abnormal neuronal signaling or insufficient descending inhibition.
Descending inhibitory pathways use serotonin, norepinephrine, and endogenous opioids to dampen nociceptive traffic. When that inhibition is deficient, the patient may report persistent, amplified pain even after the original tissue injury should be improving. This is one reason SNRIs and TCAs appear in pain pharmacotherapy despite being known as antidepressants. They are not selected because the patient “seems depressed”; they are selected when the pain biology suggests altered central modulation. Pharmacists should avoid overdiagnosing the pain type but should identify when the medication list misses a plausible mechanism target.
Exam takeaway: Allodynia and hyperalgesia are pathway clues that push attention toward modulation failure.
flowchart TD
A[Peripheral input] --> B[Dorsal horn synapse]
B --> C[Ascending pain signal]
D[Descending serotonin and norepinephrine inhibition] --> B
E[Endogenous opioids] --> B
F[Central sensitization] --> B
G[Allodynia and hyperalgesia] --> F
Exam takeaway: Dorsal horn amplification and weak descending inhibition explain why pain can persist beyond the original injury signal.
B Worked example
A 47-year-old woman with depression, obesity, and chronic low back pain takes naproxen 500 mg by mouth twice daily and omeprazole 20 mg daily. She reports a new “shooting, electric pain” from the low back to the lateral foot after lifting a box, along with pain from light touch over the calf. Lumbar x-ray from last year showed degenerative changes. Serum creatinine is normal. She asks whether switching from naproxen to a different NSAID is the most appropriate next step.
Identify task: determine whether treatment should still center on inflammatory transduction. Extract key facts: shooting, electric, radiating pain and allodynia are pathway clues for abnormal transmission/modulation. Apply rule: reject the idea that a stronger or different NSAID is automatically the best mechanism-based change. Eliminate distractors: chronic degenerative changes on x-ray are tempting noise; they can falsely anchor the learner to nociceptive osteoarthritic pain. Verify: recommend reassessment for likely neuropathic features, align therapy toward the neural mechanism, and communicate red flags if weakness or bladder symptoms emerge.
C Exam trap
D Checkpoint
Question: Which symptom most strongly suggests a modulation abnormality rather than uncomplicated peripheral transduction?
- Allodynia when clothing brushes the skin
- Localized swelling after ankle sprain
- Pain only with direct pressure on a bruised area
- Immediate sharp pain at the moment of a cut
Answer: A. Allodynia when clothing brushes the skin.
- A. Tempting because it is a classic board clue; it is right because pain from a normally nonpainful stimulus strongly suggests central or spinal amplification.
- B. Tempting because swelling is associated with pain; it is wrong because it fits peripheral inflammatory transduction.
- C. Tempting because bruises are painful; it is wrong because direct pressure pain alone does not imply abnormal modulation.
- D. Tempting because it is acute and dramatic; it is wrong because this is typical initial nociceptor activation and A-delta transmission rather than allodynic amplification.
1.1.1.6 Perception, central amplification, and the biopsychologic overlay
A Explanation
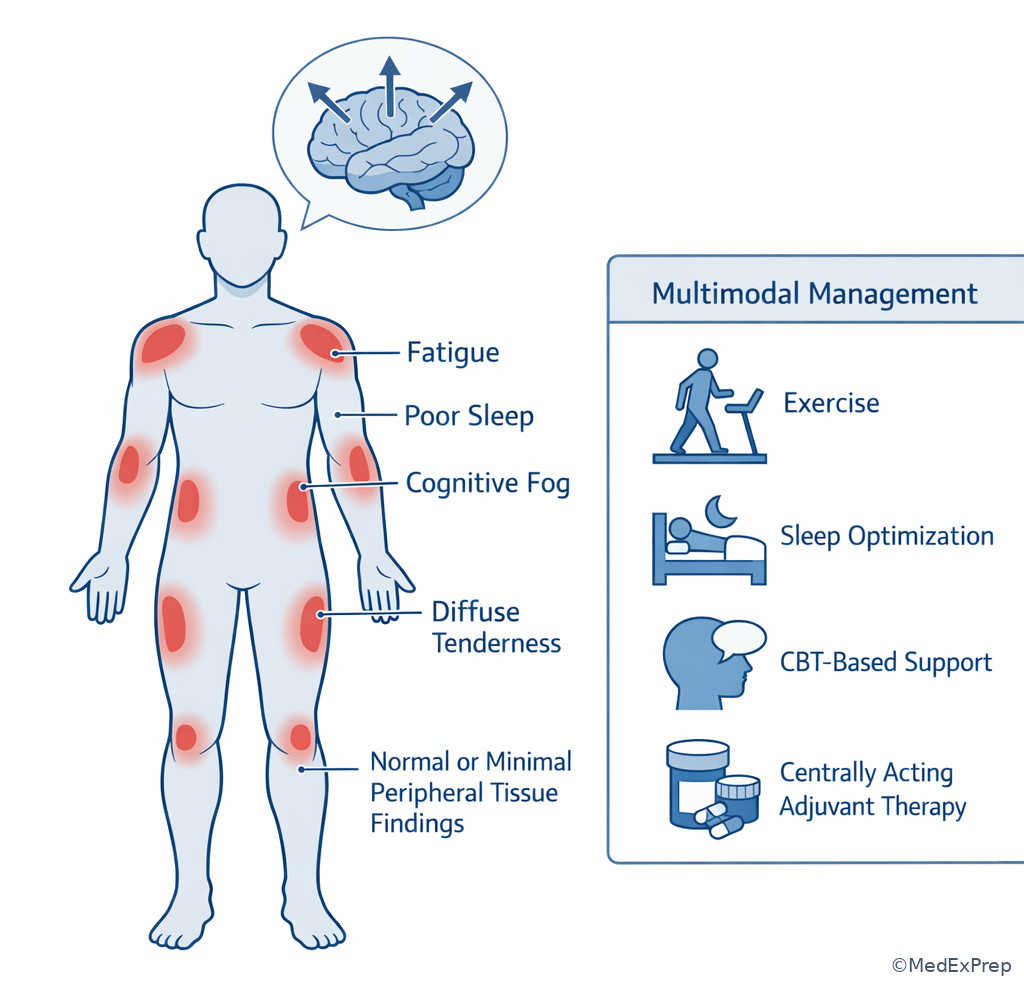
The decision conflict here is respect the reality of pain perception without reducing it to “just psychological,” and choose multimodal reasoning versus one-dimensional escalation. The single rule that resolves this is: when pain is diffuse, disproportionate to tissue findings, associated with fatigue, sleep disruption, cognitive symptoms, or broad sensitivity, think altered central processing and perception as part of the mechanism. See Fig 5. This does not mean the pain is unreal. It means the CNS is participating strongly in the pain experience.
WHY THIS IS TESTED: board stems often include mood disorder, insomnia, trauma history, or high distress as distractors. The wrong move is to dismiss pain or to assume opioid escalation is the universal fix. The right move is to recognize that higher-order processing and central amplification affect both symptom burden and the likely benefit of multimodal care. Pharmacists should frame this as mechanism-based care planning, not psychiatric labeling.
Perception involves cortical and subcortical interpretation of incoming signals. Attention, expectation, fear, depression, and sleep deprivation can intensify perceived pain. When central amplification dominates, local tissue findings may seem modest relative to the patient’s severity. A purely peripheral strategy may underperform. In practice, this points toward functional goals, nonpharmacologic integration, and careful choice of centrally acting agents when appropriate. Upcoming lessons will formalize nociplastic pain, but already you should recognize the pattern. See Fig 6 for the comparison image.
Exam takeaway: Diffuse pain with sleep and fatigue clues should trigger multimodal thinking instead of reflexive anti-inflammatory escalation.
flowchart LR
A[Peripheral input] --> B[Brain interpretation]
C[Poor sleep] --> B
D[Mood distress] --> B
E[Attention and threat focus] --> B
B --> F[Increased pain perception]
G[Central amplification] --> F
H[Multimodal strategy] --> G
Exam takeaway: Diffuse tenderness, fatigue, and sleep disruption are pattern clues for centrally amplified pain processing.
B Worked example
A 38-year-old woman with migraines, irritable bowel syndrome, and major depressive disorder reports 2 years of diffuse musculoskeletal pain. Medications include sertraline 100 mg by mouth daily, acetaminophen as needed, and sumatriptan as needed. She says “everything hurts,” sleeps 4 to 5 hours nightly, and has tenderness in multiple regions without swelling. CRP is normal. She asks whether starting scheduled naproxen 500 mg by mouth twice daily is the most appropriate next step because her friend improved on it.
Identify task: match the stem to pathway biology. Extract key facts: diffuse pain, sleep disturbance, IBS and migraine overlap, normal inflammatory markers, and chronicity suggest central amplification. Apply rule: reject the idea that peripheral anti-inflammatory therapy alone best addresses this pattern. Eliminate distractors: normal CRP is supportive but not decisive; the broader symptom cluster is the real discriminator. Verify: recommend a multimodal, function-centered plan and careful review of medication interaction/safety if considering centrally acting options.
C Exam trap
D Checkpoint
Question: Which additional finding best supports a major perception/central amplification component?
- Nonrestorative sleep and diffuse tenderness without swelling
- Single swollen wrist after a fall
- Immediate lancinating pain after touching a hot pan
- Pain limited to a bruised shin with palpation only
Answer: A. Nonrestorative sleep and diffuse tenderness without swelling.
- A. Tempting because it bundles several broad clues; it is right because diffuse pain plus sleep dysfunction and absent local inflammation suggests central amplification.
- B. Tempting because acute pain can be intense; it is wrong because a swollen wrist after trauma is more consistent with local peripheral nociception.
- C. Tempting because it sounds dramatic; it is wrong because it reflects acute nociceptor activation from thermal injury.
- D. Tempting because bruises can remain tender; it is wrong because isolated local palpation pain does not imply widespread central processing abnormalities.
- True or False: Normal inflammatory markers rule out a pain mechanism requiring treatment. False.
- The symptom cluster most associated with central amplification includes diffuse pain, fatigue, and poor sleep.
- Name one reason perception matters on exam stems: it changes which therapies are likely to work and what outcomes to monitor.
1.1.1.7 Pharmacotherapy implications: matching drug class to pathway
A Explanation
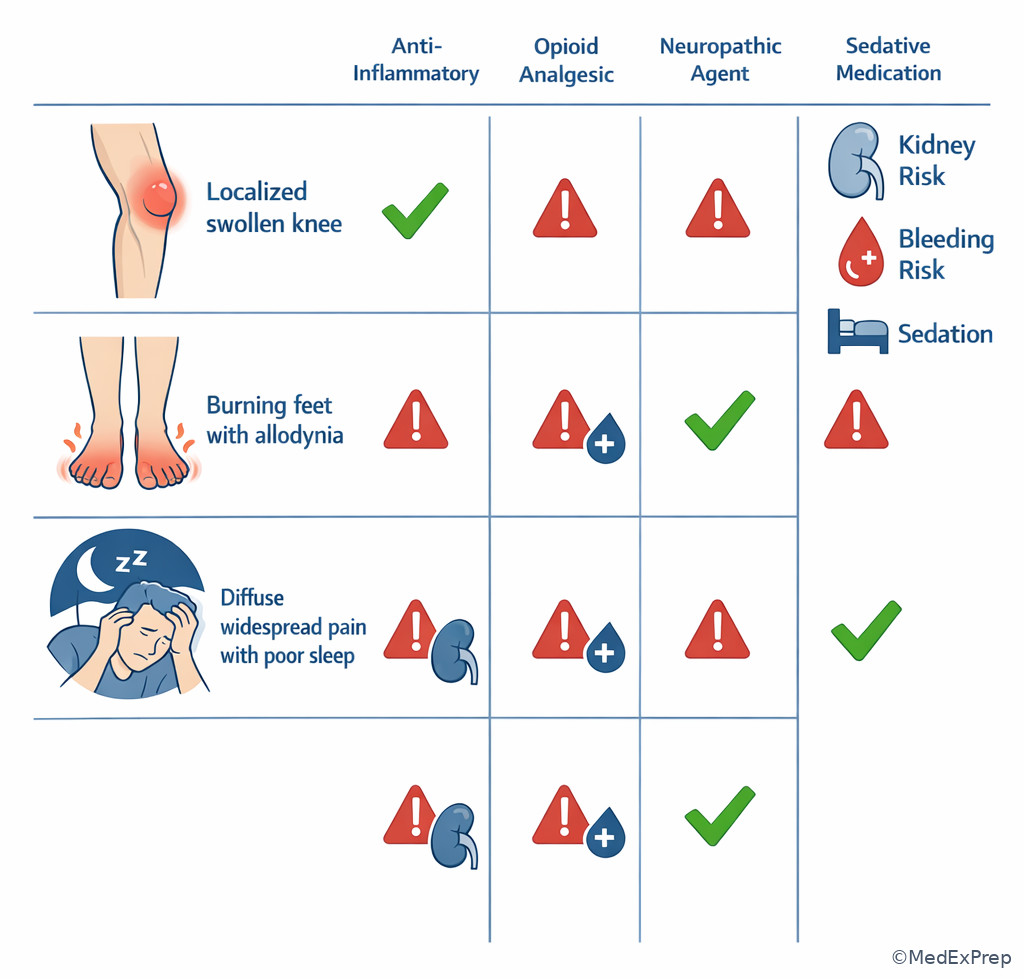
This final integration section asks the most board-relevant question: given the pathway clue, which medication category is reasonable, and which is the tempting mismatch? The single resolving rule is to choose the class whose mechanism acts at the dominant pain level while screening for comorbidity and safety constraints. See Fig 1 and Fig 6. For inflammatory transduction, anti-inflammatory therapy is often more plausible. For abnormal neural transmission or impaired descending inhibition, adjuvant analgesic strategies become more plausible. For mixed or centrally amplified patterns, multimodal care and function-based monitoring matter most.
WHY THIS IS TESTED: the BCPMP perspective is not to “diagnose pain perfectly,” but to identify the medication-related problem and recommend the safest mechanism-aligned next step. Questions may ask what requires clarification, what to monitor, or which regimen is mismatched. The answer often depends on one discriminating clue: local inflammation, sensory distortion, diffuse amplification, or mixed pathology.
Pharmacists should also anticipate common medication safety conflicts. Systemic NSAIDs may fit inflammatory pain yet be poor choices in CKD, GI bleed risk, HF, or anticoagulation. Gabapentinoids may fit abnormal transmission but become unsafe with sedation burden, falls, or renal misdosing. SNRIs may fit modulation failure but require review of blood pressure, serotonergic combinations, and withdrawal concerns. Opioids can affect transmission and perception but are not automatically first-line for every severe pain complaint, especially when the dominant mechanism is not opioid-responsive or when safety risks outweigh expected benefit.
Exam takeaway: The best drug choice depends on where the pain pathway is dysregulated and what safety limits are present.
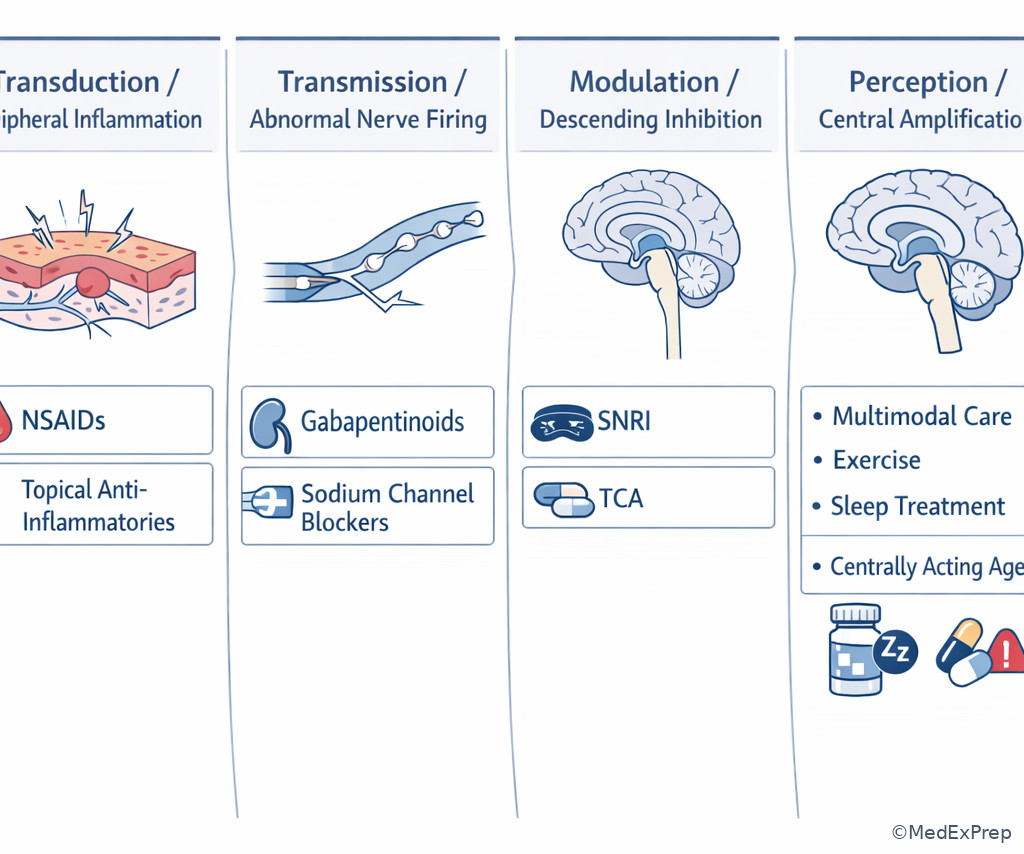
Exam takeaway: Analgesic failure often reflects mechanism mismatch or safety limits rather than simply needing a higher dose.
B Worked example
A 66-year-old man is discharged after thoracotomy. He has CAD, COPD, CKD stage 3b, and chronic insomnia. Discharge medications include acetaminophen 1,000 mg by mouth every 8 hours, oxycodone immediate-release 5 mg by mouth every 6 hours as needed, and ibuprofen 600 mg by mouth every 8 hours for 10 days. He reports severe incisional tenderness with coughing, but also numb burning pain near the scar. He takes aspirin 81 mg daily and sertraline 50 mg daily.
Identify task: identify the drug-therapy problem in a mixed-pathway patient during transition of care. Extract key facts: nociceptive postoperative tissue pain plus a neuropathic scar component; CKD, CAD, aspirin, and COPD raise safety concerns. Apply rule: do not assume one drug handles all mechanisms safely. The ibuprofen is mechanism-plausible for inflammatory tissue pain but high risk in CKD/CAD; oxycodone may help acute severe pain but requires careful monitoring given COPD and insomnia. Eliminate distractors: burning near the scar tempts complete pivot away from nociceptive management, but tissue pain remains present. Verify: communicate that this is mixed pain requiring safer multimodal planning and close monitoring rather than automatic continuation of every discharge medication.
C Exam trap
D Checkpoint
Question: Which statement best reflects a mechanism-based pharmacist approach?
- If pain is severe, intensify the most potent available analgesic regardless of symptom quality.
- Choose therapy by dominant pathway clue, then verify comorbidity and interaction safety.
- Normal imaging rules out centrally amplified pain.
- A poor response to NSAIDs confirms opioid therapy is the best next step.
Answer: B. Choose therapy by dominant pathway clue, then verify comorbidity and interaction safety.
- A. Tempting because severe pain can prompt urgency; it is wrong because mechanism mismatch and safety constraints can make a potent drug the wrong answer.
- B. Tempting because it sounds algorithmic; it is right because board-style pain pharmacotherapy depends on pathway recognition followed by individualized safety review.
- C. Tempting because learners overvalue objective imaging; it is wrong because central amplification can exist despite limited structural findings.
- D. Tempting because nonresponse may look like under-treatment; it is wrong because NSAID failure can reflect wrong mechanism, not automatic need for opioids.
Tables
| Pathway step | Main exam clue | Typical symptom language | Medication implication |
|---|---|---|---|
| Transduction | Tissue injury or inflammation | Tender, swollen, movement-provoked, localized | Anti-inflammatory strategy more plausible if safe |
| Transmission | Abnormal nerve signal spread | Burning, electric, shooting, radiating | Adjuvant/neural pathway targeting becomes more plausible |
| Modulation | Amplified spinal or descending control problem | Allodynia, hyperalgesia, pain out of proportion | Central or adjuvant strategies; avoid purely peripheral thinking |
| Perception | Higher-order amplification | Diffuse pain, fatigue, poor sleep, distress impact | Multimodal plan and function-based follow-up |
| Pattern | Choose first-pass thinking | Reject as primary move | Why the rejection matters |
|---|---|---|---|
| Localized swollen inflammatory flare | Peripheral inflammatory targeting | Assuming a neural-only regimen is best | Misses prostaglandin-driven transduction |
| Burning allodynic foot pain | Neural transmission/modulation targeting | Escalating NSAID because pain score is high | Severity does not equal inflammatory mechanism |
| Diffuse pain with sleep disturbance | Central amplification and multimodal plan | One-dimensional anti-inflammatory escalation | Fails to address perception and central processing |
| Mixed postoperative tissue plus nerve pain | Multimodal, safety-screened combination thinking | Single “strongest” drug strategy | Mixed mechanisms need balanced targeting and monitoring |
| Finding in stem | Most likely dominant mechanism | Closest confounder | Single discriminator |
|---|---|---|---|
| Warm swollen joint after overuse | Peripheral sensitization | Neuropathic pain | Local inflammation rather than burning sensory distortion |
| Electric pain down leg with touch pain | Transmission/modulation abnormality | Musculoskeletal strain | Radiation and allodynia |
| Diffuse body pain with fatigue and insomnia | Central amplification/perception-heavy state | Inflammatory arthritis | Broad symptoms with limited local inflammatory findings |
| Pain from clothing brushing skin | Modulation abnormality | Simple tenderness | Normally nonpainful stimulus becomes painful |
| Immediate sharp pain, then dull ache | Sequential A-delta then C-fiber signaling | Single-fiber mechanism | Two-phase temporal pattern |
| Drug category | Best pathway fit | Common safety screen | Monitoring focus |
|---|---|---|---|
| NSAIDs | Peripheral inflammatory transduction | CKD, GI bleed, HF, anticoagulation, BP | Movement pain, renal function, edema, GI tolerance |
| Acetaminophen | Mild nociceptive support; not strongly anti-inflammatory | Liver disease, total daily dose, combination products | Total dose, symptom relief, adherence |
| Gabapentinoid-type strategy | Neural transmission abnormalities | Renal dosing, sedation, falls, misuse risk | Dizziness, somnolence, renal function, allodynia |
| SNRI/TCA-type strategy | Descending modulation and central amplification | Interactions, BP, anticholinergic burden, suicidality | Function, sleep, BP, adverse effects, time-to-benefit |
| Opioid strategy | Severe pain when benefits outweigh risks; mixed mechanism contexts | Sedation, respiratory risk, interactions, constipation | Respiratory status, sedation, bowel regimen, function |
Exam Traps & Differentiators
- Most common wrong answer: escalating the familiar analgesic simply because pain is severe. Why: learners confuse severity with mechanism. Fix: identify whether the stem’s decisive clue is inflammatory, neural, or centrally amplified.
- Looks similar but isn’t: inflammatory tenderness versus allodynia. Both can sound like “touch hurts,” but allodynia means a normally nonpainful stimulus is painful, pointing to modulation failure rather than local inflammation.
- Looks similar but isn’t: chronic musculoskeletal pain versus neuropathic pain. Chronicity alone does not define mechanism; “burning/electric/radiating” matters more than duration.
- Looks similar but isn’t: high ESR or old imaging findings versus current pathway clues. These details are often noise unless they directly match the symptom pattern.
| If the stem says... | Think... | Do not reflexively think... |
|---|---|---|
| Burning, electric, shooting | Abnormal neural transmission | “Need a stronger NSAID” |
| Allodynia, hyperalgesia | Modulation/central sensitization | Simple local inflammation only |
| Warmth, swelling, movement pain | Peripheral inflammatory transduction | Diffuse central amplification as the sole explanation |
| Diffuse pain, fatigue, poor sleep | Central amplification and multimodal care | Normal labs mean no real pain problem |
| Poor response to one class | Possible mechanism mismatch | Automatic need for opioid escalation |
Related future traps: in Nociceptive Neuropathic And Nociplastic Pain, you will separate these patterns formally; in Acute And Chronic Pain States, you will learn why chronicity does not automatically equal opioid candidacy or central amplification.
Algorithm / Approach
Rapid Review
- Transduction → tissue mediator-driven nociceptor activation; think inflammation clues.
- A-delta fibers → fast, sharp, localized pain; first wave after injury.
- C fibers → slow, dull, burning, diffuse pain; lingering second wave.
- Peripheral sensitization → lowered threshold at the injury site; touch/pressure hurts more locally.
- Transmission abnormality → burning, electric, radiating descriptors separate it from simple inflammation.
- Modulation failure → allodynia or hyperalgesia is the discriminator.
- Perception-heavy state → diffuse pain with fatigue and poor sleep separates it from localized injury.
- NSAID success pattern → swollen tender movement-provoked pain more than sensory distortion.
- NSAID failure → may mean mechanism mismatch, not inadequate pain seriousness.
- Adjuvant-friendly pattern → abnormal sensation and allodynia more than warmth/swelling.
- Mixed pain → do not force one-pathway logic; combine mechanism thinking with safety review.
- Old imaging → weak discriminator compared with current symptom language.
- Normal inflammatory labs → do not rule out clinically important centrally amplified pain.
- Pharmacist best next step → identify pathway, align drug class, then screen interactions and organ function.
Self-check quiz
1. A 34-year-old man with ankle sprain takes ibuprofen 400 mg by mouth every 6 hours as needed and reports localized swelling, warmth, and tenderness at the lateral ankle. Which pathway step is most directly linked to prostaglandin-driven nociceptor activation in this stem?
- Transduction
- Transmission
- Perception
- Descending inhibition
2. A 52-year-old woman with diabetes takes acetaminophen 1,000 mg by mouth three times daily and reports 6 months of burning foot pain with painful light touch. Which finding most strongly supports modulation or central sensitization rather than localized inflammatory pain?
- Allodynia when bedsheets touch the feet
- Warmth and swelling of one metatarsophalangeal joint
- Pain only when stepping on a stone
- Sharp pain immediately after stepping on a tack
3. A 68-year-old woman with CKD stage 3, HF, and osteoarthritis takes acetaminophen 650 mg by mouth every 8 hours and asks about ibuprofen 600 mg by mouth three times daily for a swollen painful knee after overuse. The pain is localized and worsens with walking; she has no burning or radiating symptoms. What is the most appropriate pharmacist recommendation?
- Recommend systemic ibuprofen because the pathway fit outweighs all safety concerns
- Recognize inflammatory pathway fit but clarify safer alternatives because systemic NSAID risk is high
- Recommend duloxetine immediately because all osteoarthritis pain is centrally amplified
- Advise doubling acetaminophen to 2,000 mg by mouth every 8 hours because noninflammatory options are safer
4. A 45-year-old man with obesity and chronic low back pain takes naproxen 500 mg by mouth twice daily. He now describes new electric pain radiating to the foot with pain from light touch over the calf. Lumbar x-ray last year showed degenerative changes. What is the most appropriate interpretation for the pharmacist to communicate?
- The current symptom pattern suggests abnormal neural transmission/modulation rather than simple inflammatory pain alone
- The old x-ray finding proves the pain remains purely nociceptive and should be treated with a different NSAID
- The pain is probably exaggerated because imaging findings are chronic
- The most appropriate next step is automatic opioid escalation because NSAID therapy failed
5. A 40-year-old woman with IBS, migraine, and depression takes sertraline 100 mg by mouth daily and acetaminophen as needed. She reports diffuse body pain, poor sleep, and fatigue for 18 months with normal CRP and no swollen joints. Which approach is most appropriate?
- Focus on central amplification and a multimodal, function-based plan
- Escalate to scheduled naproxen because the absence of swelling does not matter
- Conclude the pain is not clinically significant because inflammatory markers are normal
- Recommend opioid initiation because diffuse pain indicates severe tissue injury
6. A 71-year-old man with CAD, CKD stage 3b, and diabetic neuropathy is discharged on acetaminophen 1,000 mg by mouth every 8 hours, ibuprofen 600 mg by mouth every 8 hours for 7 days, and oxycodone 5 mg by mouth every 6 hours as needed after a rib fracture. He reports localized pleuritic tenderness plus burning skin sensitivity near the fracture line. Which medication-related problem most requires clarification?
- The ibuprofen is mechanism-plausible for tissue pain but high-risk because CKD and CAD make systemic NSAID continuation unsafe
- The oxycodone should be stopped immediately because opioids never help mixed pain
- The acetaminophen should be avoided because localized tenderness proves inflammation only
- The burning sensitivity means all nociceptive therapy should be discontinued
7. A 63-year-old woman with diabetic kidney disease, generalized anxiety disorder, and chronic shoulder osteoarthritis takes meloxicam 15 mg by mouth daily, acetaminophen 650 mg by mouth every 8 hours, and gabapentin 300 mg by mouth nightly. She now reports a new hot swollen shoulder after overuse while her longstanding burning foot pain is unchanged. Which interpretation best guides the next recommendation?
- The current shoulder flare most likely reflects peripheral inflammatory transduction despite coexisting neuropathic pain elsewhere
- The chronic burning feet prove the shoulder pain must also be neuropathic
- The existing gabapentin makes inflammatory pain impossible
- The best move is to ignore the shoulder mechanism and focus only on total pain score
8. A 57-year-old man with depression, insomnia, and chronic neck pain takes diclofenac 75 mg by mouth twice daily and omeprazole 20 mg daily. He reports persistent pain despite improved neck range of motion after physical therapy. The most bothersome symptom is pain from shirt collar contact and burning pain extending into the forearm. Which statement best explains why changing to celecoxib alone is unlikely to be the best next step?
- The dominant clue is allodynia and burning radiation, which points away from purely peripheral anti-inflammatory targeting as the sole adjustment
- Celecoxib is never used for musculoskeletal pain
- Improved range of motion means the pain is psychogenic
- Any chronic pain that persists after NSAID therapy requires opioid conversion
Answer key
1.1.1.8 1. Answer: A — Transduction
- A. Transduction — Tempting because localized warmth, swelling, and tenderness are classic inflammatory cues. It is correct because prostaglandin-mediated nociceptor activation occurs at the site of tissue injury during transduction. The single stem clue is the swollen warm ankle after sprain. Sources: DiPiro Pharmacotherapy; AHFS Drug Information.
- B. Transmission — Tempting because pain signals do travel through nerves after injury. It is incorrect for this question because the stem asks specifically about prostaglandin-driven nociceptor activation, which occurs before the signal is propagated. The discriminator is “prostaglandin-driven” plus local inflammation. Sources: DiPiro; Clinical Pharmacology.
- C. Perception — Tempting because all pain is ultimately experienced in the brain. It is incorrect because perception is the conscious experience, not the peripheral activation step targeted by inflammatory mediators. The discriminator is localized inflammatory signs rather than diffuse central features. Sources: DiPiro; ACCP pain management guidance.
- D. Descending inhibition — Tempting because central control influences pain intensity. It is incorrect because descending inhibition modulates spinal processing rather than initiating the pain signal at the injury site. The discriminator is direct peripheral inflammatory activation. Sources: DiPiro; AHFS.
1.1.1.9 2. Answer: A — Allodynia when bedsheets touch the feet
- A. Allodynia when bedsheets touch the feet — Tempting because it is a classic exam buzz clue. It is correct because pain from a normally nonpainful stimulus strongly supports modulation abnormality or central sensitization. The discriminator is painful light touch. Sources: DiPiro; ACCP guidance.
- B. Warmth and swelling of one metatarsophalangeal joint — Tempting because diabetic patients can also develop inflammatory pain. It is incorrect here because this points to local inflammatory transduction, not modulation failure. The discriminator is unilateral warmth/swelling. Sources: AHFS; Clinical Pharmacology.
- C. Pain only when stepping on a stone — Tempting because it is a real pain trigger in the foot. It is incorrect because direct noxious mechanical stimulation does not establish central sensitization. The discriminator is that the stimulus itself is painful. Sources: DiPiro.
- D. Sharp pain immediately after stepping on a tack — Tempting because it is acute and intense. It is incorrect because immediate sharp pain reflects nociceptor activation and A-delta transmission, not allodynic modulation failure. The discriminator is the clearly painful stimulus. Sources: DiPiro; AHFS.
1.1.1.10 3. Answer: B — Recognize inflammatory pathway fit but clarify safer alternatives because systemic NSAID risk is high
- A. Recommend systemic ibuprofen because the pathway fit outweighs all safety concerns — Tempting because localized swollen activity-related pain does fit inflammatory transduction. It is incorrect because CKD and HF are major clinical facts that limit systemic NSAID safety despite good mechanism fit. The discriminator is CKD stage 3 plus HF. Sources: Lexicomp; AHFS; FDA NSAID labeling.
- B. Recognize inflammatory pathway fit but clarify safer alternatives because systemic NSAID risk is high — Tempting because it balances mechanism with safety. It is correct because the stem describes inflammatory pain, yet pharmacist judgment must integrate renal and cardiovascular risk before recommending systemic NSAID intensification. The discriminator is the coexistence of strong inflammatory clues with high-risk comorbidities. Sources: Lexicomp; FDA labeling; DiPiro.
- C. Recommend duloxetine immediately because all osteoarthritis pain is centrally amplified — Tempting because duloxetine can be used in chronic musculoskeletal pain. It is incorrect because “all osteoarthritis pain is centrally amplified” is too broad, and this acute swollen flare is more directly inflammatory. The discriminator is acute localized swelling after overuse. Sources: DiPiro; Clinical Pharmacology.
- D. Advise doubling acetaminophen to 2,000 mg by mouth every 8 hours because noninflammatory options are safer — Tempting because acetaminophen is often safer than NSAIDs. It is incorrect because the proposed dose is unsafe and exceeds usual maximum daily limits, creating a dose trap. The discriminator is the numerical dosing error. Sources: FDA acetaminophen labeling; Lexicomp.
1.1.1.11 4. Answer: A — The current symptom pattern suggests abnormal neural transmission/modulation rather than simple inflammatory pain alone
- A. The current symptom pattern suggests abnormal neural transmission/modulation rather than simple inflammatory pain alone — Tempting because electric radiation and touch pain are classic neural clues. It is correct because the decisive symptom language points to abnormal transmission/modulation, making old degenerative imaging less important. The discriminator is “electric” plus pain from light touch. Sources: DiPiro; ACCP guidance.
- B. The old x-ray finding proves the pain remains purely nociceptive and should be treated with a different NSAID — Tempting because degenerative spine disease is common. It is incorrect because imaging does not override current neuropathic symptom descriptors. The discriminator is current sensory quality, not old anatomy. Sources: DiPiro; Clinical Pharmacology.
- C. The pain is probably exaggerated because imaging findings are chronic — Tempting if the learner dismisses symptoms when structure seems mild. It is incorrect because allodynia and burning radiation reflect real pain pathway abnormalities. The discriminator is the specific sensory abnormality. Sources: DiPiro; ACCP guidance.
- D. The most appropriate next step is automatic opioid escalation because NSAID therapy failed — Tempting because persistent severe pain can lead to potency thinking. It is incorrect because failure of a peripheral strategy may signal mechanism mismatch, not automatic opioid need. The discriminator is neuropathic-quality pain. Sources: DiPiro; ASHP/ACCP pain management references.
1.1.1.12 5. Answer: A — Focus on central amplification and a multimodal, function-based plan
- A. Focus on central amplification and a multimodal, function-based plan — Tempting because diffuse pain, fatigue, poor sleep, and comorbid migraine/IBS create a recognizable pattern. It is correct because this cluster supports centrally amplified pain processing requiring multimodal rather than purely peripheral management. The discriminator is diffuse pain plus sleep/fatigue with no swollen joints. Sources: DiPiro; ACCP pain management references.
- B. Escalate to scheduled naproxen because the absence of swelling does not matter — Tempting because NSAIDs are familiar analgesics. It is incorrect because the absence of local inflammatory features actually matters a great deal in mechanism selection. The discriminator is diffuse rather than localized inflammatory pain. Sources: AHFS; DiPiro.
- C. Conclude the pain is not clinically significant because inflammatory markers are normal — Tempting if the learner over-relies on labs. It is incorrect because central amplification can produce substantial pain without elevated inflammatory markers. The discriminator is the symptom cluster, not the CRP alone. Sources: DiPiro; ACCP guidance.
- D. Recommend opioid initiation because diffuse pain indicates severe tissue injury — Tempting because diffuse pain may sound severe and refractory. It is incorrect because diffuse pain with poor sleep and fatigue does not imply severe tissue injury and should not trigger reflexive opioid thinking. The discriminator is minimal peripheral inflammatory evidence. Sources: DiPiro; guideline-based pain stewardship principles.
1.1.1.13 6. Answer: A — The ibuprofen is mechanism-plausible for tissue pain but high-risk because CKD and CAD make systemic NSAID continuation unsafe
- A. The ibuprofen is mechanism-plausible for tissue pain but high-risk because CKD and CAD make systemic NSAID continuation unsafe — Tempting because it handles the mixed stem without oversimplifying. It is correct because the patient has true nociceptive fracture pain that could respond to anti-inflammatory therapy, but CKD stage 3b and CAD make systemic NSAID continuation the key medication-safety issue requiring clarification. The discriminator is the combination of inflammatory tissue pain with major NSAID risk factors. Sources: FDA NSAID labeling; Lexicomp; AHFS.
- B. The oxycodone should be stopped immediately because opioids never help mixed pain — Tempting because mixed pain includes a neuropathic component and opioids carry risk. It is incorrect because acute fracture pain may still justify cautious opioid use depending on severity and monitoring; “never” is too absolute. The discriminator is acute localized fracture tenderness. Sources: DiPiro; opioid stewardship guidance.
- C. The acetaminophen should be avoided because localized tenderness proves inflammation only — Tempting because learners may think acetaminophen lacks anti-inflammatory action. It is incorrect because acetaminophen remains a common supportive analgesic in nociceptive pain and localized tenderness does not contraindicate it. The discriminator is lack of hepatic safety concern in the stem. Sources: Lexicomp; FDA acetaminophen labeling.
- D. The burning sensitivity means all nociceptive therapy should be discontinued — Tempting because burning pain sounds mechanistically specific. It is incorrect because the patient has mixed pain, not purely neuropathic pain; tissue-targeted therapy still matters. The discriminator is localized pleuritic tenderness plus fracture context. Sources: DiPiro; ACCP guidance.
1.1.1.14 7. Answer: A — The current shoulder flare most likely reflects peripheral inflammatory transduction despite coexisting neuropathic pain elsewhere
- A. The current shoulder flare most likely reflects peripheral inflammatory transduction despite coexisting neuropathic pain elsewhere — Tempting because it resists overgeneralization. It is correct because a hot swollen shoulder after overuse points to local inflammatory transduction, even though the patient also has separate chronic neuropathic foot pain. The discriminator is the new hot swollen localized joint. Sources: DiPiro; AHFS.
- B. The chronic burning feet prove the shoulder pain must also be neuropathic — Tempting because clinicians may anchor on a known pain diagnosis. It is incorrect because coexisting pain mechanisms can occur in different body sites and must be interpreted separately. The discriminator is the shoulder’s inflammatory features. Sources: DiPiro; ACCP references.
- C. The existing gabapentin makes inflammatory pain impossible — Tempting because a current adjuvant might seem protective. It is incorrect because one medication does not prevent a new inflammatory pain process. The discriminator is the new mechanical-overuse inflammatory presentation. Sources: Clinical Pharmacology; DiPiro.
- D. The best move is to ignore the shoulder mechanism and focus only on total pain score — Tempting because total burden matters clinically. It is incorrect because pathway-specific reasoning is necessary to optimize therapy and avoid mismatch. The discriminator is the distinct symptom language for the shoulder versus feet. Sources: DiPiro; BCPMP-aligned pharmacist problem-solving framework.
1.1.1.15 8. Answer: A — The dominant clue is allodynia and burning radiation, which points away from purely peripheral anti-inflammatory targeting as the sole adjustment
- A. The dominant clue is allodynia and burning radiation, which points away from purely peripheral anti-inflammatory targeting as the sole adjustment — Tempting because celecoxib is a plausible same-category distractor. It is correct because collar-induced pain and burning radiation are neural/modulation clues, so switching within NSAID therapy alone is unlikely to address the dominant mechanism. The discriminator is allodynia plus burning forearm radiation despite improved motion. Sources: DiPiro; AHFS; Clinical Pharmacology.
- B. Celecoxib is never used for musculoskeletal pain — Tempting if the learner thinks the question wants a blanket NSAID rejection. It is incorrect because celecoxib is used in musculoskeletal pain; the issue is mismatch to this specific symptom pattern, not universal inappropriateness. The discriminator is the word “alone” in the rationale. Sources: FDA labeling; AHFS.
- C. Improved range of motion means the pain is psychogenic — Tempting because function improved while pain persisted. It is incorrect because persistent allodynic burning pain can reflect true neural pathway dysfunction even when mechanical range improves. The discriminator is sensory abnormality, not psychogenic inference. Sources: DiPiro; ACCP guidance.
- D. Any chronic pain that persists after NSAID therapy requires opioid conversion — Tempting because persistent pain can provoke escalation thinking. It is incorrect because chronic pain persistence after an NSAID often signals wrong mechanism rather than mandatory opioid use. The discriminator is neuropathic-quality symptom language. Sources: DiPiro; opioid stewardship references.
Keep going with the full BCPMP Prep Course (BCPMP)
You just studied the way members do, in the same lesson interface. Full access unlocks every lesson, the question bank and flashcards for a full year.
One payment · 1 year of access · No auto-renewal