1.1.1 - BCIDP Domain Map
BCIDP Domain Map
What you'll learn
- DOMAIN: Infectious Diseases Pharmacotherapy -> Subskill: classify questions by syndrome-based therapy selection, targeted therapy optimization, and patient-specific regimen design
- DOMAIN: Microbiology and Diagnostics -> Subskill: recognize when culture, susceptibility, rapid diagnostics, and biomarkers drive a medication recommendation
- DOMAIN: PK/PD and Dose Individualization -> Subskill: identify items centered on dosing, route, organ dysfunction, dialysis, and exposure-response reasoning
- DOMAIN: Stewardship and Safety -> Subskill: distinguish de-escalation, duplicate coverage, duration, adverse effects, interactions, and toxicity monitoring questions
- DOMAIN: Prevention, Transitions, and Professional Practice -> Subskill: recognize prophylaxis, IV-to-PO, counseling, and pharmacist-scope framing in board-style stems
- DOMAIN: Infectious Diseases Pharmacotherapy -> select empiric and targeted antimicrobial therapy using syndrome, organism, susceptibility, and host factors
- DOMAIN: Microbiology and Diagnostics -> interpret microbiology, diagnostic tests, and clinical data as they affect medication decisions
- DOMAIN: PK/PD and Dose Design -> individualize dose, interval, route, and monitoring by renal/hepatic function and treatment target
- DOMAIN: Stewardship and Medication Safety -> recommend de-escalation, duration optimization, adverse effect mitigation, and interaction management
- DOMAIN: Prevention and Transitions of Care -> support prophylaxis, discharge regimen feasibility, adherence, and follow-up monitoring
Why it matters
- The BCIDP exam does not reward isolated memorization of drug names; it rewards recognizing which decision framework the stem is testing.
- A domain map lets you quickly sort stem details into useful buckets: bug, host, drug, source, susceptibility, safety, stewardship, and monitoring.
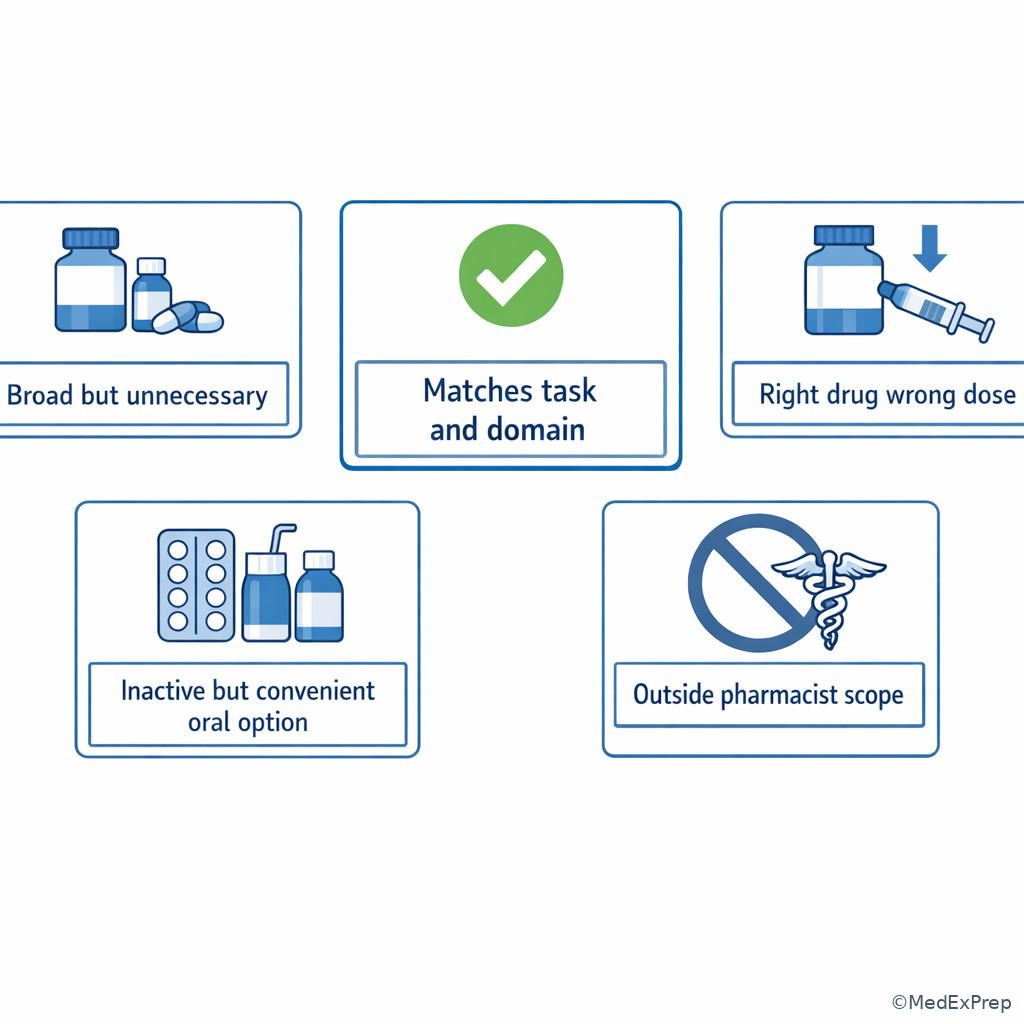
- Many wrong answers are attractive because they fit the syndrome but miss the tested domain, such as choosing a broad agent when the item is really about de-escalation or picking the right drug but wrong renal adjustment.
- If you know the map first, later lessons on scope boundaries and case reasoning become easier to apply under timed conditions.
Key Terms & Must-Know Facts
1.1.1.1 Key terms
- Empiric therapy: initial regimen before full microbiology is available
- Targeted therapy: narrowed regimen based on organism and susceptibility data
- De-escalation: reducing spectrum or number of agents once data support it
- PK/PD: relationship between drug exposure and antimicrobial effect
- Breakpoint: susceptibility threshold used to interpret an MIC
- Stewardship: optimizing therapy while minimizing unnecessary exposure and resistance pressure
- Colonization: organism presence without evidence that treatment is indicated
- Contamination: test result not representing true infection
- IV-to-PO conversion: transition from intravenous to oral therapy when clinically appropriate
- Therapeutic drug monitoring: measuring or estimating exposure to improve efficacy and reduce toxicity
- Special population: patient group requiring tailored selection or dosing, such as dialysis, obesity, pregnancy, transplant, or immunocompromise
- Pharmacist-scope framing: recommend, verify, clarify, monitor, educate, or escalate rather than independently diagnose or perform procedures
1.1.1.2 Must-know facts
- BCIDP stems usually test a medication decision, not abstract microbiology trivia.
- The same infection can generate different question types: empiric choice, targeted narrowing, dose adjustment, toxicity monitoring, or step-down planning.
- If a stem provides cultures and susceptibilities, broad empiric reasoning is often no longer the best framework.
- If renal function, dialysis, weight, or drug levels appear, suspect a PK/PD or dose-design question.
- If multiple active agents are listed, duplicate coverage and stewardship become likely test targets.
- If the patient is clinically improving and can take oral therapy, IV continuation may be the distractor.
- Not every positive culture requires treatment; colonization versus infection is repeatedly tested.
- On BCIDP-style questions, safety and feasibility can overrule theoretical spectrum advantages.
Exam takeaway: First identify whether the stem is testing therapy, diagnostics, PK/PD, stewardship, or prevention before choosing an answer.
flowchart TD
A[Read the stem] --> B{What is the task?}
B --> C[Therapy selection]
B --> D[Microbiology / diagnostics]
B --> E[PK/PD / dose design]
B --> F[Stewardship / safety]
B --> G[Prevention / transition]
C --> C1[Empiric vs targeted]
C --> C2[Bug-host-drug fit]
D --> D1[Culture MIC breakpoint]
D --> D2[Colonization vs infection]
E --> E1[Renal hepatic dialysis]
E --> E2[Exposure target monitoring]
F --> F1[De-escalation duration]
F --> F2[Interaction toxicity duplicate coverage]
G --> G1[IV to PO prophylaxis counseling] Exam takeaway: Mentally sorting stem details into bug, host, drug, and stewardship buckets reduces distractor pull.
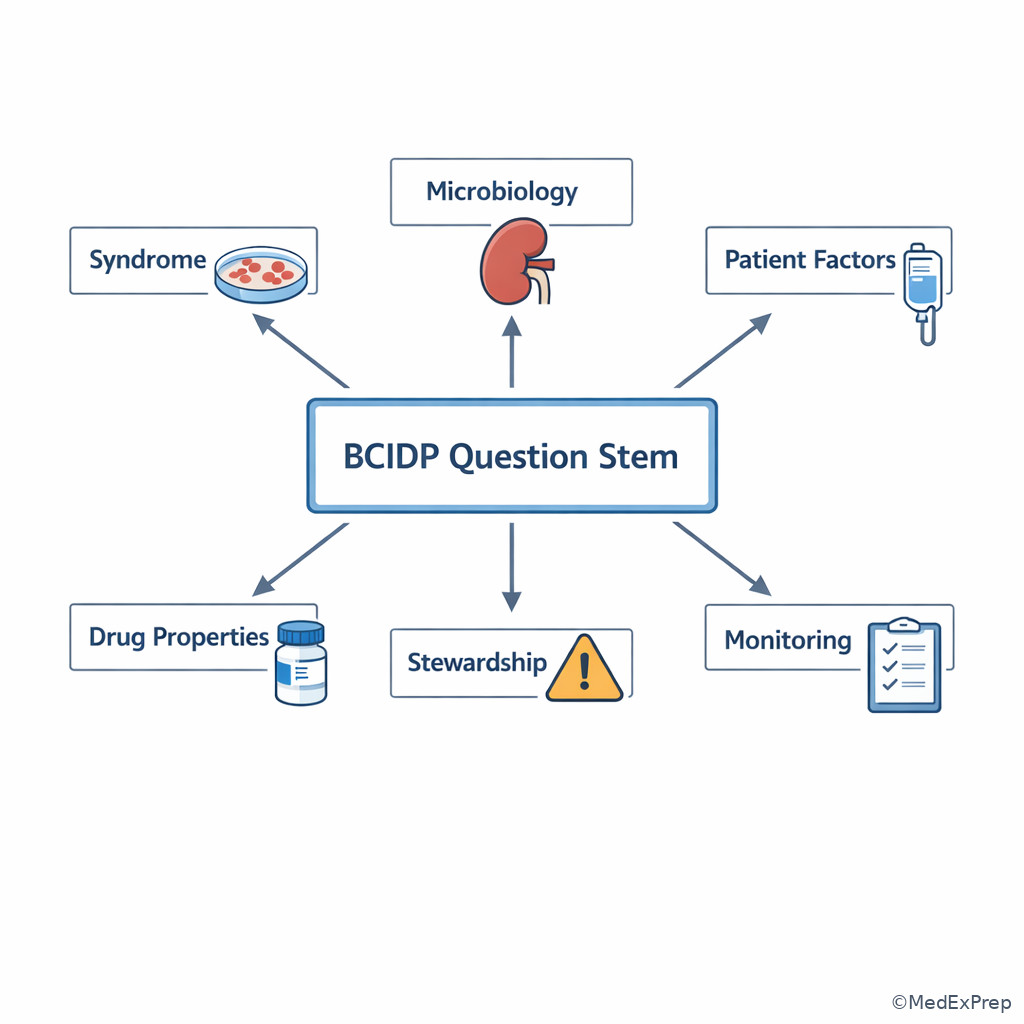
Core content
1.1.1.3 Foundational map: what the BCIDP exam is really asking you to do
A Explanation
The first decision conflict is simple but high yield: Is this a content question or a task question? Many learners read a stem and focus on the disease name. The exam often cares more about the action: choose empiric therapy, optimize targeted therapy, adjust dose, interpret susceptibility, recommend de-escalation, monitor toxicity, or clarify an unsafe plan. The single resolving rule is this: identify the pharmacist action verb before interpreting the details. If the stem asks for the most appropriate next step after culture results, reject answers that stay in empiric mode. If the stem gives a regimen with creatinine clearance and asks what to monitor, reject syndrome-focused answers that ignore drug exposure and toxicity. WHY THIS IS TESTED: candidates often know the infection but miss the tested competency.
For BCIDP, the highest-yield broad buckets are: infectious diseases pharmacotherapy, microbiology/diagnostics, PK/PD dose design, stewardship/safety, and prevention/transitions. This topic is foundational because every later lesson fits somewhere on this map. See Fig 1 for the organizing structure.
B Worked example
A 68-year-old man with type 2 diabetes, stage 3 chronic kidney disease, and atrial fibrillation on apixaban is receiving piperacillin/tazobactam 4.5 g IV every 6 hours for hospital-acquired pneumonia. On day 3, he is afebrile, oxygen need is improving, and sputum culture grows Escherichia coli susceptible to ceftriaxone. Serum creatinine is 1.8 mg/dL, unchanged from baseline. A mild eosinophilia is noted, and the nurse reports the patient prefers to avoid extra IV lines. The question asks for the most appropriate pharmacist recommendation.
Reasoning chain: Identify task: this is not “name the pneumonia bug”; it is a therapy optimization question after microbiology returns. Extract key facts: clinical improvement, culture-directed susceptibility, broad empiric agent still running, stable renal function, no clue demanding antipseudomonal continuation. Apply rule: when culture data permit, move from broad empiric to narrower targeted therapy. Eliminate distractors: continuing piperacillin/tazobactam is tempting because it is active, but spectrum is broader than needed; switching to meropenem would be even broader and unjustified; changing apixaban would address a non-central detail. Verify: ceftriaxone is active, narrower, operationally simpler, and stewardship-concordant.
C Exam trap
D Checkpoint
Question: A pharmacist reviews cefepime 2 g IV every 8 hours started empirically for febrile neutropenia. Blood cultures remain negative, ANC is recovering, and the stem asks for the most appropriate monitoring focus. Which domain is most directly being tested?
- Infectious diseases pharmacotherapy — tempting because cefepime is an antimicrobial choice, but the ask is about what to monitor rather than which agent to select.
- Microbiology and diagnostics — tempting because cultures are mentioned, but the stem does not ask for interpretation of organism identity or susceptibility.
- PK/PD and dose individualization — tempting because cefepime dosing is specified, but no organ function or exposure target detail is offered.
- Stewardship and safety — correct because monitoring ongoing need and appropriate continuation after negative cultures and clinical change is a stewardship-centered pharmacist task.
1.1.1.4 Foundational map: the major BCIDP domains and their signature clues
A Explanation
The next decision conflict is which broad domain best matches the stem clues. You do not need unpublished blueprint percentages to prepare well; you need pattern recognition. Therapy questions usually feature a syndrome, likely pathogens, prior antibiotics, allergies, or susceptibility data. Diagnostics questions foreground specimen quality, culture interpretation, MICs, rapid tests, contamination versus true pathogen, or biomarker limits. PK/PD questions highlight drug, dose, route, infusion strategy, renal function, dialysis, obesity, hepatic dysfunction, or exposure targets. Stewardship questions feature broad-to-narrow choices, duplicate anaerobic coverage, unnecessary MRSA or Pseudomonas coverage, duration, oral step-down, or “do we need to keep treating?” Prevention and transitions questions emphasize prophylaxis, discharge planning, adherence, counseling, access, and follow-up.
The single resolving rule: look for the detail that would be unnecessary unless that domain were being tested. For example, an MIC without a dosing or breakpoint context suggests microbiology interpretation; creatinine clearance placed next to a fully named regimen strongly suggests dose design; a patient tolerating diet, improving, and ready for discharge points toward IV-to-PO or transition planning. See Fig 2 for a high-yield comparison of domain clues.
Exam takeaway: Match the stem’s “extra detail” to the domain being tested, because that detail usually separates the correct answer from a look-alike option.
flowchart LR
A[Stem clues] --> B{Most distinctive clue}
B --> C[Culture MIC rapid test] --> C1[Diagnostics domain]
B --> D[CrCl dialysis weight level] --> D1[PK/PD domain]
B --> E[Broader than needed duplicate therapy duration] --> E1[Stewardship domain]
B --> F[Discharge oral option adherence] --> F1[Prevention transition domain]
B --> G[Syndrome likely pathogens allergy prior exposure] --> G1[Therapy selection domain] B Worked example
A 54-year-old woman with obesity, rheumatoid arthritis on prednisone, and chronic kidney disease receives vancomycin 1.25 g IV every 12 hours plus ceftriaxone 2 g IV daily for suspected meningitis. Her CSF culture later grows penicillin-susceptible Streptococcus pneumoniae. Serum creatinine has increased from 0.8 to 1.4 mg/dL. The stem includes a vancomycin concentration and asks for the best therapy adjustment. There is also an incidental note of chronic sinusitis.
Reasoning chain: Identify task: therapy adjustment after culture data with a safety signal. Extract key facts: definitive pathogen with narrower treatment option, vancomycin nephrotoxicity risk becoming relevant, susceptibility allows de-escalation. Apply rule: once susceptibility supports a narrower beta-lactam, vancomycin can often be discontinued. Eliminate distractors: changing vancomycin to a different dosing interval is tempting because the level is provided, but the culture result changes the entire need for vancomycin; escalating ceftriaxone dose without indication misses the targeted question. Verify: the tested domain overlaps therapy and stewardship, with safety reinforcing the narrow choice.
C Exam trap
D Checkpoint
Question: Which stem detail most strongly signals that a BCIDP item is primarily testing a microbiology/diagnostics domain rather than therapy selection?
- Recent exposure to levofloxacin 750 mg PO daily for 5 days — tempting because prior exposure affects therapy choice, but it points more to empiric selection and resistance risk than diagnostics.
- A bronchoalveolar lavage culture with an MIC and breakpoint interpretation — correct because MIC and susceptibility interpretation are diagnostic data that directly frame the medication decision.
- Need for oral step-down at discharge tomorrow — tempting because it changes the regimen, but it is a transitions-of-care clue.
- Creatinine clearance of 24 mL/min while receiving cefepime 2 g IV every 8 hours — tempting because drug and dose are central, but that is a PK/PD dose-adjustment clue.
- The most common signal for a PK/PD domain is the presence of renal function, dialysis, or exposure target.
- True or False: A positive culture automatically means the item is testing microbiology rather than stewardship. False.
- Name the 3 quick clue words for stewardship stems: broad, duplicate, duration.
1.1.1.5 Application: how stems blend syndrome, bug, host, and drug information
A Explanation
Once you identify the domain, the next conflict is which facts matter most within the stem. BCIDP questions often contain noise: age, comorbidities, old allergies, mild lab abnormalities, and operational details. The pharmacist must choose between every available fact and the decision-driving fact. A useful internal hierarchy is: task first, then syndrome/source, then microbiology, then host modifiers, then drug-specific safety and feasibility. If the question is targeted therapy, organism and susceptibility outrank remote epidemiology. If the question is dosing, organ function and modality outrank the syndrome name. If the question is oral step-down, bioavailability and source control feasibility outrank the fact that IV therapy “feels stronger.” WHY THIS IS TESTED: the exam is built to reward disciplined prioritization, not total data absorption.
Use a mental grid: syndrome tells you where the drug must work; bug tells you what it must cover; host tells you whether standard choices are safe and feasible; drug tells you whether the regimen can achieve exposure without undue harm. See Fig 3 for a comparison framework. This lesson is not asking you to master every syndrome yet; it is teaching where later syndrome lessons will plug into your reasoning map.
Exam takeaway: Prioritize the fact that changes action, not the fact that merely sounds clinically interesting.
flowchart TD
A[Question asks for best regimen decision] --> B[Syndrome or source]
B --> C[Likely or confirmed bug]
C --> D[Host modifiers]
D --> E[Drug fit]
E --> F[Check stewardship and monitoring]
D --> D1[Renal function allergy immunocompromise route]
E --> E1[PK PD interactions toxicity penetration]
Exam takeaway: A structured stem-sorting approach helps you downgrade distracting details and elevate the one fact that changes therapy.
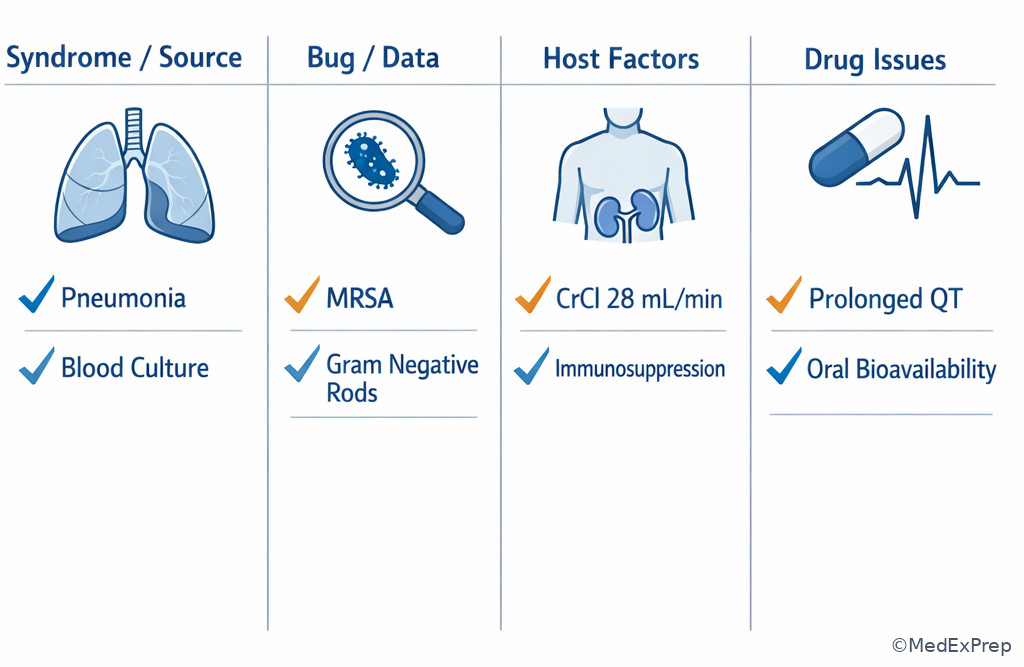
B Worked example
A 73-year-old woman with cirrhosis, chronic kidney disease, and a remote rash with amoxicillin is admitted with pyelonephritis. She was started on cefepime 2 g IV every 12 hours. Urine culture grows ESBL-producing E. coli. She has a QTc of 510 ms, mild thrombocytopenia, and nausea but is otherwise improving. The question asks for the best targeted regimen recommendation.
Reasoning chain: Identify task: targeted therapy recommendation. Extract key facts: pyelonephritis source, confirmed ESBL organism, current cefepime may be unreliable depending on susceptibility context and syndrome, QTc makes fluoroquinolone less appealing, renal function and liver disease affect dosing but do not change the central bug-drug fit. Apply rule: in serious ESBL infections, choose an agent with reliable activity and supportive evidence rather than being distracted by non-central details. Eliminate distractors: oral levofloxacin is tempting for convenience but QTc and resistance concerns matter; piperacillin/tazobactam is tempting if reported susceptible, but source and ESBL reliability are critical; ceftriaxone is too narrow for ESBL. Verify: a carbapenem-based targeted recommendation best fits the domain.
C Exam trap
D Checkpoint
Question: A stem includes linezolid 600 mg IV every 12 hours, platelet count trend, serotonin-active home medications, and no culture data yet. What is the most likely primary domain being tested?
- Therapy selection — tempting because linezolid choice matters, but the supporting clues emphasize adverse effects and interactions rather than organism fit.
- Microbiology/diagnostics — tempting because cultures are not final, but there is no lab interpretation task.
- Stewardship and safety — correct because platelets and serotonergic co-medications direct attention to toxicity and interaction management.
- Prevention and transitions — tempting because linezolid has oral bioavailability, but discharge feasibility is not the stem’s central clue.
1.1.1.6 Application: pharmacist scope, task verbs, and answer-choice filtering
A Explanation
BCIDP is a pharmacist board exam, so another major decision conflict is which answers remain inside pharmacist role. The exam wants consultant-level medication judgment, not unsupported independent diagnosis or procedure-level action. Accept verbs such as recommend, assess, clarify, verify, adjust, monitor, educate, de-escalate, convert to oral therapy, document a plan, and escalate safety concerns. Reject answers that require acting as an unrestricted prescriber or proceduralist unless the stem explicitly grants collaborative authority. The single resolving rule is: if the action is outside pharmacist scope, choose the answer that appropriately recommends, clarifies, or escalates instead. WHY THIS IS TESTED: high-performing clinicians can still miss exam items by picking an answer that is medically sensible but role-inappropriate.
This matters even when the drug choice itself is correct. For example, “write the order for line removal” is a trap if the pharmacist should instead recommend line evaluation or alert the primary team. Likewise, if no diagnosis has been established, the pharmacist’s role is often to interpret the available microbiology and medication implications, not independently make the final diagnosis. This domain map therefore includes scope framing as a cross-cutting filter over every other domain.
Exam takeaway: When multiple answers seem clinically reasonable, prefer the one framed as a pharmacist recommendation, clarification, monitoring step, or escalation.
flowchart TD
A[Answer choice] --> B{Within pharmacist role?}
B -->|Yes| C[Recommend optimize monitor educate]
B -->|No| D[Reject unless explicit authority given]
C --> E{Safe and stewardship aligned?}
E -->|Yes| F[Keep in consideration]
E -->|No| G[Reject]
D --> H[Prefer clarify or escalate option] Exam takeaway: Distinguish medication-optimization actions from prescriber-only or procedural actions to avoid avoidable misses.
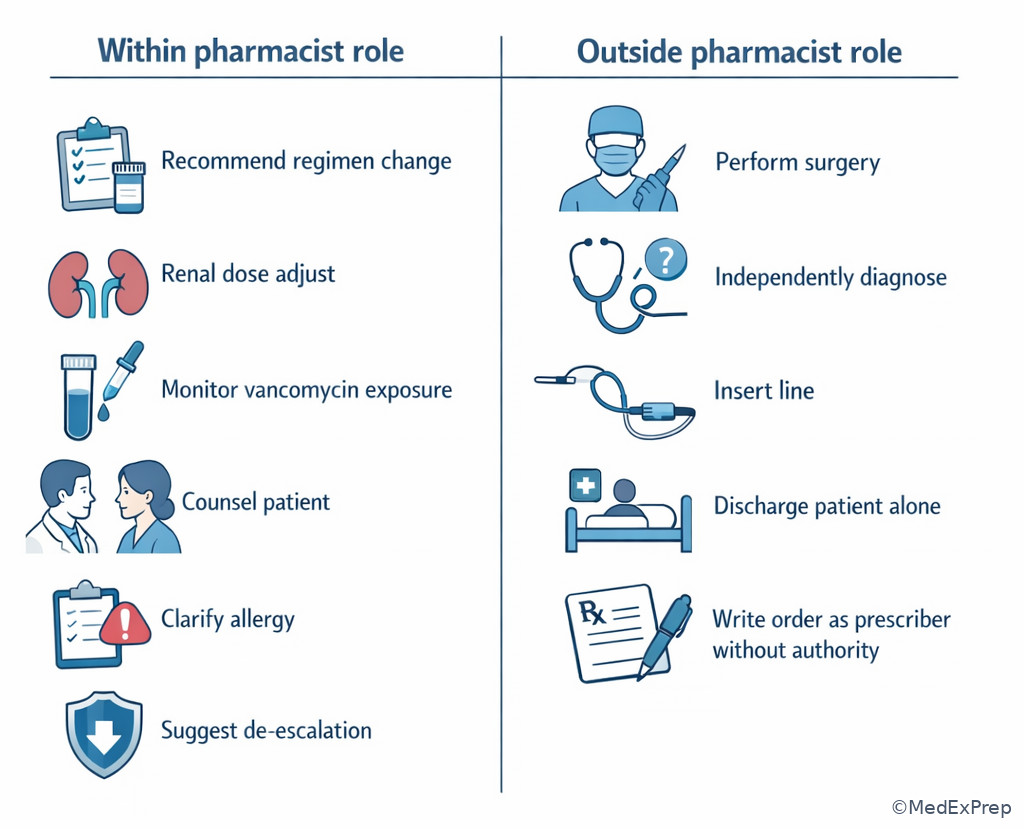
B Worked example
A 60-year-old kidney transplant recipient on tacrolimus is admitted with candidemia and receives micafungin 100 mg IV daily. Repeat blood cultures are pending. He has a tunneled central line, hypertension, and mild diarrhea. The item asks what the pharmacist should do next. One option is “remove the line immediately”; another is “recommend urgent line evaluation and communicate persistent candidemia risk while optimizing antifungal therapy.”
Reasoning chain: Identify task: pharmacist next step. Extract key facts: candidemia requires medication optimization and urgent multidisciplinary follow-up; line management matters but is not a pharmacist-performed procedure. Apply rule: stay within role while still acting decisively. Eliminate distractors: “remove the line immediately” is medically adjacent but outside pharmacist action; “continue current therapy with no communication” ignores the seriousness; “switch to fluconazole now” is premature without stability and susceptibility context. Verify: the pharmacist should recommend appropriate therapy and escalate line/source concerns to the treating team.
C Exam trap
D Checkpoint
Question: Which answer is most likely to be correct on a BCIDP item if no collaborative practice authority is specified?
- Write an order for meropenem 2 g IV every 8 hours by extended infusion — tempting because the regimen may be appropriate, but independent prescribing is not assumed.
- Perform incision and drainage, then narrow therapy — tempting because source control matters, but procedural management is outside pharmacist scope.
- Recommend meropenem 2 g IV every 8 hours by extended infusion and document renal-dose reassessment needs — correct because it stays within pharmacist medication-management role.
- Finalize the diagnosis of osteomyelitis before adjusting therapy — tempting because diagnosis matters, but the pharmacist generally acts on provided data and collaborates rather than independently establishing the diagnosis.
- Fill in the blank: If the stem asks what the pharmacist should do, procedural answers are usually ______. outside scope
- True or False: The most clinically aggressive answer is usually the best BCIDP answer. False.
- Name 3 in-scope verbs: recommend, clarify, monitor.
1.1.1.7 Integration: building an exam-day question triage system
A Explanation
The final integration task is combining all prior sections into a rapid triage system. Under timed conditions, you need a repeatable algorithm: identify the ask, classify the domain, rank the stem facts, filter by pharmacist scope, then verify the choice for efficacy, safety, feasibility, and stewardship. The decision conflict here is speed versus thoroughness. Moving too fast leads to superficial pattern matching; moving too slowly wastes time on noise. The single resolving rule is: perform the same short sequence on every item, even if you think you already know the answer. WHY THIS IS TESTED: the exam is less about memorizing all facts at once and more about consistently applying a medication-decision workflow.
This triage system anticipates the next course topic, Case Reasoning Framework, where you will expand the method into a more formal bug-host-drug-source analysis. At this stage, your goal is not exhaustive management. Your goal is to quickly identify what kind of pharmacist judgment the question demands and prevent classic misses such as broader-than-needed therapy, wrong dose in renal dysfunction, unsafe interaction, or out-of-scope action. See Fig 5 for the exam-day algorithm.
Exam takeaway: Use the same five-step sequence on every item to convert complex vignettes into one pharmacist-level decision.
flowchart TD
A[Read stem] --> B[Identify pharmacist task]
B --> C[Assign domain]
C --> D[Rank key facts]
D --> E[Apply scope filter]
E --> F[Choose answer]
F --> G[Verify efficacy safety feasibility stewardship]
Exam takeaway: A fixed workflow improves speed without sacrificing the single discriminating clue in complex vignettes.
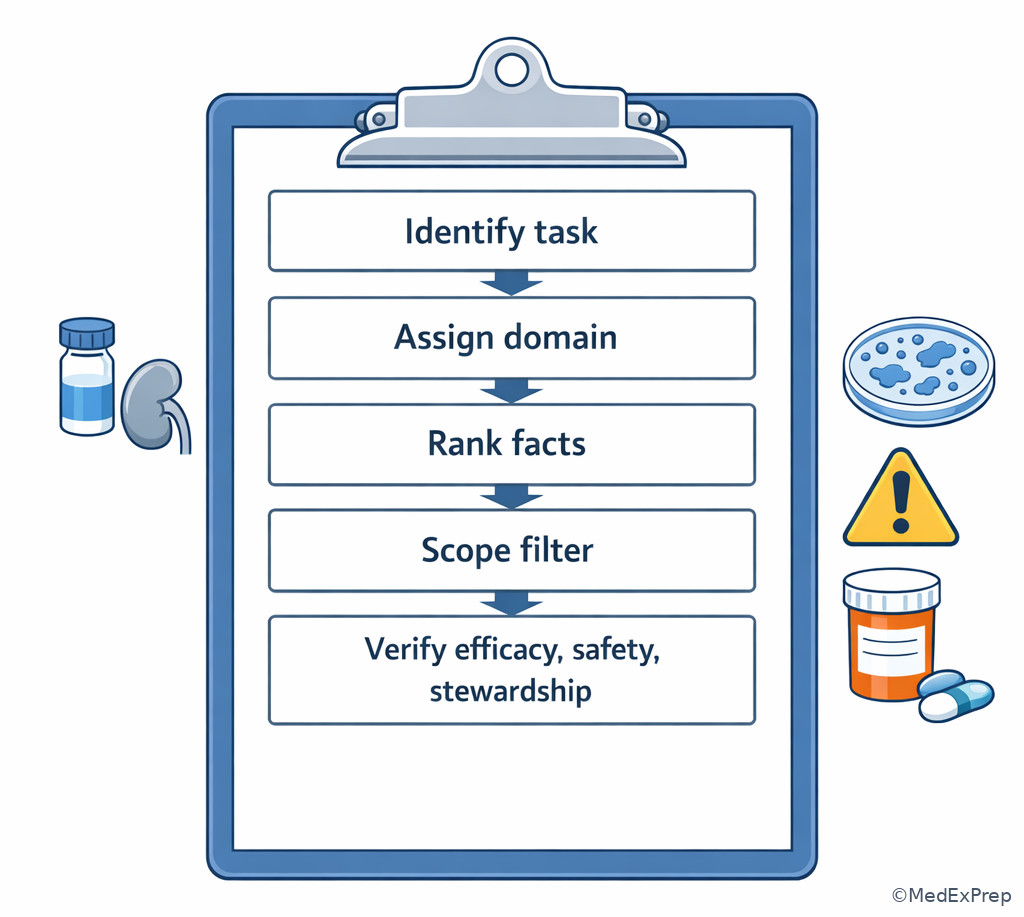
B Worked example
A 49-year-old man with obesity, uncontrolled diabetes, and hemodialysis dependence is receiving daptomycin 8 mg/kg IV after each dialysis session for MRSA bacteremia. His CK is mildly elevated, blood cultures have cleared, and he is eager for discharge. The stem includes home simvastatin use, a tunneled catheter, and a question asking for the most appropriate pharmacist follow-up recommendation.
Reasoning chain: Step 1 task: follow-up recommendation. Step 2 domain: safety and monitoring, with some transitions-of-care overlap. Step 3 key facts: daptomycin exposure in dialysis, CK elevation, statin interaction risk, bacteremia follow-up. The desire for discharge is noise unless it changes feasibility. Step 4 scope: pharmacist should recommend monitoring and therapy optimization, not independently discharge or remove hardware. Step 5 verify: CK and muscle toxicity monitoring, statin review, dialysis timing, and coordination with the team are most appropriate. The domain map prevents a common miss: choosing an early oral step-down concept that does not fit bacteremia.
C Exam trap
D Checkpoint
Question: Which verification step should always occur after you think you have the right answer to a BCIDP item?
- Confirm the answer is the broadest active regimen — tempting because severe infections often start broadly, but broadest is not the universal goal.
- Confirm the answer fits efficacy, safety, feasibility, and stewardship — correct because the final check protects against close-call distractors that fail on one of these dimensions.
- Confirm the answer uses an intravenous formulation whenever available — tempting because IV therapy feels stronger, but oral options may be preferred when appropriate.
- Confirm the answer solves every possible medical issue in the vignette — tempting because comprehensive thinking feels safe, but the exam usually targets one pharmacist decision.
Exam Traps & Differentiators
Most common wrong answer and why: choosing the clinically active regimen that does not match the tested domain. Example: keeping a broad empiric drug after susceptibilities return because it is active, when the item is actually about de-escalation.
| Stem says... | Think... | Common distractor | Single discriminator |
|---|---|---|---|
| Culture, MIC, breakpoint, rapid diagnostic | Microbiology/diagnostics domain | Answering as if still purely empiric | The lab detail exists to change the medication decision |
| CrCl, dialysis, weight, level, infusion strategy | PK/PD dose design | Choosing the right drug with the wrong dose | Organ function or exposure target is the tested variable |
| Improving, cultures finalized, spectrum broad | Stewardship/de-escalation | Continuing broad therapy “because it works” | New data allow safe narrowing |
| Discharge, tolerating PO, insurance, adherence | Transition/IV-to-PO | Preferring IV because it feels stronger | Feasibility and bioavailability now matter most |
| Question asks what the pharmacist should do | Scope framing filter | Picking a procedural or prescriber-only action | Choose recommend/clarify/monitor/escalate wording |
| Looks similar | But is not the same as | How to tell |
|---|---|---|
| Positive culture result | Question about microbiology domain | If the ask is whether to narrow, stop, or monitor therapy, it may be stewardship instead |
| Detailed drug regimen in the stem | PK/PD question | If no organ function, level, or dosing constraint appears, the regimen may just be context for safety or therapy selection |
| Desire for discharge | Automatic oral step-down | Source, bacteremia status, absorption, and agent bioavailability still decide |
| Urgent infection | Permission to act outside pharmacist role | Urgency changes communication speed, not professional boundaries |
- If the stem says “susceptibilities returned” think targeted therapy or de-escalation.
- If the stem says “creatinine clearance is 18 mL/min” think dose design before spectrum.
- If the stem says “improving and tolerating oral intake” think transition feasibility, not reflexive IV continuation.
- If the stem says “what should the pharmacist do next” think recommend, clarify, monitor, or escalate.
- If the stem says “positive culture from a low-quality specimen” think contamination/colonization risk before treatment escalation.
Exam takeaway: Most close-call wrong answers fail because they solve the wrong domain problem, not because they are obviously inactive.
Tables
| Domain | What it usually tests | Signature stem clues | Typical pharmacist action |
|---|---|---|---|
| Infectious diseases pharmacotherapy | Empiric or targeted agent selection | Syndrome, organism, allergy, prior antibiotics, susceptibility | Recommend the best regimen or narrowing strategy |
| Microbiology and diagnostics | Interpretation of culture, rapid test, MIC, specimen quality | Breakpoint, contaminant, colonization, rapid organism ID | Explain how the result changes therapy |
| PK/PD and dose individualization | Dose, interval, infusion, dialysis, monitoring target | CrCl, RRT modality, obesity, level, AUC, infusion duration | Adjust regimen and monitoring plan |
| Stewardship and safety | De-escalation, duration, duplicate coverage, toxicity, interactions | Improving patient, finalized cultures, broad therapy, adverse effect trend | Recommend safer, narrower, shorter, or better-monitored therapy |
| Prevention and transitions | Prophylaxis, IV-to-PO, discharge plan, adherence, counseling | Tolerating oral intake, discharge tomorrow, prophylaxis indication, access issue | Select feasible regimen and follow-up plan |
| Question type | Choose this framework | Reject this reflex |
|---|---|---|
| Empiric therapy | Syndrome + likely pathogens + host risk | Over-focusing on a nonfinal culture clue |
| Targeted therapy | Confirmed organism + susceptibility + site | Continuing the original broad regimen automatically |
| Dose adjustment | Drug exposure + organ function + modality | Keeping standard dose because the drug choice is correct |
| De-escalation | Narrowest effective regimen | “Don’t change what’s working” |
| IV-to-PO conversion | Clinical improvement + oral option quality + source considerations | Assuming IV is always superior |
| Safety/interaction | Drug-specific toxicity risk + comedications | Ignoring one red-flag lab or home medication |
| Differential category | Primary cue | Best next pharmacist mindset |
|---|---|---|
| Therapy selection vs stewardship | Broad regimen still active after cultures return | Ask whether narrower therapy is now justified |
| Diagnostics vs therapy | MIC or rapid test included in stem | Interpret what the test means before changing drugs |
| PK/PD vs safety | Dose details plus organ dysfunction or level | Decide whether the issue is exposure adequacy, toxicity, or both |
| Transition vs inpatient optimization | Discharge planning language | Confirm source, oral bioavailability, adherence, and monitoring feasibility |
| In-scope vs out-of-scope | Answer options include procedures or independent orders | Prefer collaborative pharmacist wording |
Algorithm / Approach
Exam takeaway: The best BCIDP answers survive a final check for efficacy, safety, feasibility, and stewardship within pharmacist scope.
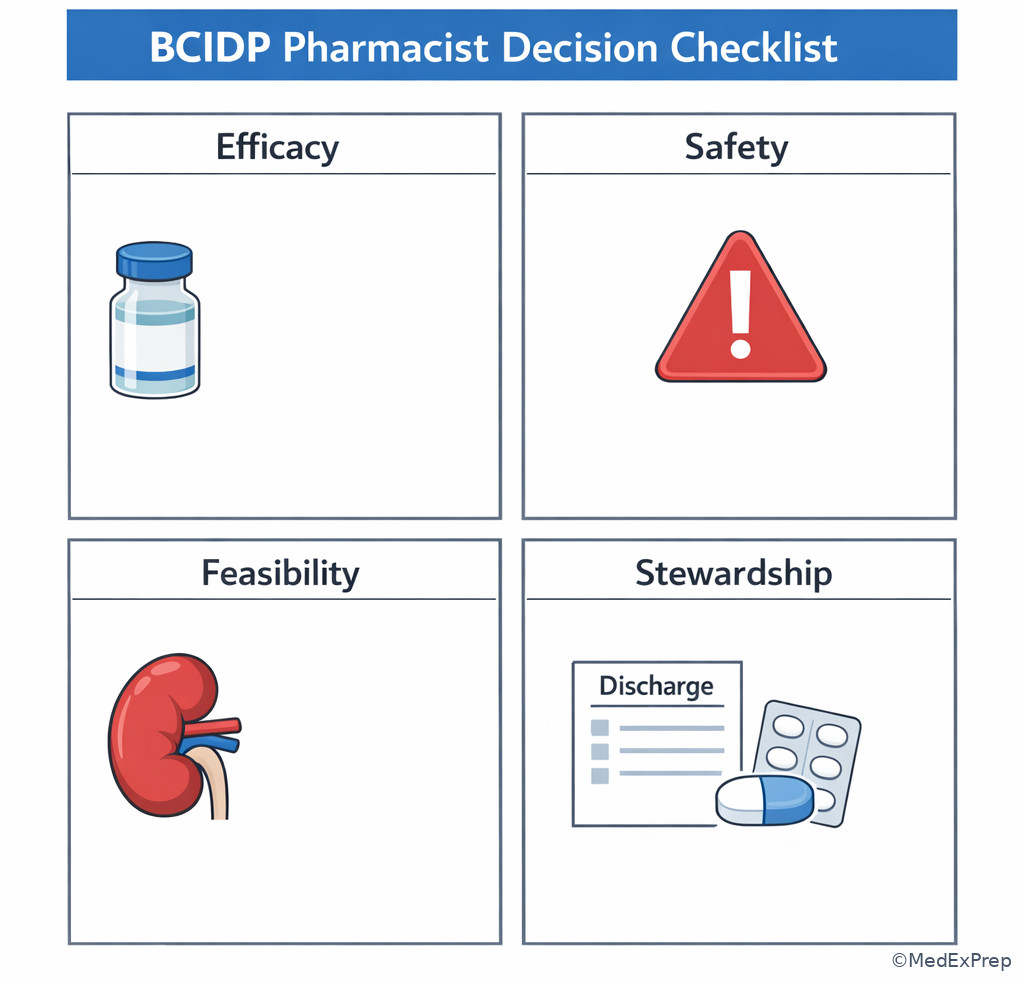
Use this algorithm when you feel uncertain. It is especially valuable early in the course because it prevents you from overcommitting to one content area before you understand the full exam structure. See Fig 5 and Fig 6 for the exam-day flow and final checklist.
Rapid Review
- Task recognition → the verb matters more than the diagnosis label
- Targeted therapy → finalized susceptibility data outrank empiric habit
- PK/PD item → CrCl, dialysis, weight, or levels are the discriminator
- Diagnostics item → MIC/breakpoint details exist to change medication meaning
- Stewardship item → broad but active is often still wrong
- Transition item → oral feasibility can beat unnecessary IV continuation
- Scope filter → recommend/clarify/escalate beats procedural action
- Noise in vignettes → prioritize the fact that changes action
- Culture positive → does not automatically mean “treat more”
- Correct drug, wrong dose → still wrong on BCIDP
- Improving patient → asks for reassessment, not autopilot continuation
- Answer verification → check efficacy, safety, feasibility, stewardship
Self-check quiz
1. A pharmacist reviews ceftriaxone 2 g IV every 24 hours for community-acquired pneumonia. The stem provides no renal function issue, no culture data, and asks which broad BCIDP domain is most likely being tested when the learner must choose the initial regimen. Which is the best answer?
- Infectious diseases pharmacotherapy
- Microbiology and diagnostics
- PK/PD and dose individualization
- Prevention and transitions of care
2. A pharmacist reviews cefepime 2 g IV every 8 hours in a patient with creatinine clearance 18 mL/min and asks which domain is most directly signaled by the presence of renal function in the stem. Which is the best answer?
- Stewardship and safety
- PK/PD and dose individualization
- Prevention and transitions of care
- Microbiology and diagnostics
3. A 65-year-old man with COPD and chronic kidney disease is receiving piperacillin/tazobactam 4.5 g IV every 6 hours for pneumonia. Sputum culture now shows Haemophilus influenzae susceptible to ceftriaxone; he is afebrile and improving. The pharmacist is asked for the most appropriate next step. Which framework should drive the answer?
- Continue broad empiric therapy because the patient improved on it
- Targeted therapy and stewardship de-escalation
- Primary prevention and prophylaxis planning
- Independent diagnostic confirmation of pneumonia etiology
4. A 58-year-old woman with obesity and diabetes is receiving vancomycin 1 g IV every 12 hours for MRSA skin infection. The stem includes an AUC estimate, serum creatinine trend, and no new culture issue. It asks for the most appropriate regimen adjustment. Which is the best primary domain?
- PK/PD and dose individualization
- Prevention and transitions
- Microbiology and diagnostics
- Diagnostic imaging escalation
5. A 72-year-old woman with atrial fibrillation on dofetilide and chronic sinusitis is prescribed levofloxacin 750 mg PO daily at discharge for a urinary infection. The stem asks what the pharmacist should address before finalizing the plan. Which framework is most appropriate?
- Stewardship and safety, especially interaction review
- Microbiology only, because urinary infections are culture-driven
- Prevention only, because discharge is mentioned
- Independent diagnosis of pyelonephritis severity
6. A 47-year-old liver transplant recipient on tacrolimus receives voriconazole 6 mg/kg IV every 12 hours for 2 doses then 4 mg/kg IV every 12 hours for probable invasive aspergillosis. The stem includes tacrolimus concentration, QTc 505 ms, mild visual changes, and a plan for discharge in several days. The pharmacist is asked for the most important recommendation now. Which answer best reflects correct domain recognition and pharmacist scope?
- Prioritize discharge conversion because oral therapy will simplify care
- Recommend urgent review of interaction and toxicity with dose/monitoring adjustment considerations
- Finalize the diagnosis of aspergillosis before commenting on therapy
- Write a standing order to hold tacrolimus indefinitely
7. A 70-year-old man on intermittent hemodialysis is receiving daptomycin 10 mg/kg IV after each dialysis session for VRE bacteremia. CK rises from 110 to 880 units/L, he reports new thigh pain, and his home rosuvastatin was resumed yesterday. Blood cultures are negative. The item asks for the best pharmacist recommendation. Which option shows the correct BCIDP reasoning structure?
- Continue daptomycin unchanged because blood cultures are now negative
- Recommend assessing daptomycin toxicity risk, reviewing statin coadministration, and escalating the CK concern to the team
- Switch automatically to oral linezolid because discharge may be possible this week
- Remove the dialysis catheter immediately
8. A 62-year-old woman with rheumatoid arthritis on prednisone and stage 4 CKD is receiving cefepime 2 g IV every 8 hours plus metronidazole 500 mg IV every 8 hours for intra-abdominal infection after source control. She is improving, cultures show susceptible E. coli and Bacteroides fragilis, and discharge to home OPAT is being discussed. The pharmacist is asked for the most appropriate next recommendation. Which option best applies the domain map?
- Keep both agents because improvement proves the current regimen is optimal
- Recommend reassessing dose for CKD and narrowing to the simplest effective regimen supported by culture data
- Focus only on discharge logistics because home therapy planning is mentioned
- Independently determine whether the surgery achieved adequate source control before changing therapy
Answer key
1.1.1.8 Question 1
Correct answer: A. Infectious diseases pharmacotherapy
- A. Tempting because the stem centers on ceftriaxone selection for a syndrome; correct because choosing an initial regimen is classic therapy-selection framing. The single clue is the ask to choose the initial regimen. Source support: DiPiro and ACCP-style pharmacotherapy frameworks emphasize syndrome-, pathogen-, and host-based regimen selection.
- B. Tempting because pneumonia often involves cultures, but incorrect because no diagnostic interpretation detail such as MIC, specimen quality, or rapid test is provided. The single clue eliminating it is the absence of microbiology interpretation data. Source support: Diagnostic domains hinge on test interpretation, not merely infection presence.
- C. Tempting because ceftriaxone is a drug with dosing, but incorrect because renal function or exposure targets are not presented as decision drivers. The single clue eliminating it is lack of dose-design data. Source support: PK/PD questions require dose-relevant patient-specific variables.
- D. Tempting because route and discharge can matter in therapy, but incorrect because nothing in the stem focuses on prophylaxis, transition, or oral conversion. The single clue eliminating it is that the choice is about initial treatment, not transition. Source support: Prevention/transition items require adherence, discharge, or prophylaxis framing.
1.1.1.9 Question 2
Correct answer: B. PK/PD and dose individualization
- A. Tempting because incorrect dosing can create toxicity, but incorrect because the stem’s most distinctive clue is creatinine clearance linked to a named cefepime regimen. The single discriminator is renal function data. Source support: Lexicomp and FDA labeling tie cefepime dose adjustment to renal function.
- B. Correct because a specified regimen plus CrCl 18 mL/min directly signals dose individualization. The single clue is explicit renal impairment. Source support: AHFS, Lexicomp, and pharmacotherapy texts identify renal function as a core dosing determinant.
- C. Tempting because route feasibility can matter later, but incorrect because there is no discharge or oral-conversion context. The single clue eliminating it is absent transition language.
- D. Tempting because cultures may later matter, but incorrect because no MIC, susceptibility, or specimen issue is given. The single clue eliminating it is lack of microbiology interpretation data.
1.1.1.10 Question 3
Correct answer: B. Targeted therapy and stewardship de-escalation
- A. Tempting because active empiric therapy led to clinical improvement; incorrect because culture data now support narrowing, and stewardship requires reassessment of broad coverage. The single clue is susceptible H. influenzae with patient improvement. Source support: IDSA stewardship principles favor narrowing once cultures support it.
- B. Correct because the combination of finalized culture data and ongoing broad therapy makes targeted de-escalation the governing framework. The single clue is organism-specific susceptibility. Source support: stewardship guidelines and pharmacotherapy texts emphasize culture-directed narrowing.
- C. Tempting because step-down planning often comes later, but incorrect because prophylaxis is not the issue. The single clue eliminating it is the active treatment question after cultures return.
- D. Tempting because diagnosis matters conceptually, but incorrect because the pharmacist is not being asked to independently diagnose; the syndrome is already being treated and microbiology is available. The single clue eliminating it is pharmacist recommendation framing.
1.1.1.11 Question 4
Correct answer: A. PK/PD and dose individualization
- A. Correct because vancomycin AUC and serum creatinine are classic exposure-and-toxicity variables used to optimize dosing. The single clue is the AUC estimate paired with renal trend. Source support: vancomycin consensus guidance and Lexicomp dosing recommendations prioritize exposure-based adjustment.
- B. Tempting because some vancomycin cases end with oral step-down discussion, but incorrect because no discharge or route-conversion issue is presented. The single clue eliminating it is the monitoring focus.
- C. Tempting because MRSA is a microbiologic concept, but incorrect because no new organism interpretation or susceptibility challenge is present. The single clue eliminating it is that the stem asks for regimen adjustment using PK data.
- D. Tempting because severe skin infection sometimes prompts imaging, but incorrect and outside the tested medication framework. The single clue eliminating it is that the item asks for a regimen adjustment, not a procedural/diagnostic escalation. Source support: pharmacist role is medication optimization.
1.1.1.12 Question 5
Correct answer: A. Stewardship and safety, especially interaction review
- A. Correct because dofetilide plus levofloxacin raises an interaction and QT-risk concern, making safety review the key pharmacist task before plan finalization. The single clue is the named interacting home medication. Source support: FDA labeling, Lexicomp interaction monographs, and Clinical Pharmacology support significant QT interaction concern.
- B. Tempting because urinary infections are often culture-guided, but incorrect because the deciding clue is a drug interaction rather than culture interpretation. The single clue eliminating it is dofetilide use.
- C. Tempting because discharge is mentioned, but incorrect because transition planning is not the immediate priority if the regimen may be unsafe. The single clue eliminating it is the high-risk interaction.
- D. Tempting because disease severity can affect route and duration, but incorrect because independently diagnosing severity is not the pharmacist’s primary role in this framing. The single clue eliminating it is “before finalizing the plan,” which points to medication safety review.
1.1.1.13 Question 6
Correct answer: B. Recommend urgent review of interaction and toxicity with dose/monitoring adjustment considerations
- A. Tempting because voriconazole has an oral formulation and discharge is mentioned; incorrect because tacrolimus interaction, QTc prolongation, and visual adverse effects demand immediate safety-focused review first. The single clue is the cluster of toxicity/interaction data. Source support: voriconazole FDA labeling, Lexicomp, and Aspergillosis guidance emphasize interaction monitoring and toxicity management.
- B. Correct because the question asks for the most important recommendation now, and the provided tacrolimus concentration and QTc specifically signal a pharmacist safety/PK-interaction action within scope. The single clue is tacrolimus plus voriconazole. Source support: FDA label, Clinical Pharmacology, and guideline-based antifungal management support close interaction/toxicity monitoring.
- C. Tempting because certainty of diagnosis matters in invasive fungal disease, but incorrect because the stem already provides treatment context and asks for medication-focused action. The single clue eliminating it is the detailed drug-toxicity data already present.
- D. Tempting because tacrolimus may need major adjustment, but incorrect because writing a standing order assumes prescriptive authority and the word “indefinitely” is unsupported. The single clue eliminating it is pharmacist-scope framing without explicit collaborative authority.
1.1.1.14 Question 7
Correct answer: B. Recommend assessing daptomycin toxicity risk, reviewing statin coadministration, and escalating the CK concern to the team
- A. Tempting because culture clearance suggests efficacy; incorrect because the current problem is toxicity risk, not persistent infection. The single clue is CK 880 units/L with myalgias. Source support: daptomycin labeling and Lexicomp emphasize CK and muscle symptom monitoring.
- B. Correct because the stem’s decisive clues are elevated CK, muscle pain, hemodialysis dosing context, and concurrent statin exposure; the pharmacist should recommend safety reassessment and escalation. The single clue is symptomatic CK elevation. Source support: FDA labeling, AHFS, and drug information references support addressing daptomycin-associated myopathy risk and interacting factors.
- C. Tempting because linezolid is an oral VRE-active alternative and discharge is mentioned; incorrect because the stem asks for the best recommendation now, and toxicity evaluation comes before reflexive transition decisions. The single clue eliminating it is acute CK/myalgia concern.
- D. Tempting because catheter management may matter in bacteremia, but incorrect because immediate catheter removal is a procedural/team action, not the pharmacist’s direct act. The single clue eliminating it is the role framing.
1.1.1.15 Question 8
Correct answer: B. Recommend reassessing dose for CKD and narrowing to the simplest effective regimen supported by culture data
- A. Tempting because improvement on current therapy suggests adequacy; incorrect because the stem gives both CKD dosing relevance and culture data that support stewardship reassessment. The single clue is combined renal impairment plus finalized organisms. Source support: stewardship principles and renal dosing references require reevaluation of both dose and spectrum.
- B. Correct because the domain map shows this is an integration item: PK/PD due to stage 4 CKD, plus stewardship due to culture-directed narrowing and simplification for ongoing care. The single clue is the combination of kidney function and finalized susceptible organisms. Source support: Lexicomp/AHFS renal dosing plus stewardship guidance support narrowing and dose reassessment.
- C. Tempting because OPAT planning is mentioned; incorrect because discharge logistics are secondary if the inpatient regimen still needs optimization. The single clue eliminating it is culture data and CKD appearing before final transition decisions.
- D. Tempting because source control adequacy affects duration and regimen decisions, but incorrect because the pharmacist should act on the provided statement “after source control” rather than independently determining procedural adequacy. The single clue eliminating it is the role boundary and existing source-control information.
Keep going with the full BCIDP Prep Course (BCIDP)
You just studied the way members do, in the same lesson interface. Full access unlocks every lesson, the question bank and flashcards for a full year.
One payment · 1 year of access · No auto-renewal