1.1.1 - Adult ICU Pharmacist Scope
Adult ICU Pharmacist Scope
What you’ll learn
- Domain: Foundations of ICU practice → Scope of pharmacist-centered critical care decision making → distinguish medication-management tasks from non-pharmacist procedural tasks
- Domain: Foundations of ICU practice → Medication assessment workflow → identify what ICU data the pharmacist must interpret before recommending therapy
- Domain: Foundations of ICU practice → Safety and stewardship → recognize when to initiate, adjust, hold, clarify, de-escalate, or urgently escalate therapy
- Domain: Foundations of ICU practice → Interdisciplinary communication → frame the most appropriate pharmacist recommendation using board-style language
- Domain: Foundations of ICU practice → Monitoring and reassessment → select efficacy and safety parameters relevant to ICU pharmacotherapy
- Inferred BCCP study grouping: Foundations of ICU Practice → pharmacist role boundaries in adult critical care medication management
- Inferred BCCP study grouping: Foundations of ICU Practice → medication-related problem identification and prioritization
- Inferred BCCP study grouping: Medication safety/stewardship → interdisciplinary accountability, documentation, escalation, and reassessment
- Official wording and weighting may vary by exam cycle; confirm against current BPS materials
Why it matters
- BCCP questions often hinge on role framing: the best answer is not the physician’s procedure, but the pharmacist’s medication recommendation, clarification, or escalation.
- In ICU cases, the same drug can be right, wrong, or incomplete depending on hemodynamics, organ dysfunction, drug exposure, and monitoring burden.
- Scope errors create exam traps: choosing a diagnosis-only answer, ignoring safety surveillance, or missing the need to urgently communicate a high-risk medication concern.
- A clear pharmacist workflow improves speed: identify the medication task, extract the ICU data that matter, apply the governing rule, then verify efficacy and toxicity.
Key Terms & Must-Know Facts
1.1.1.1 Key terms
- Medication-related problem: any issue involving indication, drug choice, dose, route, timing, duration, interaction, toxicity, monitoring, or de-escalation
- Pharmacist-centered recommendation: a medication action framed within collaborative ICU practice
- Urgent escalation: immediate communication of a safety-critical medication issue to the ICU team
- Clarify order: verify intent when dose, route, indication, or patient-specific fit is uncertain
- Hold parameter: a threshold that should pause or interrupt medication administration pending reassessment
- Stewardship: selecting the narrowest, safest, and shortest appropriate therapy with reassessment
- PK/PD: pharmacokinetic and pharmacodynamic reasoning used to individualize ICU drug therapy
- Organ dysfunction fit: whether renal, hepatic, cardiac, or neurologic status changes drug choice or dose
- High-alert medication: drug with elevated risk of serious harm if used incorrectly
- Monitoring plan: defined efficacy and safety parameters with timing
- Therapeutic reassessment: repeat review of response, toxicity, and need for continuation
- Board-style stem task: the specific action requested, such as best initial therapy, most appropriate recommendation, or most important to monitor
1.1.1.2 Must-know facts
- The BCCP perspective is adult critical care medication management, not performance of bedside procedures.
- The pharmacist is expected to recommend, dose-adjust, monitor, prevent harm, and escalate concerns.
- Many questions test whether you can identify the single missing patient variable that changes the correct medication plan.
- On exam day, the first step is often to identify what medication decision is being asked, not to chase every abnormality in the stem.
- High-risk ICU answers commonly involve vasopressors, antimicrobials, sedatives, anticoagulants, insulin, electrolytes, and renal dose adjustments.
- A tempting answer may be correct in a similar patient but wrong here because of renal failure, hepatic dysfunction, shock, drug interaction, or contraindication.
- If a stem requires action outside pharmacist scope, the correct frame is usually recommend, clarify, verify, or urgently escalate.
- Monitoring is part of the answer, not an afterthought.
Exam takeaway: Use this map to separate pharmacist medication decisions from tempting but out-of-scope procedural actions.
flowchart TD
A[ICU patient scenario] --> B{What is the task?}
B --> C[Choose or adjust medication]
B --> D[Identify safety risk]
B --> E[Design monitoring plan]
B --> F[Recommend escalation]
C --> G[Review hemodynamics organ function interactions]
D --> G
E --> G
F --> H[Communicate urgently to ICU team]
G --> I[Pharmacist-centered recommendation]
H --> I
B --> J[Procedure or diagnosis-only task]
J --> K[Reject as primary answer if no medication action]
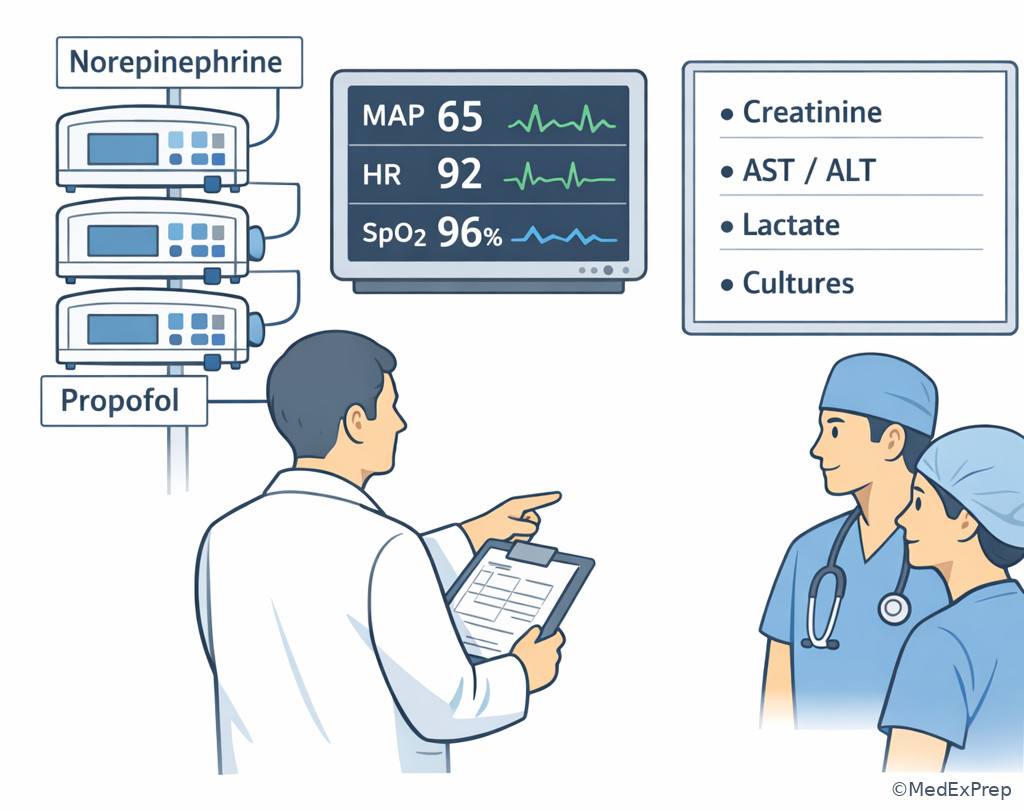
See Fig 1 for the high-yield separation between pharmacist medication management and tempting out-of-scope answer choices.
Exam takeaway: Visualize the pharmacist standing at the intersection of vitals, labs, infusions, and organ function rather than at the procedural bedside.
Core content
1.1.1.3 Foundational scope: what the ICU pharmacist is expected to do
A Explanation
The decision conflict here is simple but heavily tested: choose the answer that centers medication management versus reject the answer that centers procedure, diagnosis-only reasoning, or non-pharmacist bedside execution. In BCCP-style cases, the pharmacist is not tested on performing intubation or inserting lines. The pharmacist is tested on selecting drug therapy, identifying interactions, adjusting for organ dysfunction, prioritizing monitoring, and communicating urgent recommendations. The single resolving rule is: if the stem asks what the pharmacist should do, look for the option that changes medication therapy safely and collaboratively.
WHY THIS IS TESTED: exam writers place correct pharmacotherapy decisions next to plausible intensivist or nursing actions to see whether you stay inside pharmacist scope while still protecting the patient.
Exam takeaway: Start with the medication task, then move to patient-specific fit, then monitoring and communication.
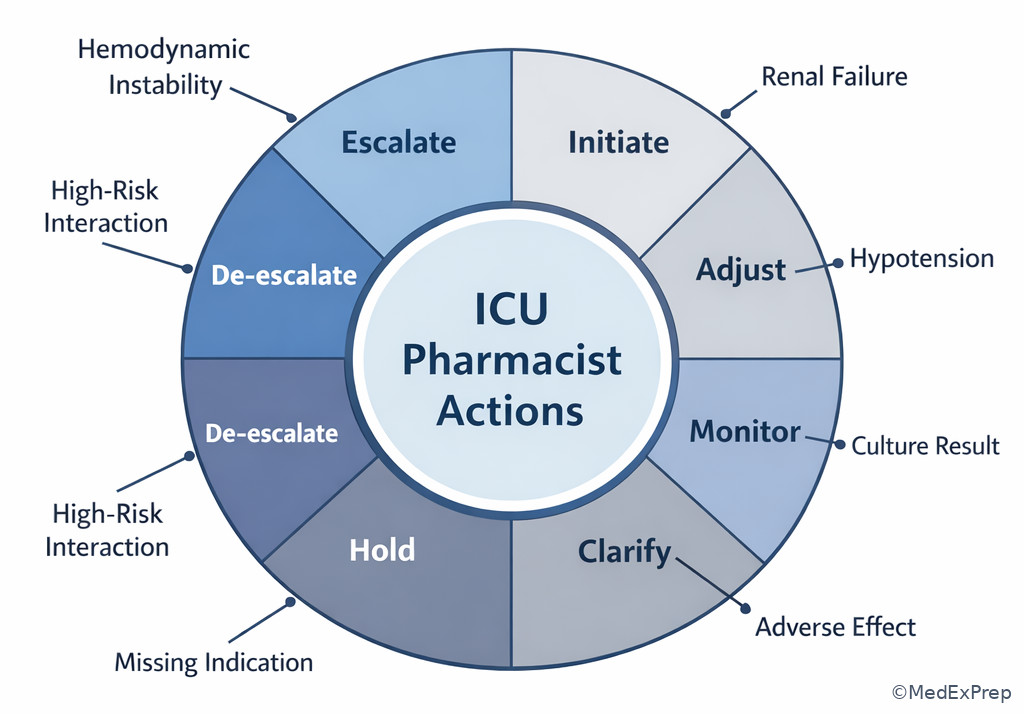
See Fig 2 for the basic action ladder you should apply before reading any answer choices.
B Worked example
A 66-year-old man in septic shock is receiving norepinephrine 0.18 mcg/kg/min, piperacillin/tazobactam 4.5 g IV every 6 hours, and vancomycin. He has atrial fibrillation, stage 3 chronic kidney disease, and type 2 diabetes. Serum creatinine increased from 1.4 to 2.1 mg/dL over 24 hours; lactate is improving; potassium is 3.4 mEq/L. The intensivist asks for pharmacy input because propofol is being considered for new agitation after intubation. One answer choice says to “perform bedside airway reassessment and set the ventilator mode.” Another says to “review hemodynamics and recommend an analgosedation strategy with dose selection and monitoring.”
Reasoning chain: Identify task → this is a pharmacist recommendation about ICU sedation. Extract key facts → shock on vasopressor, acute kidney injury, multiple infusions, intubated, agitation. Apply rule → choose medication-management action within scope; reject ventilator setup because that is not the pharmacist’s primary role. Eliminate distractors → potassium of 3.4 is relevant but not the main task; improving lactate means resuscitation trend matters but does not replace the sedation decision. Verify → the best pharmacist action is to recommend a sedative plan that accounts for hemodynamic tolerance and required monitoring.
C Exam trap
D Checkpoint
Question: A 58-year-old woman in the medical ICU is receiving dexmedetomidine 0.7 mcg/kg/hr, cefepime 2 g IV every 8 hours, and unfractionated heparin 5,000 units subcutaneously every 8 hours. She has cirrhosis and acute kidney injury. The team asks pharmacy for the most appropriate next step after new bradycardia and increasing somnolence. Which option best fits the pharmacist’s role?
- A. Independently diagnose the neurologic cause of somnolence before reviewing medications
- B. Review current sedative exposure and organ function, then recommend dexmedetomidine reassessment with monitoring and escalation if instability persists
- C. Perform a bedside neurologic procedure to determine sedation depth
- D. Set the mechanical ventilator mode to compensate for oversedation
Answer: B
- A: Tempting because it sounds thorough; wrong because the pharmacist should first address the medication contribution and communicate concerns rather than independently diagnosing outside the medication task.
- B: Tempting because it directly addresses the likely drug cause; right because it matches pharmacist scope and integrates organ function with medication monitoring.
- C: Tempting because sedation depth matters; wrong because the answer shifts into bedside procedural execution rather than pharmacist recommendation.
- D: Tempting because respiratory support may need adjustment; wrong because ventilator mode selection is not the pharmacist-centered medication action the stem is asking for.
1.1.1.4 Foundational task recognition: what data matter before you recommend anything
A Explanation
The second foundational conflict is choosing between collecting all possible ICU data and extracting only the medication-relevant data that determine therapy. Strong candidates do not get lost in the stem. They identify the task, then prioritize hemodynamics, organ function, current drug exposure, indication, timing, cultures if infection is involved, and the most immediate safety variables. The single resolving rule is: the best recommendation depends on the smallest set of data that changes drug choice, dose, route, or monitoring.
WHY THIS IS TESTED: ICU questions are noisy by design. The exam rewards pharmacists who can separate signal from distraction and tie each abnormality to a medication consequence.
Exam takeaway: Pull only the variables that change the drug plan, not every ICU number in the chart.
Exam takeaway: Hemodynamics, organ function, exposure history, and safety variables outrank incidental abnormalities in most ICU medication questions.
flowchart LR
A[Medication task] --> B[Hemodynamics]
A --> C[Renal function]
A --> D[Hepatic function]
A --> E[Current drugs and interactions]
A --> F[Indication and timing]
A --> G[Relevant cultures or drug levels]
B --> H[Recommendation]
C --> H
D --> H
E --> H
F --> H
G --> H
A --> I[Incidental data]
I --> J[Do not let noise drive the answer]
See Fig 3 when stems overload you with data. Start with the variables that actually change therapy.
B Worked example
A 72-year-old woman in the surgical ICU is receiving meropenem 1 g IV every 8 hours, enoxaparin 40 mg subcutaneously daily, and fentanyl infusion 75 mcg/hr. She has obesity, chronic heart failure, and nonalcoholic fatty liver disease. Blood pressure is stable, urine output fell overnight, serum creatinine rose from 0.9 to 2.3 mg/dL, AST is mildly elevated, and magnesium is 1.6 mg/dL. A question asks for the most appropriate pharmacist recommendation regarding antimicrobial dosing. The distracting clues are obesity and mild transaminitis, but the decisive variable is acute kidney injury because meropenem clearance is primarily renal.
Reasoning chain: Identify task → antimicrobial dose adjustment. Extract key facts → meropenem exposure, acute renal decline, hemodynamic stability, mild hepatic abnormality. Apply rule → choose the data that change antimicrobial dosing now: renal function and severity of infection. Eliminate distractors → magnesium matters for overall ICU safety but not the primary dose adjustment decision; mild transaminitis is less influential for meropenem than creatinine rise. Verify → recommend reassessment of renal-adjusted dosing and response monitoring.
C Exam trap
D Checkpoint
Question: A 64-year-old man with septic shock is receiving norepinephrine 0.12 mcg/kg/min, cefepime 2 g IV every 8 hours, and stress-dose insulin infusion. He has chronic kidney disease, COPD, and recent atrial fibrillation with rapid ventricular response now controlled. Which data point is most important for the pharmacist to prioritize before recommending cefepime dose adjustment?
- A. Current serum creatinine trend and urine output
- B. Remote COPD history
- C. Corrected calcium level
- D. Prior home antihypertensive regimen
Answer: A
- A: Tempting because cefepime is commonly renally adjusted; right because renal function most directly affects current dosing and neurotoxicity risk.
- B: Tempting because COPD affects ICU care broadly; wrong because it does not drive cefepime dose adjustment in this stem.
- C: Tempting because electrolyte abnormalities can matter in critical illness; wrong because it is not the main determinant of cefepime exposure here.
- D: Tempting because medication reconciliation matters; wrong because home antihypertensives do not determine cefepime dosing.
- The most common reason a tempting ICU answer is wrong in this lesson is that it falls outside pharmacist scope.
- True or False: The most abnormal lab is always the most important data point for the medication question. False.
- Name the 3 highest-yield data buckets before a pharmacist recommendation: hemodynamics, organ function, current drug exposure.
1.1.1.5 Application: choosing the right pharmacist action verb
A Explanation
Once you know the scope and have filtered the data, the next conflict is choosing which pharmacist action verb fits the stem: initiate, adjust, hold, discontinue, de-escalate, clarify, or urgently escalate. Many answer choices contain clinically reasonable drugs, but only one action fits the timing and risk. The single resolving rule is to match the urgency of the medication problem to the action verb. If the patient is unstable because of a current therapy, urgent escalation or immediate clarification is stronger than routine monitoring. If the therapy is effective but broader than necessary, de-escalation is stronger than discontinuation. If the indication exists but patient-specific fit changed, dose adjustment is stronger than starting over.
WHY THIS IS TESTED: BCCP questions often hinge less on the drug name and more on the correct medication-management move at that exact moment.
Exam takeaway: Match the urgency and reversibility of the medication problem to the strongest appropriate pharmacist action.
Exam takeaway: Pair each pharmacist action with the clinical trigger that makes it the safest next recommendation.
B Worked example
A 59-year-old man in the neuro ICU is receiving levetiracetam 1,500 mg IV every 12 hours, enoxaparin 40 mg daily, and nicardipine infusion. He has obesity, hypertension, and newly developed acute kidney injury after contrast exposure. He is seizure-free. Platelets are normal, magnesium is 1.7 mg/dL, and his spouse reports he takes herbal supplements at home. The stem asks for the most appropriate pharmacist recommendation regarding levetiracetam. The key issue is not initiation, not discontinuation, and not de-escalation for lack of indication. It is dose adjustment because the indication remains but renal clearance changed.
Reasoning chain: Identify task → current anticonvulsant management. Extract key facts → active order, renal injury, ongoing indication, no evidence of toxicity yet. Apply rule → therapy needed but patient fit changed, so adjust rather than stop. Eliminate distractors → stopping would be appropriate only if the indication resolved or toxicity outweighed benefit; escalating would fit an unstable adverse event, which is not present. Verify → recommend renal reassessment and dose fit monitoring.
C Exam trap
D Checkpoint
Question: A 70-year-old woman in septic shock is receiving vancomycin, cefepime, and amiodarone infusion. She has chronic kidney disease, obesity, and recent culture data showing methicillin-susceptible Staphylococcus aureus. She is hemodynamically improved. Which pharmacist action verb best fits vancomycin management now?
- A. Escalate
- B. De-escalate
- C. Clarify because vancomycin has no Gram-positive activity
- D. Hold permanently because any kidney disease contraindicates vancomycin
Answer: B
- A: Tempting because the patient was recently unstable; wrong because improvement and culture data support narrowing rather than broadening.
- B: Tempting because MSSA cultures point toward a narrower beta-lactam; right because stewardship and pathogen-specific therapy now drive the action.
- C: Tempting only if the student confuses spectrum; wrong because vancomycin does cover Gram-positive organisms, so this rationale is false.
- D: Tempting because kidney injury raises toxicity concern; wrong because renal dysfunction requires monitoring and adjustment, not universal permanent discontinuation.
1.1.1.6 Application: monitoring, reassessment, and safety surveillance are part of the answer
A Explanation
A frequent exam conflict is choosing between the answer that names the correct drug and the answer that names the correct drug plus monitoring plan. In critical care, therapy selection is incomplete without a follow-up strategy. The single resolving rule is: if two answers seem therapeutically plausible, choose the one that includes the parameter most likely to detect efficacy, toxicity, or the need for dose change. Monitoring should be mechanistically linked: vasopressors need hemodynamics and perfusion reassessment; renally cleared drugs need kidney function and exposure review; sedatives need sedation depth and cardiorespiratory safety checks; anticoagulants need bleeding surveillance and context-specific laboratory review.
WHY THIS IS TESTED: ICU pharmacotherapy is dynamic. The board expects the pharmacist to design surveillance, not just suggest a one-time medication order.
Exam takeaway: The best pharmacist recommendation connects each ICU drug decision to a concrete monitoring parameter and reassessment trigger.
flowchart TD
A[Medication chosen] --> B{What can change quickly?}
B --> C[Hemodynamics]
B --> D[Organ function]
B --> E[Drug level or exposure]
B --> F[Adverse effect signal]
C --> G[Adjust or escalate]
D --> G
E --> G
F --> G
G --> H[Document and reassess]
See Fig 4 to remember that monitoring is not separate from therapy selection; it is part of the therapeutic recommendation.
Exam takeaway: Every ICU medication decision should end with a specific follow-up parameter and timing plan.
B Worked example
A 61-year-old woman in cardiogenic shock is receiving norepinephrine 0.08 mcg/kg/min, dobutamine 5 mcg/kg/min, and furosemide infusion. She has chronic kidney disease, atrial fibrillation, and diabetes. Potassium is 3.2 mEq/L, magnesium is 1.5 mg/dL, and urine output improved slightly. A question asks for the most appropriate pharmacist recommendation regarding ongoing dobutamine therapy. The right answer must include what to monitor: heart rate/rhythm, perfusion, blood pressure, and electrolytes that may amplify arrhythmic risk.
Reasoning chain: Identify task → optimize active inotrope therapy. Extract key facts → inotrope exposure, arrhythmia history, electrolyte depletion, shock state. Apply rule → choose recommendation plus monitoring. Eliminate distractors → urine output alone is incomplete; renal function matters but does not replace rhythm surveillance; magnesium and potassium are not just incidental because they alter safety risk. Verify → recommend continued hemodynamic and rhythm monitoring with electrolyte correction considerations.
C Exam trap
D Checkpoint
Question: A 63-year-old man is receiving unfractionated heparin infusion for acute VTE in the ICU. He also has sepsis, recent surgery, and acute kidney injury. Which pharmacist recommendation is most complete?
- A. Continue heparin because it is guideline-supported, with no additional plan needed
- B. Continue heparin and monitor the institution’s anticoagulation parameter plus bleeding signs and platelet trend
- C. Switch immediately to low-molecular-weight heparin without reviewing renal function
- D. Stop anticoagulation because recent surgery makes all anticoagulation inappropriate
Answer: B
- A: Tempting because heparin is often reasonable in ICU patients; wrong because the answer omits essential monitoring.
- B: Tempting because it sounds operationally complete; right because anticoagulation management requires efficacy and safety surveillance.
- C: Tempting because LMWH is commonly used for VTE; wrong because renal dysfunction and ICU context require individualized assessment first.
- D: Tempting because postoperative bleeding risk is real; wrong because surgery is not an automatic universal contraindication, and the stem does not justify blanket discontinuation.
- True or False: A correct ICU medication choice without a monitoring plan may still be an incomplete answer. True.
- The best paired monitoring buckets are efficacy and toxicity.
- Name one high-risk ICU class where monitoring is inseparable from therapy selection: vasopressors, anticoagulants, sedatives, antimicrobials, insulin.
1.1.1.7 Integration: escalation, communication, and stewardship within pharmacist scope
A Explanation
The highest-yield integration question asks what the pharmacist should do when a medication issue is both time-sensitive and interdisciplinary. The conflict is choosing between passive observation and active escalation. The single resolving rule is: when a medication problem creates immediate risk, the pharmacist should urgently communicate the recommendation and document the rationale, while still staying inside collaborative scope. This includes unsafe infusions, major interaction risks, omitted life-saving therapies, incorrect renal dosing in unstable patients, and continued broad-spectrum therapy without reassessment. Stewardship is also part of scope: once instability resolves or data narrow the diagnosis, the pharmacist should recommend de-escalation, discontinuation, or duration optimization.
WHY THIS IS TESTED: the board expects you to protect patients by recognizing when the medication issue is urgent enough that routine note-only communication is inadequate.
Exam takeaway: Immediate instability or major medication harm triggers urgent pharmacist communication, while stable optimization issues can follow routine reassessment.
flowchart TD
A[Medication issue identified] --> B{Immediate harm or instability?}
B -->|Yes| C[Urgently communicate recommendation]
C --> D[Hold adjust or reverse if appropriate]
D --> E[Document and monitor closely]
B -->|No| F[Routine reassessment]
F --> G[Optimize dose duration or de-escalation]
G --> E
See Fig 5 for the escalation threshold that separates urgent communication from routine optimization.
Exam takeaway: Unsafe medication exposure should trigger rapid recommendation, communication, documentation, and reassessment.
B Worked example
A 68-year-old man in a mixed ICU is receiving linezolid 600 mg IV every 12 hours, fentanyl infusion 150 mcg/hr, and vasopressin 0.03 units/min. He has shock, chronic kidney disease, and depression treated with home sertraline that was accidentally continued. Temperature is 39.1°C, heart rate 132/min, and he is increasingly rigid. Creatinine is elevated, and platelet count is mildly decreased. A tempting but wrong clue is the thrombocytopenia, which may push the learner toward linezolid toxicity alone. The more urgent medication issue is the possible serotonergic interaction requiring immediate pharmacist communication.
Reasoning chain: Identify task → urgent medication safety recommendation. Extract key facts → linezolid plus sertraline, autonomic instability, hyperthermia, rigidity. Apply rule → immediate-harm interaction means urgent escalation, not passive monitoring. Eliminate distractors → mild thrombocytopenia is real but not the immediate threat; renal dysfunction matters but does not change the interaction urgency. Verify → recommend urgent review of serotonergic exposure and communication to the ICU team now.
C Exam trap
D Checkpoint
Question: A 56-year-old woman on piperacillin/tazobactam, vancomycin, and norepinephrine develops rapidly worsening acute kidney injury. Cultures now show a susceptible Escherichia coli bloodstream infection. Which pharmacist recommendation best reflects stewardship and scope?
- A. Continue both antibiotics indefinitely because broad coverage is safer in all ICU patients
- B. Recommend narrowing therapy based on cultures and reassessing renal-adjusted dosing
- C. Wait for complete resolution of shock before considering any antimicrobial changes
- D. Independently discontinue vasopressor support to reduce kidney injury
Answer: B
- A: Tempting because severe infection initially warrants broad therapy; wrong because culture-directed de-escalation is part of pharmacist stewardship.
- B: Tempting because it addresses both pathogen-specific fit and renal safety; right because it stays within pharmacist scope and integrates reassessment.
- C: Tempting because instability can delay some changes; wrong because culture data already support targeted optimization and dose fit now.
- D: Tempting because hemodynamics affect kidney function; wrong because stopping vasopressors independently is outside pharmacist role and misses the antimicrobial stewardship task.
Exam takeaway: The pharmacist’s highest-yield ICU action is often urgent communication of a medication change tied to a specific safety threat.
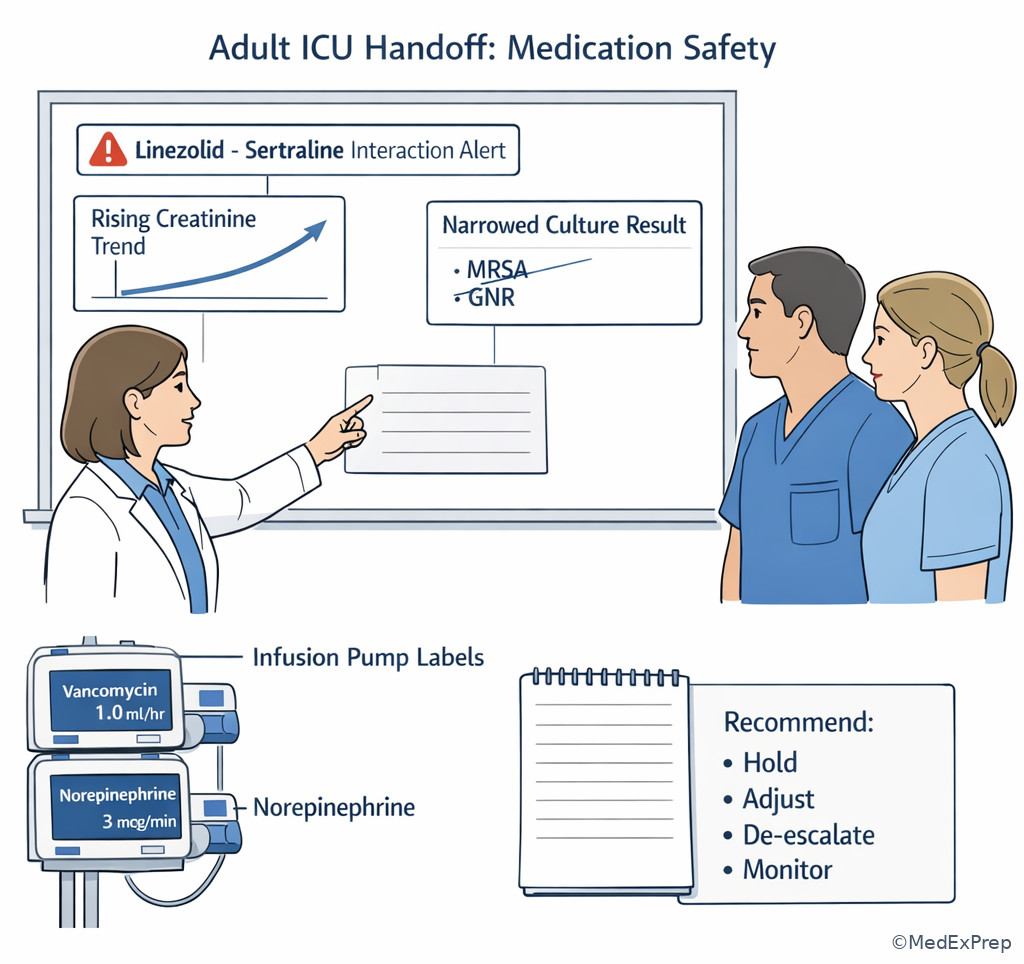
See Fig 6 for the pharmacist-centered escalation frame: identify the threat, recommend the change, communicate urgently, and verify follow-through.
Exam Traps & Differentiators
- Most common wrong answer: the procedural or diagnosis-only option. Why: it feels more urgent and more “ICU.” Discriminator: if the stem asks for the pharmacist recommendation, choose the medication-management action.
- Second common wrong answer: the correct drug without a monitoring plan. Why: students anchor on treatment names. Discriminator: the complete ICU answer includes efficacy and toxicity follow-up.
- Third common wrong answer: chasing the most abnormal lab instead of the most medication-relevant one. Why: the stem is designed to distract. Discriminator: prioritize the variable that changes drug choice, dosing, or contraindication.
- Fourth common wrong answer: discontinuing a needed drug when adjustment is enough. Why: new organ dysfunction makes the drug look dangerous. Discriminator: if the indication persists and the drug remains usable with modification, adjust rather than stop.
1.1.1.8 Looks similar but isn’t
| Tempting pair | Looks similar because | Single clue that separates them | Pharmacist-centered answer |
|---|---|---|---|
| Urgent escalation vs routine monitoring | Both involve ongoing surveillance | Current instability or preventable harm | Escalate now when the medication issue is actively dangerous |
| Discontinue vs dose-adjust | Both change the current regimen | Whether the indication still exists and safe use remains possible | Adjust if still indicated and modifiable |
| De-escalate vs continue broad therapy | Both can be initially reasonable in severe infection | Culture data or clinical reassessment supporting narrower coverage | Recommend targeted therapy plus reassessment |
| Correct drug vs correct drug plus monitoring | Both may appear therapeutically sound | One option names a follow-up parameter and action threshold | Choose the more complete ICU plan |
| Medication task vs diagnosis-only task | Both sound clinically important | The stem asks for pharmacist action on therapy | Recommend, adjust, hold, clarify, or monitor |
If the stem says “most appropriate pharmacist recommendation”, think medication action verb plus monitoring.
If the stem says “requires immediate clarification”, think unsafe order, major interaction, dose mismatch, or contraindication.
If the stem says “best next step” in an unstable patient, think urgent escalation rather than passive observation.
If the stem says “hemodynamically improved with culture data available,” think stewardship and de-escalation opportunities.
If the stem says “new organ dysfunction,” think patient-specific fit before abandoning a needed therapy.
If the stem says “multiple abnormal labs,” think which one mechanistically changes the drug decision.
Tables
| Pharmacist scope task | What you should assess | Typical output on exam | Immediate safety flag |
|---|---|---|---|
| Drug selection | Indication, allergies, hemodynamics, cultures, interactions | Recommend best initial therapy | Contraindication or mismatch to syndrome |
| Dose individualization | Renal function, hepatic function, weight, organ support, drug levels | Recommend adjusted dose or interval | Rapid organ function change with unchanged order |
| Safety surveillance | Adverse effects, duplicate therapy, interactions, infusion rates | Clarify, hold, or escalate | Current harm or imminent toxicity |
| Monitoring plan | Efficacy marker, toxicity marker, timing, thresholds | State what to monitor and when | No follow-up plan for high-alert drug |
| Stewardship | Culture results, duration, response, spectrum fit | De-escalate or discontinue when appropriate | Broad therapy continued without reassessment |
| Interdisciplinary communication | Urgency, recommended action, rationale, documentation | Communicate and verify implementation | Major interaction or unsafe order requiring immediate attention |
| Action verb | When to choose it | Close-call distractor | Why distractor is wrong |
|---|---|---|---|
| Initiate | Indicated therapy is missing | Monitor only | Observation does not fix an untreated medication need |
| Adjust | Drug is needed but dose or interval no longer fits | Discontinue | Stopping is too strong if the indication remains |
| Hold | Current administration is unsafe pending reassessment | Continue with watchful waiting | Ongoing exposure may worsen harm |
| Clarify | Order intent, indication, or fit is uncertain | Assume the order is correct | High-alert medications require verification when details conflict |
| De-escalate | Narrower or lower-intensity therapy is now supported | Continue broad coverage | Misses stewardship and avoidable toxicity |
| Escalate urgently | Immediate medication-related harm or instability | Routine documentation only | Urgent hazards require real-time communication |
| Question pattern | Primary differential | Best discriminator | Likely answer form |
|---|---|---|---|
| Most appropriate pharmacist recommendation | Medication action vs procedural task | Scope framing | Recommend/adjust/clarify/monitor |
| Requires immediate clarification | Minor imperfection vs major safety mismatch | Imminent harm threshold | Hold or urgently communicate |
| Most important to monitor | Interesting abnormality vs drug-linked marker | Mechanistic connection to therapy | Efficacy or toxicity parameter |
| Best next step after new renal dysfunction | Discontinue vs adjust | Persistent indication | Dose reassessment |
| Cultures now finalized | Continue empiric breadth vs narrow regimen | Stewardship opportunity | De-escalate |
| Unstable patient on high-alert drug | Observe vs escalate | Current harm from medication | Urgent communication and change |
Exam takeaway: High-alert drugs demand a linked safety parameter and a clear escalation threshold in the pharmacist plan.
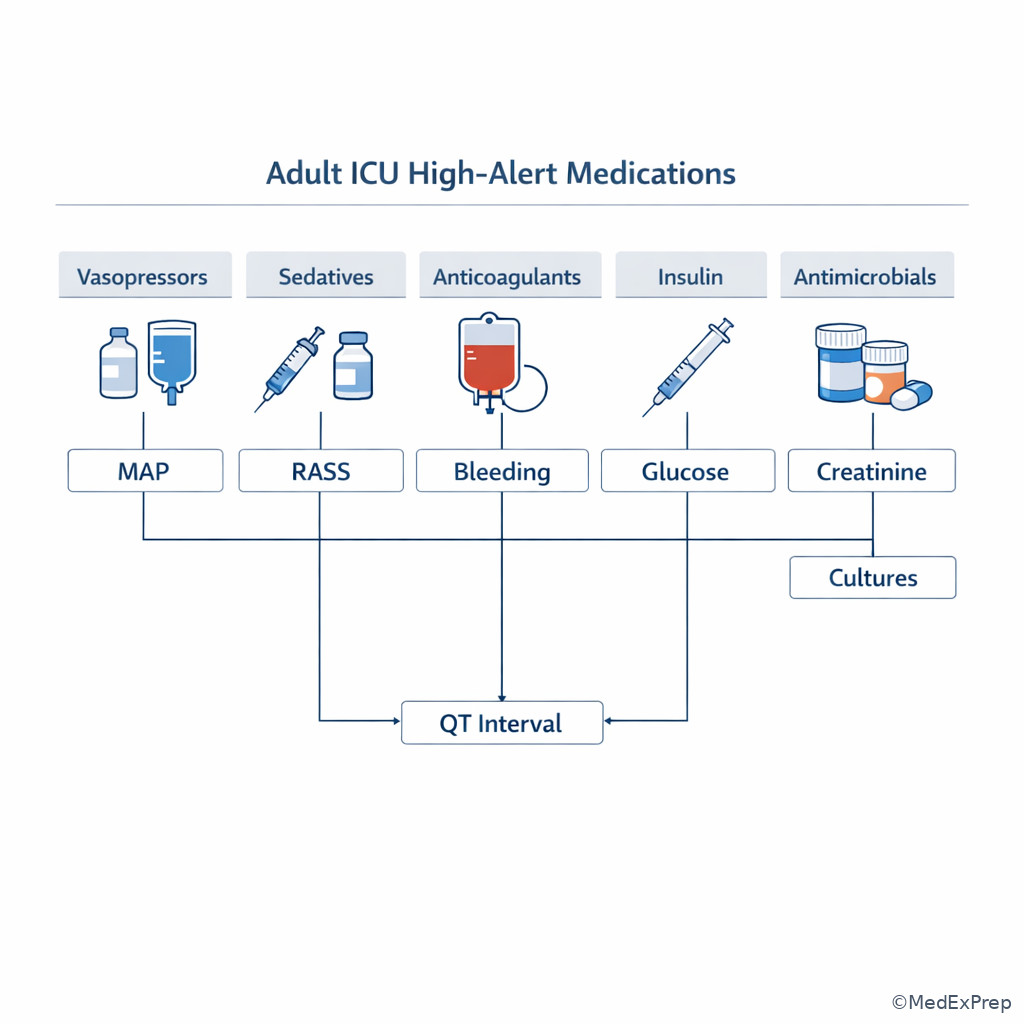
Exam takeaway: New kidney injury changes the pharmacist’s recommendation only when the drug or toxicity risk is actually renal-linked.
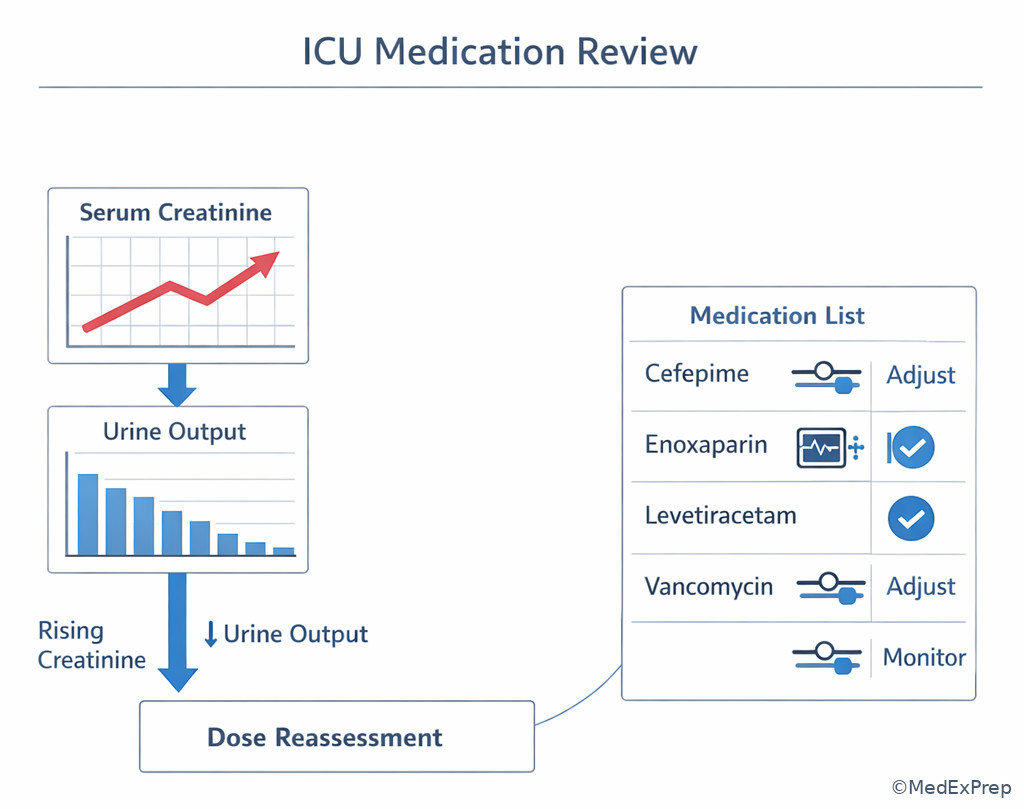
Exam takeaway: Once microbiology narrows the target, the pharmacist should think stewardship, duration, and toxicity reduction.
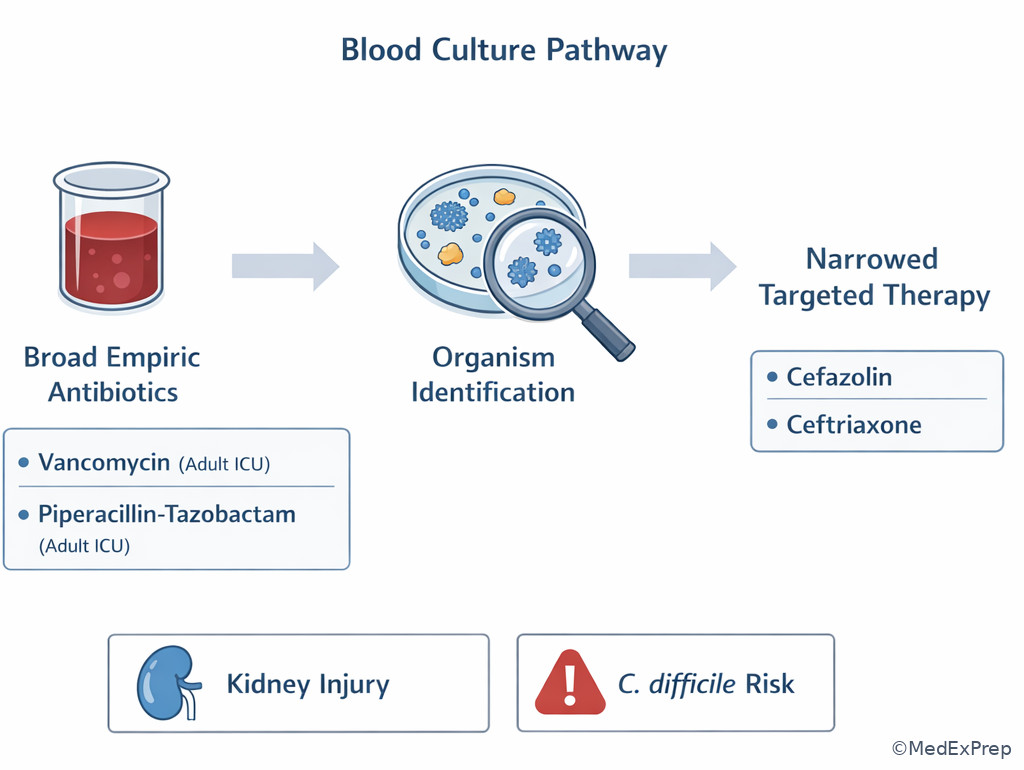
Algorithm / Approach
Forward reference: the next lesson, Medication Problem-Solving Framework, takes this algorithm and formalizes it into a repeatable case-solving sequence.
Rapid Review
- Pharmacist scope → choose medication management, not bedside procedure
- Best next step → identify the task before interpreting the entire stem
- Noisy vignette → prioritize the variable that changes drug fit
- New renal dysfunction → think dose adjustment before discontinuation if indication persists
- Two good treatment options → pick the one with the stronger monitoring plan
- Immediate medication harm → urgent communication beats passive observation
- Culture finalization → stewardship and de-escalation opportunity
- High-alert drug → define a hold or escalation threshold
- Action verb trap → discontinue is too strong when modify is sufficient
- Scope distractor → reject diagnosis-only or procedural answers lacking medication action
- Monitoring pearl → one efficacy marker plus one toxicity marker
- ICU pharmacist role → recommend, clarify, verify, document, escalate
Self-check quiz
1. A 67-year-old man in septic shock is receiving norepinephrine 0.1 mcg/kg/min, cefepime 2 g IV every 8 hours, and fentanyl infusion 50 mcg/hr. He has chronic kidney disease and diabetes. The team asks for the most appropriate pharmacist recommendation. Which option best fits pharmacist scope?
- A. Recommend medication review with renal dose assessment and monitoring
- B. Perform bedside central line insertion
- C. Set the ventilator mode
- D. Independently diagnose the source of shock before addressing medications
2. A 60-year-old woman is receiving meropenem 1 g IV every 8 hours, dexmedetomidine 0.5 mcg/kg/hr, and heparin prophylaxis. She has obesity, hypertension, and new acute kidney injury. Which data point is most important before recommending meropenem dose adjustment?
- A. Serum creatinine trend and urine output
- B. Remote migraine history
- C. Morning cortisol level
- D. Home vitamin supplement list
3. A 74-year-old man with ventilator-associated pneumonia is receiving vancomycin, piperacillin/tazobactam 4.5 g IV every 6 hours, and norepinephrine 0.04 mcg/kg/min. He has stage 4 chronic kidney disease and atrial fibrillation. Cultures now show susceptible MSSA, creatinine is rising, and lactate is improving. Which is the most appropriate pharmacist recommendation?
- A. Continue vancomycin unchanged because Gram-positive coverage remains necessary
- B. De-escalate from vancomycin to a targeted anti-MSSA beta-lactam and reassess renal-adjusted dosing
- C. Stop all antibiotics because lactate is improving
- D. Increase vancomycin dose to offset critical illness volume of distribution
4. A 62-year-old woman in the neuro ICU receives levetiracetam 1,500 mg IV every 12 hours, nicardipine infusion, and enoxaparin 40 mg daily. She has obesity and contrast-associated acute kidney injury; she remains seizure-free. Which action verb best fits levetiracetam management?
- A. Discontinue permanently
- B. Adjust dose
- C. Escalate urgently because any renal dysfunction makes the drug prohibited
- D. De-escalate because seizure freedom means no further therapy is ever needed
5. A 65-year-old man receives unfractionated heparin infusion for acute PE, with aPTT-guided titration per local protocol. He has sepsis, recent abdominal surgery, and acute kidney injury. Which pharmacist recommendation is most complete?
- A. Continue heparin and monitor anticoagulation parameter, platelet trend, and bleeding
- B. Continue heparin without monitoring because the protocol handles it
- C. Change to enoxaparin 1 mg/kg every 12 hours without renal review
- D. Discontinue anticoagulation because surgery occurred during this admission
6. A 69-year-old man in mixed shock is receiving linezolid 600 mg IV every 12 hours, fentanyl infusion 125 mcg/hr, and home sertraline was resumed. He has chronic kidney disease and diabetes. He develops fever, tachycardia, and rigidity. Which pharmacist recommendation requires immediate escalation?
- A. Continue current therapy and recheck a CBC tomorrow
- B. Urgently communicate concern for serotonergic interaction and recommend immediate medication reassessment
- C. Wait until cultures finalize before changing medications
- D. Increase fentanyl to treat presumed agitation-related sympathetic surge
7. A 71-year-old woman in septic shock is receiving cefepime 2 g IV every 8 hours, vancomycin, amiodarone infusion, and insulin infusion. She has chronic kidney disease, obesity, and mild baseline confusion. Over 48 hours, creatinine doubles and she becomes more encephalopathic; QTc is stable and glucose is controlled. Which pharmacist recommendation is most appropriate?
- A. Focus on amiodarone because QT prolongation is always the main issue
- B. Review cefepime exposure and renal dose fit as a priority medication-related cause of worsening encephalopathy
- C. Stop insulin infusion because neurologic change means hypoglycemia until proven otherwise despite controlled glucose
- D. Make no changes because encephalopathy is expected in all septic ICU patients
8. A 57-year-old man with bacteremic sepsis is receiving piperacillin/tazobactam 4.5 g IV every 6 hours, vancomycin, norepinephrine 0.03 mcg/kg/min, and stress ulcer prophylaxis. He has chronic kidney disease and heart failure. Blood cultures finalize as susceptible E. coli, creatinine is worsening, and hemodynamics are improving. Which option is the best pharmacist-centered recommendation?
- A. Continue broad-spectrum therapy until ICU discharge because shock was present initially
- B. Recommend narrowing to a targeted agent and reassessing renal-adjusted dosing now
- C. Discontinue all antimicrobials once norepinephrine is stopped
- D. Independently change the vasopressor regimen to improve renal perfusion before addressing antibiotics
Answer key
1.1.1.9 1. Answer: A
- A: Tempting because it sounds less dramatic than procedural options; correct because it stays within pharmacist scope by linking renal dose assessment and monitoring to current medications. The single stem clue is “most appropriate pharmacist recommendation.” Confirmed by pharmacist-centered critical care practice expectations in ACCP critical care training standards and standard ICU pharmacy role texts.
- B: Tempting because septic shock often involves line-related procedures; incorrect because bedside central line insertion is outside pharmacist procedural scope. The single clue is that the task is medication management, not invasive access. Supported by BCCP scope framing and ICU pharmacy role descriptions.
- C: Tempting because ventilated ICU patients need ventilator adjustment; incorrect because setting ventilator mode is not the pharmacist-centered answer here. The single clue is that the question asks for a recommendation on medications, not device operation.
- D: Tempting because diagnosis informs treatment; incorrect because independently diagnosing shock before addressing drug therapy misses the medication task and exceeds the intended pharmacist role. The single clue is the presence of active ICU medications requiring review now.
Sources: DiPiro et al.; ACCP critical care pharmacy guidance.
1.1.1.10 2. Answer: A
- A: Tempting because meropenem is commonly renally adjusted; correct because creatinine trend and urine output directly affect meropenem exposure and dose fit. The single clue is new acute kidney injury. Supported by Lexicomp, AHFS, and FDA labeling for renal dose adjustment.
- B: Tempting because comorbid histories can matter in ICU care; incorrect because migraine history does not drive meropenem dosing in this scenario. The single clue is that the question asks specifically about dose adjustment.
- C: Tempting because endocrine issues can complicate critical illness; incorrect because cortisol does not determine meropenem clearance. The single clue is the antimicrobial PK task.
- D: Tempting because home medication review may reveal interactions; incorrect because supplement history is lower priority than renal function for this drug. The single clue is the acute change in kidney status.
Sources: Lexicomp; AHFS Drug Information; FDA meropenem labeling.
1.1.1.11 3. Answer: B
- A: Tempting because vancomycin covers MSSA and was appropriate empirically; incorrect because finalized MSSA data favor targeted beta-lactam therapy, and rising creatinine increases the cost of unnecessary vancomycin exposure. The single stem clue is “susceptible MSSA” plus renal worsening. IDSA stewardship principles and drug references support de-escalation.
- B: Tempting because it addresses both microbiology and renal safety; correct because targeted anti-MSSA beta-lactam therapy is preferred once cultures identify MSSA, with renal fit reassessed. The single clue is final culture data with clinical improvement. Supported by IDSA principles, Lexicomp, and standard infectious diseases references.
- C: Tempting because lactate improvement suggests recovery; incorrect because improving perfusion does not justify stopping active infection treatment. The single clue is ongoing documented pneumonia with positive cultures.
- D: Tempting because critical illness can increase volume of distribution; incorrect because the patient now has rising creatinine and a narrower pathogen-directed option, not a reason for vancomycin escalation. The single clue is renal injury plus MSSA susceptibility.
Sources: IDSA stewardship guidance; Lexicomp; AHFS.
1.1.1.12 4. Answer: B
- A: Tempting because renal injury makes continued therapy feel risky; incorrect because the indication persists and levetiracetam often remains usable with dose adjustment. The single clue is that the patient remains at risk and seizure-free on therapy rather than experiencing a definitive contraindication. Supported by Lexicomp and FDA labeling.
- B: Tempting because it preserves therapy while addressing new renal mismatch; correct because renal clearance changes drug fit without necessarily eliminating the indication. The single clue is contrast-associated acute kidney injury in a patient on an actively indicated renally cleared medication.
- C: Tempting because kidney dysfunction raises concern for accumulation; incorrect because renal dysfunction does not universally prohibit levetiracetam. The single clue is absence of a true contraindication or acute severe toxicity.
- D: Tempting because seizure freedom looks like treatment success; incorrect because being controlled does not mean prophylaxis or ongoing therapy is no longer needed in the ICU context. The single clue is that the question asks about dose fit, not stopping based on success alone.
Sources: Lexicomp; FDA levetiracetam labeling.
1.1.1.13 5. Answer: A
- A: Tempting because it sounds detailed; correct because UFH management in critically ill adults requires protocol-based anticoagulation monitoring plus bleeding and platelet surveillance. The single clue is active therapeutic heparin infusion in a high-risk ICU patient. Supported by CHEST/anticoagulation guidance and institutional protocol principles.
- B: Tempting because protocols standardize titration; incorrect because the pharmacist is still responsible for recognizing and following efficacy and safety parameters. The single clue is that the question asks for the most complete recommendation.
- C: Tempting because enoxaparin is commonly used for VTE treatment; incorrect because acute kidney injury makes blind conversion inappropriate and the stem emphasizes ongoing UFH management. The single clue is renal dysfunction with a currently titratable ICU anticoagulant.
- D: Tempting because recent surgery increases bleeding risk; incorrect because surgery alone does not mandate cessation of indicated therapeutic anticoagulation without more bleeding context. The single clue is acute PE requiring treatment.
Sources: CHEST antithrombotic guidance; Lexicomp; AHFS.
1.1.1.14 6. Answer: B
- A: Tempting because linezolid can cause delayed hematologic toxicity that merits CBC review; incorrect because fever, tachycardia, and rigidity with sertraline coexposure point to a more urgent serotonergic safety issue. The single clue is the symptomatic linezolid-sertraline combination. Supported by FDA labeling, Lexicomp interaction data, and critical care drug references.
- B: Tempting because it escalates a drug interaction concern quickly; correct because the combination plus current symptoms suggests immediate medication-related harm requiring urgent communication and reassessment. The single clue is active instability with a known interaction pair.
- C: Tempting because antimicrobial decisions often depend on cultures; incorrect because an acute safety interaction cannot wait for microbiology. The single clue is the current syndrome of toxicity, not pathogen uncertainty.
- D: Tempting because agitation can increase sympathetic tone; incorrect because increasing fentanyl misses the probable interaction and may worsen assessment difficulty. The single clue is rigidity and serotonergic coexposure, not undertreated pain alone.
Sources: Lexicomp interaction monographs; FDA linezolid labeling; AHFS.
1.1.1.15 7. Answer: B
- A: Tempting because amiodarone often raises QT concerns in ICU patients; incorrect because the stem specifically says QTc is stable, while renal failure plus encephalopathy makes cefepime exposure the more discriminating medication issue. The single clue is stable QTc with doubling creatinine.
- B: Tempting because cefepime neurotoxicity is a known renal exposure problem; correct because worsening encephalopathy in the setting of rising creatinine should trigger review of cefepime dose fit and neurotoxicity risk. The single clue is renal deterioration temporally linked to neurologic decline. Supported by Lexicomp, FDA cefepime labeling, and ICU antimicrobial references.
- C: Tempting because hypoglycemia can cause neurologic change; incorrect because the stem says glucose is controlled, removing that as the best medication explanation. The single clue is absence of glucose evidence for insulin-related neurotoxicity.
- D: Tempting because septic encephalopathy is common; incorrect because the board expects pharmacists to identify medication-related causes when a known drug-risk pattern is present. The single clue is cefepime plus acute kidney injury.
Sources: Lexicomp; FDA cefepime labeling; AHFS.
1.1.1.16 8. Answer: B
- A: Tempting because shock initially justifies broad empiric therapy; incorrect because finalized susceptible E. coli cultures and improving hemodynamics create a stewardship opportunity, especially with worsening kidney function. The single clue is improving shock plus organism identification. Supported by IDSA stewardship principles and antimicrobial references.
- B: Tempting because it combines spectrum narrowing with renal safety; correct because the pharmacist should recommend targeted therapy and reassess dose fit based on worsening creatinine. The single clue is culture finalization paired with renal deterioration.
- C: Tempting because vasopressor discontinuation may suggest recovery; incorrect because stopping antibiotics based on hemodynamic recovery alone ignores the documented bloodstream infection. The single clue is active bacteremia requiring treatment continuation, not cessation.
- D: Tempting because renal perfusion matters in shock; incorrect because independently changing vasopressors is outside the stem’s pharmacist-centered antimicrobial task. The single clue is the question asking for the best medication-centered recommendation regarding current therapy optimization.
Sources: IDSA stewardship guidance; Lexicomp; AHFS Drug Information.
Keep going with the full BCCP Prep Course (BCCP)
You just studied the way members do, in the same lesson interface. Full access unlocks every lesson, the question bank and flashcards for a full year.
One payment · 1 year of access · No auto-renewal