1.1.1 - Shock And Organ Perfusion
Why it matters
- Shock questions are rarely testing a label alone; they test whether you can identify inadequate tissue perfusion early enough to change drug therapy.
- For the critical care pharmacist, the exam often turns on what to start first, what not to delay, and what to monitor within minutes to hours.
- Poor organ perfusion immediately changes drug handling, so the same dose can become ineffective in one patient and toxic in another.
- Early confusion between distributive, cardiogenic, hypovolemic, and obstructive patterns leads to classic board traps in fluids, vasopressors, inotropes, and medication safety.
Key Terms & Must-Know Facts
1.1.1.1 Key terms
- Shock — acute circulatory failure causing inadequate oxygen delivery relative to tissue demand.
- Organ perfusion — effective blood flow to tissues sufficient to support cellular function.
- MAP — mean arterial pressure; common hemodynamic target in vasopressor therapy.
- Lactate — marker of global stress/hypoperfusion, but not a standalone diagnosis.
- Fluid responsiveness — likelihood that stroke volume or cardiac output increases after fluid administration.
- Vasoplegia — low systemic vascular tone leading to reduced arterial pressure despite adequate or increased cardiac output.
- Preload — ventricular filling before contraction.
- Afterload — resistance the ventricle must overcome to eject blood.
- Cardiac output — blood pumped per minute; \( CO = HR \times SV \).
- Systemic vascular resistance — arterial tone/load contributing to blood pressure.
- Shock index — heart rate divided by systolic blood pressure; a screening clue, not a sole treatment trigger.
- Capillary refill — bedside sign of peripheral perfusion.
- Mixed venous or central venous oxygen saturation — surrogate of oxygen delivery-consumption balance.
- End-organ dysfunction — kidney injury, altered mentation, hepatocellular injury, or worsening acid-base state from hypoperfusion.
1.1.1.2 Must-know facts
- Normal blood pressure does not exclude shock if perfusion is poor.
- Hypotension with cold extremities and rising lactate is a treatment problem first, not a naming exercise.
- A common initial MAP target is at least 65 mm Hg, but patient-specific goals may differ.
- Urine output under 0.5 mL/kg/hr is a major perfusion warning sign in adults.
- Lactate clearance trend is more useful than a single isolated value.
- Norepinephrine is the usual first-line vasopressor for many distributive shock scenarios.
- Fluids help only if the patient is likely fluid responsive; excess fluid can worsen oxygenation and organ congestion.
- Cardiogenic shock often needs caution with fluids and consideration of inotropy or vasoactive support.
- Obstructive shock does not improve with escalating pressors alone if the obstruction is unaddressed.
- Poor perfusion can reduce renal and hepatic clearance, increasing drug accumulation risk.
Core content
1.1.1.3 Foundational recognition: what shock means for a pharmacist
A Explanation
The board-style conflict is usually this: Is this patient merely hypotensive, or are they in true shock requiring immediate pharmacologic support and perfusion monitoring? The rule that resolves the conflict is simple: choose the answer that recognizes inadequate tissue perfusion, not just a low blood pressure number. A patient with MAP 62 mm Hg plus confusion, oliguria, cool mottled skin, rising lactate, or worsening creatinine is in a different category than a stable patient with a transient low cuff reading.
WHY THIS IS TESTED: exam stems often hide the key clue in organ dysfunction rather than in the headline blood pressure. Pharmacist-level reasoning begins with identifying whether oxygen delivery is failing and whether drug initiation, titration, or escalation should occur now.
Think in terms of determinants: pressure, flow, and tissue delivery. Blood pressure reflects the interaction of cardiac output and vascular tone. Organ perfusion then depends on whether that pressure and flow actually reach microcirculation. This is why the exam rewards choosing a therapy that corrects the dominant problem: volume loss, pump failure, vasodilation, or obstruction. See Fig 1.
The most useful bedside pharmacist cues are: MAP trend, heart rate pattern, urine output, lactate trend, mental status, skin temperature/mottling, creatinine, transaminase changes, and whether vasoactive needs are increasing. A single lactate can mislead; beta-agonists, seizures, liver dysfunction, or severe adrenergic stress can elevate it. A single MAP can mislead too; a chronically hypertensive patient may need a higher pressure to perfuse kidneys or brain than another patient would.
Exam takeaway: Identify shock by combining pressure, perfusion, and organ dysfunction rather than relying on hypotension alone.
flowchart TD
A[Low MAP or concerning trend] --> B{Perfusion signs present?}
B -->|Yes| C[Check urine output, mentation, lactate, skin]
C --> D{End-organ dysfunction?}
D -->|Yes| E[Treat as shock and escalate monitoring]
D -->|No| F[Reassess volume status and hemodynamic trend]
B -->|No| G[Repeat assessment and verify measurement] B Worked example
A 68-year-old man in the medical ICU has pneumonia, type 2 diabetes, and stage 3 CKD. He received ceftriaxone 2 g IV daily and azithromycin 500 mg IV daily in the ED, plus 1.5 L crystalloid. His current vitals are BP 88/52 mm Hg, HR 118/min, RR 28/min, temperature 38.9°C, SpO2 94% on high-flow oxygen. Lactate is 4.1 mmol/L, creatinine increased from 1.5 to 2.1 mg/dL, urine output over 3 hours is 40 mL total. The distracting clue is a hemoglobin of 10.2 g/dL, which may tempt a transfusion-focused answer.
Identify task: determine the best next pharmacologic action and monitoring priority.
Extract key facts: hypotension, tachycardia, oliguria, rising creatinine, elevated lactate, infectious source, prior fluids but persistent instability. Hemoglobin is not the main discriminator here.
Apply rule: persistent hypotension plus organ hypoperfusion after initial fluid suggests shock requiring prompt vasoactive support while evaluating distributive physiology.
Eliminate distractors: transfusion is not supported by this hemoglobin; diuresis would worsen perfusion; waiting for another isolated lactate before acting delays therapy.
Verify: recommendation should focus on starting protocol-concordant vasopressor support, usually norepinephrine, while continuing source-directed care and reassessing MAP, urine output, and lactate trend.
C Exam trap
D Checkpoint
Question: A 72-year-old woman with coronary artery disease and chronic hypertension is receiving piperacillin/tazobactam 4.5 g IV every 6 hours for presumed intra-abdominal infection. BP is 96/58 mm Hg, HR 104/min, lactate 3.8 mmol/L, urine output 15 mL/hr for 4 hours, and she is newly confused. Which finding most strongly supports treating this as shock rather than isolated hypotension?
- HR 104/min
- Lactate 3.8 mmol/L with oliguria and new confusion
- Chronic hypertension history
- Receipt of broad-spectrum antibiotics
Answer: B.
- A: tempting because tachycardia often accompanies shock, but it is nonspecific and can occur with pain, fever, or anxiety.
- B: correct because multiple perfusion markers and organ dysfunction signs identify clinically important shock rather than a number alone.
- C: tempting because chronic hypertension affects MAP targets, but by itself it does not prove current perfusion failure.
- D: tempting because infection suggests septic shock, but antibiotics do not establish the hemodynamic diagnosis.
1.1.1.4 Foundational classification: distributive vs cardiogenic vs hypovolemic vs obstructive
A Explanation
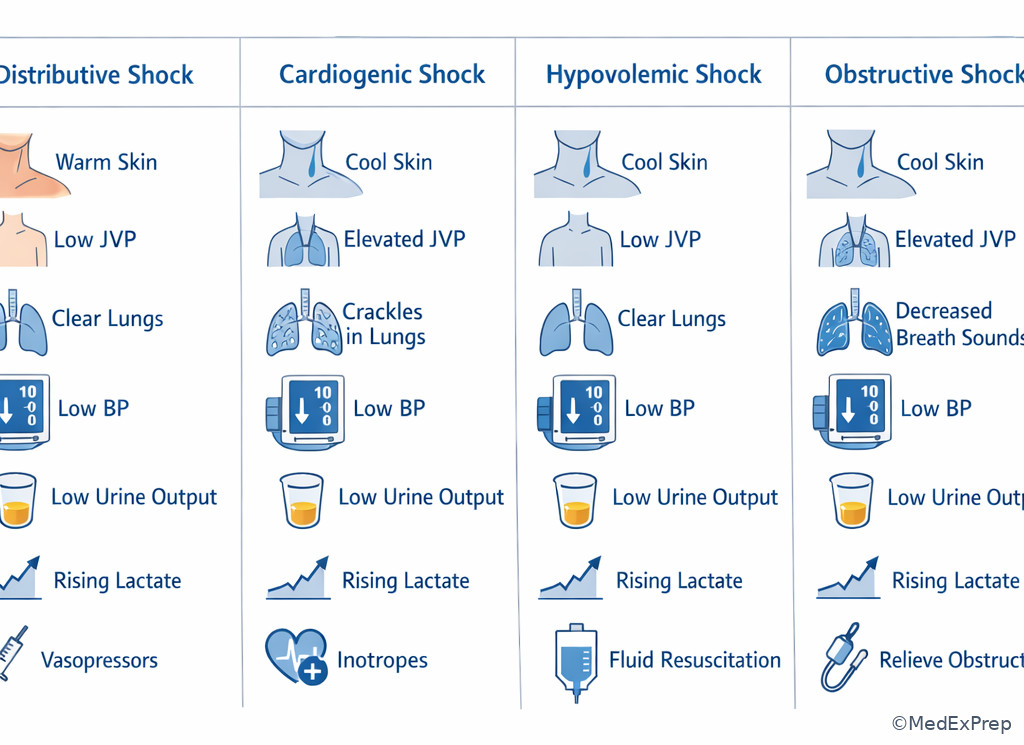
Once you recognize shock, the next conflict is: Which physiologic category best explains the bedside pattern, and which medication strategy fits that category? The resolving rule is to match temperature/perfusion clues, volume story, neck-vein or congestion findings, and likely mechanism. See Fig 2.
Distributive shock typically shows vasodilation: warm extremities early, wide pulse pressure, low SVR pattern, infection or inflammatory trigger, and need for vasopressor support when fluids are insufficient. Cardiogenic shock points toward pump failure: pulmonary congestion, cold extremities, rising filling pressures, low output physiology, myocardial injury or severe decompensated heart failure. Hypovolemic shock suggests decreased preload: hemorrhage, GI losses, third spacing, dry mucosa, flat neck veins, and improvement with volume if no major pump limitation exists. Obstructive shock reflects impaired filling or outflow: tamponade, massive pulmonary embolism, tension physiology; the exam clue is that pressure remains poor despite therapies that do not relieve the obstruction.
WHY THIS IS TESTED: the board wants to know whether you can reject therapies that are superficially reasonable but mechanistically mismatched. Large fluid boluses in cardiogenic shock, pressor-only escalation in untreated obstruction, and delayed vasopressors in distributive shock are classic misses.
For pharmacists, the practical distinction is medication selection and monitoring. Distributive shock usually brings norepinephrine early. Cardiogenic shock often raises inotrope-versus-pressor questions and fluid caution. Hypovolemia prioritizes appropriate resuscitative fluid or blood product support based on cause. Obstructive shock still may need temporary vasoactive support, but the key is recognizing that pharmacotherapy alone will not solve the primary problem.
Exam takeaway: Use bedside pattern recognition to match the dominant shock mechanism to the safest pharmacologic direction.
flowchart LR
A[Shock state] --> B{Warm or cold?}
B -->|Warm early| C[Distributive likely]
B -->|Cold clammy| D{Congestion or volume loss?}
D -->|Pulmonary edema JVD| E[Cardiogenic likely]
D -->|Bleeding losses dry exam| F[Hypovolemic likely]
A --> G{Obstruction clues?}
G -->|Tamponade PE tension| H[Obstructive likely] Exam takeaway: Visual pattern recognition of warm versus cold shock and congestion versus volume loss helps eliminate the wrong therapy quickly.
B Worked example
A 74-year-old woman with ischemic cardiomyopathy, atrial fibrillation, and chronic kidney disease is admitted after progressive dyspnea. She is receiving furosemide 80 mg IV twice daily at home-equivalent intensity, metoprolol succinate, and apixaban. In the ICU, BP is 82/54 mm Hg, HR 110/min, she is cool and clammy, has bibasilar crackles, elevated jugular venous pressure, lactate 3.2 mmol/L, and urine output 20 mL/hr. A distracting clue is a recent history of poor oral intake, which may tempt a fluid-bolus answer.
Identify task: choose the best pharmacologic direction.
Extract key facts: low pressure plus congestion plus cool extremities plus low urine output suggests low-output cardiogenic physiology, not simple hypovolemia.
Apply rule: when congestion and pump failure dominate, large empiric fluids are rejected; pharmacologic support should prioritize hemodynamic support appropriate to cardiogenic shock while the team evaluates definitive management.
Eliminate distractors: additional loop diuretic alone will not correct shock; large fluid bolus may worsen pulmonary edema; vasodilator therapy is unsafe with current hypotension.
Verify: recommendation should focus on collaborative hemodynamic support, often involving vasoactive/inotropic therapy guided by institutional protocol and bedside assessment.
C Exam trap
D Checkpoint
Question: A 63-year-old man on meropenem 1 g IV every 8 hours has BP 84/46 mm Hg, HR 122/min, warm flushed skin, bounding pulses, lactate 3.9 mmol/L, and diffuse pneumonia on imaging. Which shock pattern is most consistent with this presentation?
- Cardiogenic shock
- Hypovolemic shock
- Distributive shock
- Obstructive shock
Answer: C.
- A: tempting because lactate and hypotension occur in cardiogenic shock, but warm flushed skin and bounding pulses are not typical low-output clues.
- B: tempting because tachycardia and hypotension fit volume loss, but the warm vasodilated pattern and infection source favor distributive physiology.
- C: correct because infection plus vasodilated bedside findings strongly support distributive shock.
- D: tempting because severe instability can occur in obstructive shock, but no tamponade, PE, or tension pattern is given.
- The dominant medication in early distributive shock is usually ________. Answer: norepinephrine.
- True or False: pulmonary congestion makes a large empiric fluid bolus less attractive in shock. Answer: True.
- Name the 4 major shock categories. Answer: distributive, cardiogenic, hypovolemic, obstructive.
1.1.1.5 Application: perfusion endpoints and what to monitor first
A Explanation
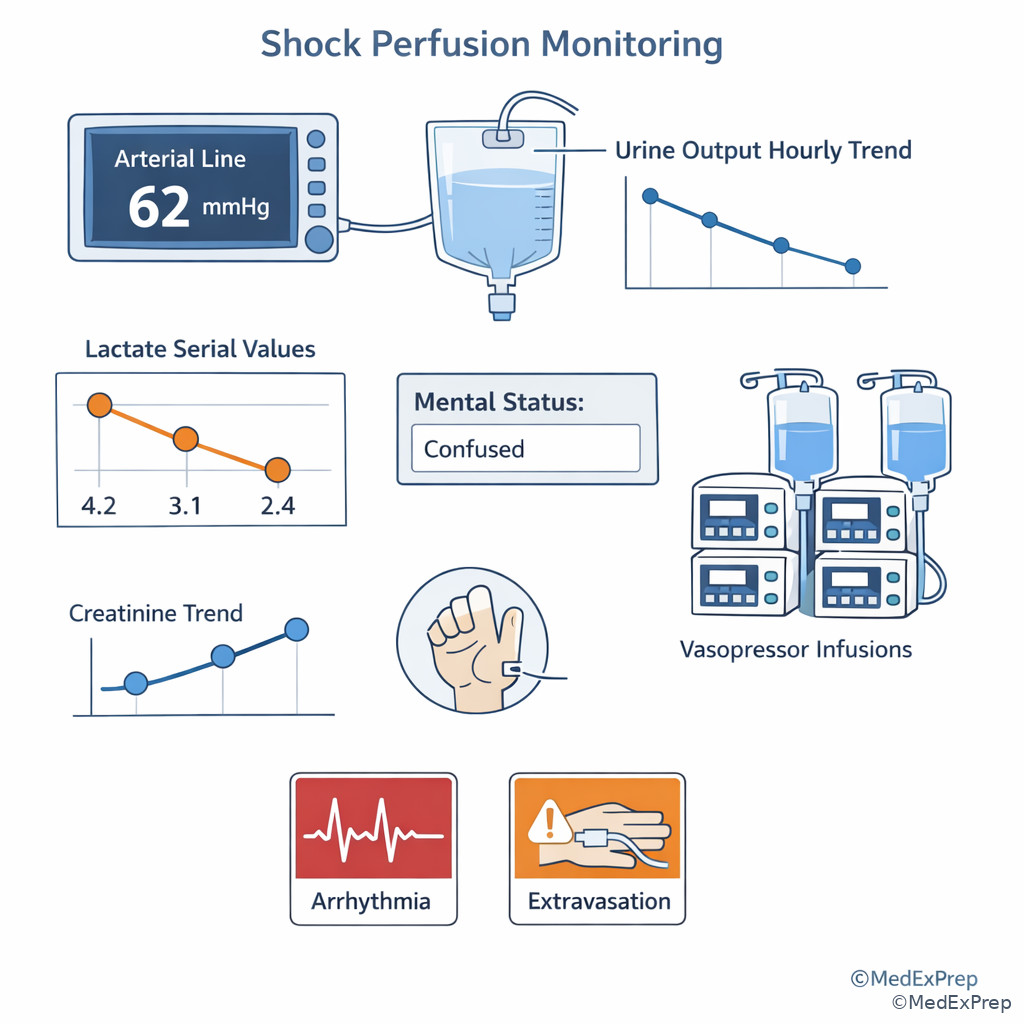
The decision conflict here is: Which endpoint should guide early pharmacist reassessment after fluid or vasoactive therapy? The resolving rule is to choose dynamic, clinically relevant perfusion endpoints rather than isolated numbers. MAP matters, but so do urine output, mentation, lactate trend, skin findings, and organ-function trajectory. See Fig 4.
WHY THIS IS TESTED: stems often offer a familiar number that is incomplete. For example, a lactate decrease is encouraging but does not override worsening urine output. A MAP of 65 mm Hg may still be inadequate in a patient with chronic hypertension, while a brief MAP below target may be tolerated if perfusion is clearly improving and vasopressor titration is in progress. The exam wants the most useful monitoring priority, not the most famous measurement.
Useful early targets include MAP at or above the current clinical goal, improving urine output, better mentation, and down-trending lactate when elevated initially. Capillary refill and peripheral perfusion can be helpful bedside adjuncts. Drug-related monitoring matters too: arrhythmias with inotropes or epinephrine, digital ischemia with high-dose vasopressors, worsening pulmonary edema after fluids, and extravasation risk with vasopressor infusions.
Remember that some markers lag. Serum creatinine rises later than perfusion loss. Lactate may remain elevated for reasons beyond global hypoperfusion. Therefore, the strongest reassessment answer often combines hemodynamic improvement plus organ function signal. See Fig 5 for a high-yield visual of the main endpoints.
Exam takeaway: Reassess therapy with MAP plus organ-perfusion signals rather than any single laboratory value.
flowchart TD
A[After fluids or vasoactive change] --> B[Check MAP against target]
B --> C[Check urine output and mentation]
C --> D[Trend lactate and renal function]
D --> E{Improving?}
E -->|Yes| F[Continue and monitor for toxicity]
E -->|No| G[Escalate reassessment and revise strategy] Exam takeaway: The best reassessment plan combines hemodynamic, urine output, neurologic, and laboratory trends in one view.
B Worked example
A 59-year-old man with alcoholic cirrhosis and hypertension is on norepinephrine 0.12 mcg/kg/min after presumed septic shock. Piperacillin/tazobactam 4.5 g IV every 6 hours has been started. Two hours later, MAP increased from 58 to 67 mm Hg, but urine output remains 10–15 mL/hr, lactate is unchanged at 5.0 mmol/L, and he is still lethargic. AST and ALT are mildly elevated from baseline. A distracting clue is improved heart rate, which may falsely reassure.
Identify task: determine whether resuscitation is adequate.
Extract key facts: MAP target reached, but multiple organ perfusion markers have not improved yet.
Apply rule: a pressure response alone does not confirm restored tissue perfusion.
Eliminate distractors: stopping reassessment because MAP is above 65 is premature; changing antibiotics solely due to unchanged lactate at 2 hours is not yet justified by this data alone.
Verify: continue active reassessment and communicate that the patient still has persistent hypoperfusion despite an improved MAP.
C Exam trap
D Checkpoint
Question: A 66-year-old woman receiving norepinephrine 0.08 mcg/kg/min and cefepime 2 g IV every 8 hours for suspected septic shock has improved MAP from 57 to 66 mm Hg over 90 minutes. Which additional parameter most strongly supports improved organ perfusion?
- HR decreases from 122 to 108/min
- Urine output increases from 10 mL/hr to 45 mL/hr
- Temperature rises from 38.2°C to 38.7°C
- WBC increases from 14,000 to 16,000/mm3
Answer: B.
- A: tempting because tachycardia often improves with stabilization, but heart rate alone is less direct than urine output for perfusion.
- B: correct because improved urine output is a strong early organ-perfusion endpoint in the right clinical context.
- C: tempting because temperature may track infection severity, but it does not confirm improved perfusion.
- D: tempting because infection markers matter, but WBC fluctuation is not an early hemodynamic success signal.
1.1.1.6 Application: fluids, vasopressors, and the first medication decision
A Explanation
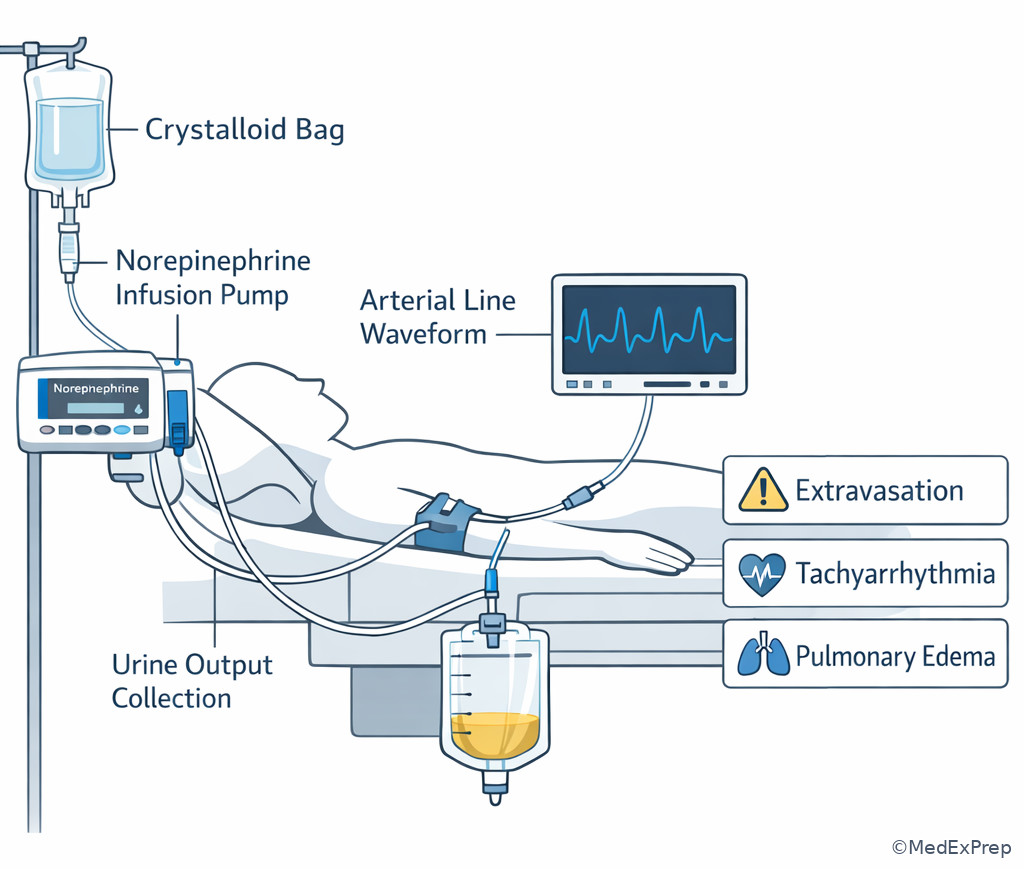
The classic exam conflict is: Should the pharmacist recommend more fluid, start vasopressor support, or reject both as the immediate answer? The single resolving rule is to identify the dominant physiology and whether delay in vasopressor support would worsen perfusion. In distributive shock with persistent hypotension after initial resuscitation, do not wait endlessly on additional fluid if perfusion remains poor; early norepinephrine is commonly favored. In cardiogenic shock or obvious congestion, additional empiric fluid becomes less attractive. In clear hypovolemia, volume replacement is central. In obstructive shock, pharmacotherapy is supportive but not definitive. See Fig 6.
WHY THIS IS TESTED: the most common wrong answer is usually the option that sounds broadly reasonable but is one step out of sequence for the exact patient. The exam may include a tempting-but-wrong “give another 2 liters now” answer in a patient already showing pulmonary edema or a “wait for central access before vasopressors” answer in a patient with clear ongoing shock.
Norepinephrine is generally the preferred first-line vasopressor in many adult distributive shock scenarios because it increases arterial tone with a favorable balance of efficacy and arrhythmia risk compared with some alternatives. Dopamine is a recurrent distractor because it sounds kidney-friendly or heart-rate-supportive; on boards, its arrhythmia liability and less favorable profile often make it inferior in many shock settings. Epinephrine can be appropriate in selected cases but may increase lactate and provoke tachyarrhythmias, creating interpretation traps. Vasopressin is typically an adjunct rather than a first single agent in many adult ICU scenarios.
Pharmacist reasoning must also include route, compatibility, concentration, extravasation risk, and rapid reassessment. Local ICU protocol may govern peripheral norepinephrine initiation, but exam logic generally favors not delaying pressor therapy solely for central-line placement when shock is ongoing and institutional practice supports peripheral initiation with monitoring.
Exam takeaway: Choose fluid, vasopressor, or escalation by matching the bedside pattern and rejecting sequence errors.
flowchart TD
A[Patient in shock] --> B{Obvious volume loss without congestion?}
B -->|Yes| C[Give appropriate fluid or blood product strategy]
B -->|No| D{Warm vasodilated pattern after initial fluid?}
D -->|Yes| E[Start norepinephrine and reassess]
D -->|No| F{Congestion low output pattern?}
F -->|Yes| G[Consider cardiogenic support strategy]
F -->|No| H[Evaluate for obstruction and escalate] Exam takeaway: Link bedside shock pattern to the correct infusion choice and the immediate monitoring priorities.
B Worked example
A 61-year-old man with COPD and hypertension presents with urosepsis. He received 2 L balanced crystalloid, cefepime 2 g IV every 8 hours, and vancomycin per protocol. BP remains 78/44 mm Hg, HR 126/min, temperature 39.1°C, lactate 5.3 mmol/L, urine output 5 mL in the last hour, and he has warm extremities. Chest exam is clear. A distracting clue is sinus tachycardia, which may tempt dopamine.
Identify task: pick the best next pharmacologic action.
Extract key facts: persistent hypotension despite initial fluid, warm vasodilatory pattern, infection source, severe hypoperfusion, no congestion clues.
Apply rule: start first-line vasopressor support, usually norepinephrine, rather than dopamine or more indiscriminate fluid.
Eliminate distractors: dopamine is tempting because of tachycardia and old “renal” myths, but arrhythmia risk and evidence profile make it less attractive; vasopressin alone is usually adjunctive; phenylephrine lacks the same broad first-line role.
Verify: norepinephrine with rapid reassessment of MAP, urine output, lactate, and source control trajectory is the best next pharmacologic move.
C Exam trap
D Checkpoint
Question: A 58-year-old woman with pyelonephritis is receiving cefepime 2 g IV every 8 hours. After 30 mL/kg crystalloid, BP remains 80/48 mm Hg, MAP 57 mm Hg, HR 120/min, lactate 4.6 mmol/L, urine output 8 mL/hr, and she has warm extremities without crackles. What is the most appropriate next pharmacologic action?
- Begin norepinephrine infusion per ICU protocol
- Give dopamine infusion because tachycardia suggests chronotropic support is needed
- Give furosemide 40 mg IV to improve urine output
- Delay vasoactive therapy until central venous access is placed regardless of local protocol
Answer: A.
- A: correct because persistent distributive shock after initial fluid favors early norepinephrine with close monitoring and protocol confirmation.
- B: tempting because dopamine may seem useful in hypotension with tachycardia, but arrhythmia risk and inferior first-line role make it wrong here.
- C: tempting because oliguria is present, but low urine output from shock is not fixed by forcing diuresis.
- D: tempting because central access is ideal, but delaying needed vasopressor support despite protocol-supported peripheral initiation is unsafe.
- The usual first-line vasopressor in many adult distributive shock cases is ________. Answer: norepinephrine.
- True or False: oliguria in shock should be treated first with loop diuretics. Answer: False.
- When crackles and elevated JVP accompany hypotension, repeated blind fluid boluses become more or less attractive? Answer: Less attractive.
1.1.1.7 Integration: organ dysfunction, PK/PD consequences, and medication safety in shock
A Explanation
The advanced conflict is: How does poor perfusion change medication safety and dosing, and which abnormality demands pharmacist clarification now? The resolving rule is to think beyond hemodynamics: shock alters absorption, distribution, metabolism, and elimination, often rapidly and unpredictably. This is where BCCCP questions become more pharmacy-specific.
WHY THIS IS TESTED: the exam commonly couples shock with a drug decision such as antimicrobial dosing, sedative accumulation, anticoagulant safety, or nephrotoxic combination risk. Learners who stop at hemodynamic classification miss the medication-management layer.
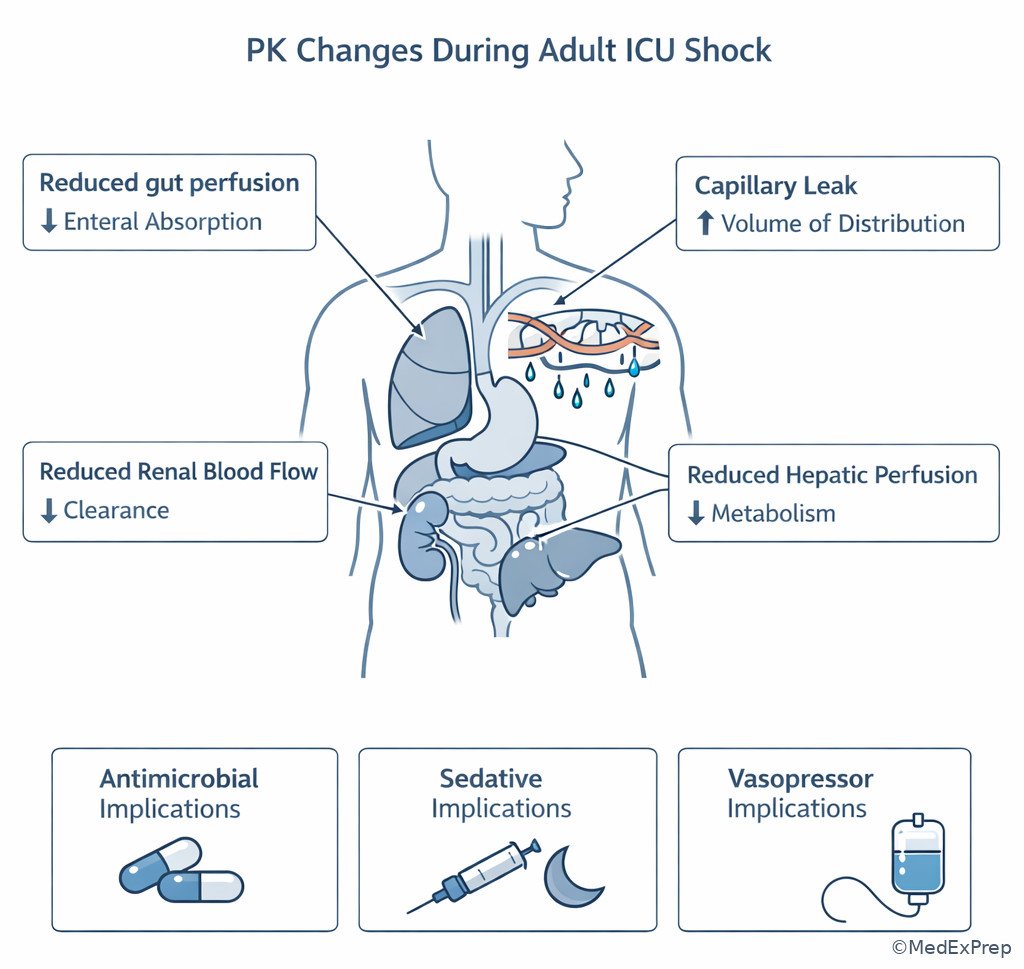
Renal hypoperfusion can lower clearance before serum creatinine fully reflects the change. Hepatic hypoperfusion and congestion may reduce metabolism, especially for high-extraction drugs. Gut hypoperfusion can reduce enteral absorption, making IV therapy preferable in unstable patients. Capillary leak and aggressive fluid resuscitation can increase apparent volume of distribution for hydrophilic drugs, potentially lowering early serum concentrations. Protein binding may also change in critical illness, complicating interpretation of total drug levels.
Practically, this means you must reassess dose, route, concentration, interaction profile, and toxicity monitoring. Nephrotoxic stacks become more dangerous during shock. Renally cleared antibiotics may need later dose adjustment as kidney function worsens or improves. Sedatives and opioids can accumulate unpredictably in hepatic or renal dysfunction. Vasopressor-related peripheral ischemia, arrhythmias, or extravasation are medication harms that can be more immediately testable than deep PK theory.
See Fig 3 for phenotype clues and remember the forward connection: upcoming sepsis/MOF content will expand these PK/PD shifts during inflammatory organ failure states.
Exam takeaway: Poor perfusion changes route reliability, drug distribution, clearance, and toxicity risk at the same time.
B Worked example
A 70-year-old man with septic shock is receiving norepinephrine 0.18 mcg/kg/min, vancomycin per pharmacy dosing protocol, and piperacillin/tazobactam 4.5 g IV every 6 hours. He also has type 2 diabetes, CKD stage 3b, and home lisinopril use. Over 12 hours, urine output declines from 35 mL/hr to 8 mL/hr, creatinine rises from 1.8 to 2.7 mg/dL, and lactate remains elevated. A distracting clue is that blood pressure has improved to MAP 66 mm Hg, which may hide the evolving drug safety issue.
Identify task: determine the highest-yield pharmacist action.
Extract key facts: renal perfusion remains poor or kidney injury is evolving despite acceptable MAP; nephrotoxic risk stack is present; drug clearance is changing.
Apply rule: hypoperfusion changes dose-adjustment logic and toxicity risk; medication reassessment must occur even when blood pressure looks better.
Eliminate distractors: maintaining all doses without reassessment ignores evolving AKI; changing antibiotics solely due to creatinine rise may be premature without infection data; oral conversion is inappropriate in ongoing shock.
Verify: the best action is to reassess renal-dose appropriateness, nephrotoxic burden, and monitoring plan immediately.
C Exam trap
D Checkpoint
Question: A 64-year-old man with shock is receiving vancomycin, piperacillin/tazobactam, and norepinephrine. Which development most strongly requires immediate pharmacist clarification because it can alter medication safety even if MAP is at target?
- Temperature decreases from 39.0°C to 38.2°C
- WBC decreases from 19,000 to 17,500/mm3
- Urine output falls to 0.2 mL/kg/hr with rising serum creatinine
- Heart rate decreases from 124 to 108/min
Answer: C.
- A: tempting because fever improvement can suggest response, but it does not directly change dose safety.
- B: tempting because infection labs matter, but modest WBC change is not the strongest immediate medication-safety trigger.
- C: correct because evolving AKI directly affects clearance, nephrotoxic risk, and dosing/monitoring strategy.
- D: tempting because improved heart rate may look reassuring, but it does not carry the same medication-risk implication as worsening renal perfusion.
1.1.1.8 Integration: choosing the best next pharmacologic action in mixed or unclear shock
A Explanation
The final integration problem is: What should you recommend when the shock state is mixed, evolving, or incompletely defined? The exam does not require you to act outside pharmacist scope by making every definitive diagnosis. The resolving rule is to recommend the safest protocol-concordant pharmacologic step with the highest likelihood of improving perfusion now, while explicitly calling for collaborative reassessment of the underlying cause.
WHY THIS IS TESTED: many stems are intentionally messy. A patient may have pneumonia and reduced ejection fraction, GI losses and sepsis, or chronic cirrhosis with distributive features. In these cases, the best answer is rarely “do everything” and rarely “wait for more data.” It is the option that addresses the immediate hemodynamic threat while avoiding a mechanism-specific harm.
In mixed vasodilatory and cardiogenic features, you may need pressure support first while avoiding excessive fluid. In possible obstructive physiology, temporary pressors may be appropriate, but the pharmacist should escalate that pharmacotherapy alone will not solve the problem. In unclear shock with severe hypotension and hypoperfusion, choose the intervention that protects perfusion now and can be titrated quickly while further evaluation proceeds. See Fig 6 again for the core decision tree.
This is also where board wording matters. If the answer option asks you to “independently diagnose tamponade” or “take the patient to surgery,” reject it as outside pharmacist framing. Prefer answers such as recommending vasopressor initiation, medication adjustment, emergent team notification, or escalation for collaborative evaluation.
Exam takeaway: In unclear or mixed shock, choose the safest pharmacologic bridge while escalating collaborative reassessment of the cause.
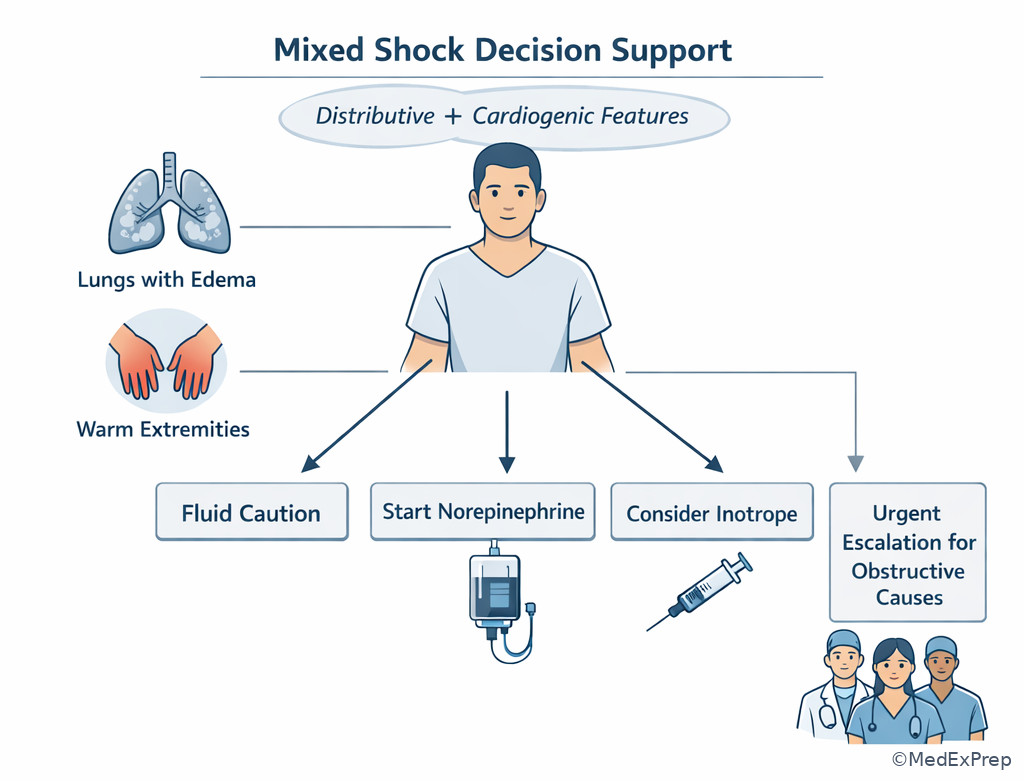
B Worked example
A 67-year-old man with severe HFrEF, diabetes, and pneumonia is in the ICU on ceftriaxone 2 g IV daily plus azithromycin 500 mg IV daily. BP is 76/42 mm Hg, HR 118/min, lactate 4.4 mmol/L, warm extremities are noted, but he also has bibasilar crackles and chronic lower-extremity edema. Urine output is 12 mL/hr. A distracting clue is chronic edema, which may cause an examinee to dismiss all fluid-related thinking, yet the immediate issue is perfusion failure.
Identify task: choose the best next pharmacologic action in mixed features.
Extract key facts: severe hypotension with organ hypoperfusion, infectious trigger suggesting vasodilation, but poor fluid tolerance due to HFrEF/congestion.
Apply rule: the safest bridge is early vasopressor support rather than a large additional fluid bolus; simultaneously communicate concern for mixed distributive/cardiogenic physiology and need for close reassessment.
Eliminate distractors: large fluid bolus risks worsening pulmonary edema; pure inotrope-first without pressure support may not address severe vasodilation; observation is unsafe.
Verify: norepinephrine-based support with collaborative evaluation of the mixed physiology is the best immediate pharmacist recommendation.
C Exam trap
D Checkpoint
Question: A 69-year-old woman with HFrEF and pneumonia is receiving cefepime 2 g IV every 8 hours. She has BP 78/45 mm Hg, lactate 4.2 mmol/L, urine output 10 mL/hr, warm extremities, and bibasilar crackles. Which is the best next pharmacologic recommendation within pharmacist scope?
- Recommend immediate norepinephrine initiation with close reassessment and fluid caution
- Recommend a 2-L crystalloid bolus because all shock should first receive more fluid
- Wait for echocardiography before recommending any hemodynamic medication
- Recommend phenylephrine first because it avoids beta activity entirely
Answer: A.
- A: correct because mixed vasodilatory and fluid-intolerant features favor a least-harm pressure-support strategy with collaborative reassessment.
- B: tempting because infection-related shock often begins with fluids, but congestion clues make a large blind bolus unsafe here.
- C: tempting because diagnostic clarification is desirable, but it should not delay treatment of active hypoperfusion.
- D: tempting because alpha-agonism may sound cleaner in hypotension, but phenylephrine is not the preferred first-line option in this scenario.
Exam Traps & Differentiators
| Looks similar | But isn’t | Single best discriminator | Pharmacist implication |
|---|---|---|---|
| Hypotension | Shock | Evidence of hypoperfusion or organ dysfunction | Escalate monitoring and pharmacologic support when perfusion fails |
| Warm septic patient | Pure hypovolemia | Warm extremities, vasodilated pattern, persistent hypotension after initial fluid | Norepinephrine usually outranks repeated blind boluses |
| Oliguria in shock | Need for diuretic | Low urine output with poor perfusion markers | Fix perfusion first; do not reflex to loop diuretics |
| MAP at goal | Resolved shock | Urine output, mentation, lactate, and renal function may still be worsening | Continue reassessment and dose safety review |
| Tachycardia in shock | Indication for dopamine | Distributive shock after fluids still favors norepinephrine in many cases | Avoid arrhythmia trap |
| Persistent instability | Reason to keep escalating pressors only | Obstructive clues or severe pump failure | Escalate for underlying cause; pharmacotherapy may only bridge |
If the stem says...
- “Warm extremities, bounding pulses, infection source” → think distributive physiology.
- “Crackles, elevated JVP, cool clammy skin” → think cardiogenic physiology and fluid caution.
- “Blood loss, GI losses, dry mucosa, empty-tank story” → think hypovolemic shock.
- “Sudden severe instability not explained by fluid/pump pattern” → think obstructive causes and escalate.
- “MAP improved but oliguria persists” → think incomplete resuscitation or ongoing organ hypoperfusion.
- “Improving BP with worsening creatinine” → think evolving PK change and medication safety review.
Tables
| Reference parameter | High-yield adult ICU target or clue | Why it matters in shock |
|---|---|---|
| MAP | Often at least 65 mm Hg initially | Common vasopressor target, but not sufficient alone |
| Urine output | At least 0.5 mL/kg/hr often used as a bedside goal | Early organ perfusion marker |
| Lactate | Trend down over time rather than rely on one value | Supports perfusion assessment and response tracking |
| Mental status | Improving alertness is favorable | Brain perfusion/end-organ signal |
| Skin/capillary refill | Warm vs cold and prolonged refill can help classify pattern | Rapid bedside adjunct to hemodynamic assessment |
| Creatinine trend | Rising values may lag but still matter | Signals evolving kidney injury and dose safety changes |
| Pressor requirement | Escalating dose requirement is a red flag | Suggests unresolved shock or incorrect strategy |
| Shock type | Typical bedside clues | Medication direction | Board trap to reject |
|---|---|---|---|
| Distributive | Warm skin early, infection/inflammation, vasodilated pattern | Norepinephrine often first-line after initial fluid | Dopamine first because tachycardia is present |
| Cardiogenic | Cool clammy, crackles, JVP elevation, low output | Fluid caution; consider vasoactive/inotropic support collaboratively | Large fluid bolus despite congestion |
| Hypovolemic | Loss history, dry exam, reduced preload clues | Resuscitative fluid or blood product strategy based on cause | Pressor-only strategy without volume replacement |
| Obstructive | Tamponade/PE/tension clues, mismatch to standard patterns | Temporary support plus urgent escalation for cause-specific management | Escalating pressors as definitive solution |
| Differential situation | Tempting interpretation | Correct interpretation | Discriminator |
|---|---|---|---|
| MAP 66, oliguria persists | Shock resolved | Perfusion may still be inadequate | Urine output and organ markers remain abnormal |
| Lactate elevated after epinephrine | Always worsening shock | Could partly reflect catecholamine effect | Interpret with overall perfusion picture |
| Shock with rising creatinine | Only a nephrology issue | Immediate medication-dose and toxicity issue | Drug clearance can change before full stabilization |
| Hypotension in HFrEF with infection | No vasoactive therapy until diagnosis is perfect | Least-harm bridge therapy should not be delayed | Profound hypoperfusion requires timely support |
| Persistent hypotension after initial fluids | Repeat the same bolus strategy automatically | Re-evaluate physiology and pressor need | Response to prior fluid and congestion clues |
| Medication issue during shock | Mechanism | Pharmacist monitoring priority |
|---|---|---|
| Reduced enteral absorption | Gut hypoperfusion | Consider IV route for critical therapies |
| Hydrophilic drug underexposure early | Capillary leak and increased volume of distribution | Ensure adequate loading where appropriate |
| Renally cleared drug accumulation | Reduced renal blood flow/AKI | Adjust dose and frequency; monitor levels if available |
| Hepatic metabolism reduction | Liver hypoperfusion or congestion | Watch for sedative/opioid accumulation |
| Vasopressor toxicity | Alpha/beta adrenergic effects and infusion risk | Monitor rhythm, ischemia, and IV site |
Algorithm / Approach
Rapid Review
- Shock vs hypotension → organ hypoperfusion separates them.
- Distributive shock → warm vasodilated pattern points toward norepinephrine after initial fluid.
- Cardiogenic shock → congestion plus cold skin argues against blind fluid loading.
- Hypovolemic shock → loss history and empty-tank clues favor volume replacement.
- Obstructive shock → pressors may bridge, but they do not fix the obstruction.
- MAP target → useful starting goal, not a complete resuscitation endpoint.
- Urine output → strongest simple bedside organ-perfusion trend to follow early.
- Lactate → trend matters more than one isolated value.
- Dopamine trap → tachycardia does not make it first-line in distributive shock.
- Oliguria in shock → do not reflex to diuretics before fixing perfusion.
- Improved BP with rising creatinine → think changing clearance and drug toxicity risk.
- Mixed shock → choose least-harm bridge therapy while escalating evaluation.
- Enteral route in unstable shock → may be unreliable due to gut hypoperfusion.
- Hydrophilic drugs in capillary leak → early underexposure risk can occur despite later accumulation concerns.
Self-check quiz
1.1.1.9 Question 1
A 62-year-old man in the ICU is receiving ceftriaxone 2 g IV every 24 hours for pneumonia. BP is 94/56 mm Hg, HR 108/min, urine output is 12 mL/hr, lactate is 4.0 mmol/L, and he is newly confused. Which finding most strongly indicates shock rather than isolated hypotension?
- Heart rate 108/min
- Urine output 12 mL/hr with new confusion
- Receipt of ceftriaxone
- Temperature 38.4°C
1.1.1.10 Question 2
A 57-year-old woman receives piperacillin/tazobactam 4.5 g IV every 6 hours for intra-abdominal infection. After initial fluid resuscitation, she remains hypotensive with MAP 56 mm Hg, warm extremities, and lactate 4.8 mmol/L. Which vasoactive agent is the most appropriate first-line choice in many adult distributive shock scenarios?
- Norepinephrine infusion
- Dopamine infusion
- Phenylephrine infusion
- Vasopressin infusion as sole initial agent
1.1.1.11 Question 3
A 71-year-old man with HFrEF, CAD, and CKD is receiving cefepime 2 g IV every 8 hours for pneumonia. BP is 82/50 mm Hg, HR 112/min, he is cool and clammy, has bibasilar crackles, elevated JVP, lactate 3.6 mmol/L, and urine output 18 mL/hr. Which is the best next pharmacologic recommendation?
- Give 2 L balanced crystalloid rapidly
- Recommend hemodynamic support with fluid caution for likely cardiogenic physiology
- Administer furosemide 80 mg IV immediately as sole therapy
- Delay all hemodynamic medications until lactate is repeated in 6 hours
1.1.1.12 Question 4
A 60-year-old woman with septic shock is receiving norepinephrine 0.1 mcg/kg/min and meropenem 1 g IV every 8 hours. MAP improved from 58 to 67 mm Hg over 2 hours. Which additional finding best supports improved organ perfusion?
- Urine output increases from 8 mL/hr to 42 mL/hr
- WBC count increases from 13,000 to 15,000/mm3
- Temperature increases from 38.1°C to 38.6°C
- Heart rate changes from 118/min to 112/min
1.1.1.13 Question 5
A 65-year-old man with urosepsis receives vancomycin per protocol and cefepime 2 g IV every 8 hours. After 30 mL/kg crystalloid, BP remains 78/46 mm Hg, MAP 57 mm Hg, lactate 5.1 mmol/L, urine output 6 mL/hr, and extremities are warm without crackles. Which option is the most appropriate next pharmacologic action?
- Start norepinephrine per protocol
- Start dopamine because tachycardia is present
- Give furosemide 40 mg IV for oliguria
- Wait for central line placement before any vasopressor despite protocol allowances
1.1.1.14 Question 6
A 68-year-old woman with septic shock, type 2 diabetes, and CKD is receiving norepinephrine 0.14 mcg/kg/min, piperacillin/tazobactam 4.5 g IV every 6 hours, and vancomycin per pharmacy dosing. MAP is 66 mm Hg, but urine output fell from 35 mL/hr to 9 mL/hr and creatinine rose from 1.4 to 2.3 mg/dL over 12 hours. Which pharmacist action is most appropriate?
- Continue all current medication doses because MAP is at goal
- Reassess renal-dose appropriateness and nephrotoxic burden immediately
- Change norepinephrine to dopamine to improve renal perfusion
- Convert antibiotics to enteral therapy because blood pressure has improved
1.1.1.15 Question 7
A 73-year-old man with pneumonia, HFrEF, and chronic edema is receiving ceftriaxone 2 g IV daily plus azithromycin 500 mg IV daily. BP is 76/44 mm Hg, lactate 4.5 mmol/L, urine output 10 mL/hr, extremities are warm, and bibasilar crackles are present. Which is the best next pharmacologic recommendation within pharmacist scope?
- Recommend norepinephrine initiation with cautious fluid strategy and close reassessment
- Recommend a mandatory 2-L crystalloid bolus before any vasoactive therapy
- Recommend phenylephrine as preferred first-line agent because beta activity should always be avoided in HFrEF
- Withhold recommendations until echocardiography definitively separates distributive from cardiogenic shock
1.1.1.16 Question 8
A 64-year-old man is receiving epinephrine infusion for refractory shock, cefepime 2 g IV every 8 hours, and hydrocortisone 50 mg IV every 6 hours. Two hours later, MAP is modestly improved, heart rate is 128/min, lactate increased from 4.2 to 5.0 mmol/L, urine output remains 28 mL/hr, and mentation is slightly improved. Which interpretation is most appropriate?
- The lactate rise proves the patient is worsening and all therapy is failing
- The lactate rise may reflect epinephrine effect, so overall perfusion context must be assessed
- The improved mentation proves shock is fully resolved
- The best next action is to add furosemide because urine output is not yet normal
Answer key
1.1.1.17 Question 1 Answer: B
A. Heart rate 108/min: tempting because tachycardia commonly accompanies shock and can signal physiologic stress. It is incorrect for this question because tachycardia is nonspecific and can result from fever, pain, anxiety, or hypovolemia without confirmed end-organ hypoperfusion. Single discriminator: it does not directly demonstrate organ dysfunction. Source: DiPiro; SCCM/critical care hemodynamic practice principles.
B. Urine output 12 mL/hr with new confusion: tempting because it seems “too obvious,” but that is exactly why it is correct. It is correct because oliguria plus altered mentation are direct end-organ perfusion abnormalities, making shock more likely than isolated low pressure alone. Single discriminator: multiple organ perfusion markers are abnormal. Source: ACCP/critical care texts; DiPiro.
C. Receipt of ceftriaxone: tempting because infection treatment suggests sepsis, and sepsis can progress to shock. It is incorrect because the presence of an antibiotic does not prove current hemodynamic insufficiency. Single discriminator: medication context does not replace perfusion data. Source: DiPiro.
D. Temperature 38.4°C: tempting because fever supports infection as a trigger. It is incorrect because fever indicates inflammatory/infectious stress, not shock by itself. Single discriminator: temperature does not establish organ hypoperfusion. Source: DiPiro.
1.1.1.18 Question 2 Answer: A
A. Norepinephrine infusion: tempting because it is the familiar guideline answer, and it is correct here for that reason. PK/PD-wise, norepinephrine increases vascular tone effectively in vasodilatory shock with a commonly preferred first-line profile. Single discriminator: persistent warm distributive shock after initial fluid. Source: Surviving Sepsis Campaign; DiPiro; Lexicomp.
B. Dopamine infusion: tempting because its beta activity may seem useful when heart rate or cardiac output is a concern. It is incorrect because, for many adult distributive shock scenarios, its higher arrhythmia risk and less favorable evidence profile make it inferior to norepinephrine. Single discriminator: distributive shock after fluids does not become a dopamine indication simply because tachycardia exists. Source: Surviving Sepsis Campaign; Lexicomp.
C. Phenylephrine infusion: tempting because pure alpha agonism sounds appealing for low pressure. It is incorrect because phenylephrine is not typically the preferred first-line vasopressor in this scenario. Single discriminator: it lacks the same standard first-line role as norepinephrine in adult distributive shock. Source: DiPiro; guideline summaries.
D. Vasopressin infusion as sole initial agent: tempting because vasopressin is used in shock and can reduce catecholamine dose requirements. It is incorrect because it is more commonly an adjunct than the sole initial first-line agent. Single discriminator: first-line initiation role belongs more often to norepinephrine. Source: Surviving Sepsis Campaign; Lexicomp.
1.1.1.19 Question 3 Answer: B
A. Give 2 L balanced crystalloid rapidly: tempting because hypotension and low urine output often trigger a volume reflex. It is incorrect because crackles, elevated JVP, cool skin, and HFrEF/low-output clues suggest cardiogenic physiology with poor fluid tolerance. Single discriminator: congestion is present. Source: DiPiro; ACCP critical care references.
B. Recommend hemodynamic support with fluid caution for likely cardiogenic physiology: tempting because it seems less concrete than a specific drug name, yet it is correct because the question asks for the best recommendation within pharmacist scope. PK/PD-wise, cardiogenic shock reflects inadequate forward flow; the correct pharmacologic direction avoids fluid overload and supports perfusion collaboratively. Single discriminator: congestion plus low-output signs. Source: DiPiro; Lexicomp for agent properties.
C. Administer furosemide 80 mg IV immediately as sole therapy: tempting because pulmonary congestion is present. It is incorrect because diuresis alone does not treat active shock with hypotension and hypoperfusion. Single discriminator: the patient is in shock, not isolated volume overload. Source: DiPiro.
D. Delay all hemodynamic medications until lactate is repeated in 6 hours: tempting because lactate trend is useful. It is incorrect because severe instability should not wait for delayed confirmation. Single discriminator: active hypoperfusion is already documented. Source: Critical care practice standards; DiPiro.
1.1.1.20 Question 4 Answer: A
A. Urine output increases from 8 mL/hr to 42 mL/hr: tempting because it appears like a straightforward bedside metric, and it is correct because improved urine output is a direct early organ-perfusion signal. Single discriminator: it reflects kidney perfusion response, not just systemic pressure. Source: DiPiro; critical care monitoring principles.
B. WBC count increases from 13,000 to 15,000/mm3: tempting because infection severity matters. It is incorrect because WBC trend is not the best near-term perfusion endpoint after a hemodynamic intervention. Single discriminator: it does not directly measure perfusion response. Source: DiPiro.
C. Temperature increases from 38.1°C to 38.6°C: tempting because infection activity is relevant. It is incorrect because fever trend does not establish hemodynamic success or failure. Single discriminator: temperature is not a preferred early perfusion endpoint. Source: DiPiro.
D. Heart rate changes from 118/min to 112/min: tempting because improving tachycardia can look reassuring. It is incorrect because heart rate is less specific than urine output for improved organ perfusion. Single discriminator: it is supportive at best, not the strongest endpoint. Source: ACCP critical care references.
1.1.1.21 Question 5 Answer: A
A. Start norepinephrine per protocol: tempting because it is the standard answer, and it is correct because the patient has persistent distributive-appearing shock after initial fluid with severe hypoperfusion. PK/PD-wise, norepinephrine improves arterial tone and MAP effectively in this setting. Single discriminator: warm extremities and persistent hypotension after 30 mL/kg without crackles. Source: Surviving Sepsis Campaign; Lexicomp; DiPiro.
B. Start dopamine because tachycardia is present: tempting because learners may think a beta-active pressor fits hypotension with low urine output. It is incorrect because dopamine is not preferred first-line in many adult distributive shock cases due to arrhythmia risk. Single discriminator: distributive shock physiology still favors norepinephrine. Source: Surviving Sepsis Campaign; Lexicomp.
C. Give furosemide 40 mg IV for oliguria: tempting because urine output is low. It is incorrect because oliguria from active shock reflects underperfusion, not a need for forced diuresis. Single discriminator: MAP is 57 mm Hg with lactate 5.1 mmol/L. Source: DiPiro.
D. Wait for central line placement before any vasopressor despite protocol allowances: tempting because central access is ideal for vasopressor administration. It is incorrect because needed pressor support should not be delayed if local ICU protocol allows monitored peripheral initiation. Single discriminator: ongoing severe hypoperfusion makes delay unsafe. Source: ASHP/Lexicomp administration guidance; local protocol note applies.
1.1.1.22 Question 6 Answer: B
A. Continue all current medication doses because MAP is at goal: tempting because learners stop once a pressure target is reached. It is incorrect because renal function is worsening, so clearance and nephrotoxic risk have changed despite acceptable MAP. Single discriminator: urine output fell and creatinine rose. Source: DiPiro; Lexicomp renal dosing guidance.
B. Reassess renal-dose appropriateness and nephrotoxic burden immediately: tempting because it adds work beyond hemodynamics, and it is correct for exactly that reason. PK-wise, shock-related AKI alters elimination of renally cleared drugs and magnifies nephrotoxicity risk. Single discriminator: evolving oliguria and creatinine rise. Source: Lexicomp; AHFS; DiPiro.
C. Change norepinephrine to dopamine to improve renal perfusion: tempting because of outdated renal-dose dopamine concepts and the desire to “help the kidneys.” It is incorrect because dopamine is not recommended for renal protection and brings arrhythmia risk. Single discriminator: no evidence-based renal rescue role justifies the switch. Source: DiPiro; guideline-based vasopressor recommendations.
D. Convert antibiotics to enteral therapy because blood pressure has improved: tempting because step-down thinking can emerge once MAP improves. It is incorrect because shock remains clinically significant and enteral absorption may still be unreliable during unstable perfusion. Single discriminator: ongoing oliguria/AKI indicates instability. Source: DiPiro; Lexicomp.
1.1.1.23 Question 7 Answer: A
A. Recommend norepinephrine initiation with cautious fluid strategy and close reassessment: tempting because it treats the immediate threat without claiming full diagnostic certainty, and it is correct because the patient has mixed distributive and fluid-intolerant features. This is the least-harm bridge therapy within pharmacist scope. Single discriminator: profound hypoperfusion plus warm extremities plus crackles. Source: Surviving Sepsis Campaign; DiPiro.
B. Recommend a mandatory 2-L crystalloid bolus before any vasoactive therapy: tempting because infection-related shock often begins with fluids. It is incorrect because fixed extra volume is unsafe when crackles and chronic HFrEF signal poor fluid tolerance. Single discriminator: pulmonary congestion clues. Source: DiPiro.
C. Recommend phenylephrine as preferred first-line agent because beta activity should always be avoided in HFrEF: tempting because it sounds tailored to heart failure. It is incorrect because “always avoid beta activity” is an overgeneralization and phenylephrine is not the preferred first-line answer here. Single discriminator: mixed vasodilatory shock still favors norepinephrine-based support. Source: Lexicomp; DiPiro.
D. Withhold recommendations until echocardiography definitively separates distributive from cardiogenic shock: tempting because diagnostic clarity is important. It is incorrect because active hypoperfusion should not wait for perfect diagnostic sorting. Single discriminator: lactate 4.5 mmol/L with oliguria and severe hypotension. Source: Critical care practice principles; DiPiro.
1.1.1.24 Question 8 Answer: B
A. The lactate rise proves the patient is worsening and all therapy is failing: tempting because lactate is a famous shock marker. It is incorrect because epinephrine can increase lactate independent of worsening global perfusion, so interpretation must be contextual. Single discriminator: epinephrine infusion is present. Source: DiPiro; critical care pharmacology references.
B. The lactate rise may reflect epinephrine effect, so overall perfusion context must be assessed: tempting because it requires nuanced interpretation, and it is correct because perfusion markers must be integrated rather than isolated. Slightly improved MAP and mentation argue against using a single lactate value as absolute proof of deterioration. Single discriminator: catecholamine-related lactate effect is plausible here. Source: DiPiro; Lexicomp epinephrine information.
C. The improved mentation proves shock is fully resolved: tempting because neurologic improvement is encouraging. It is incorrect because one improving endpoint does not prove full resolution, especially with persistent abnormalities elsewhere. Single discriminator: urine output is still limited and lactate interpretation remains unresolved. Source: DiPiro.
D. The best next action is to add furosemide because urine output is not yet normal: tempting because urine output remains below ideal. It is incorrect because shock-related oliguria is not corrected by reflex diuresis without a volume-overload rationale. Single discriminator: ongoing shock context. Source: DiPiro.
Keep going with the full BCCCP Prep Course (BCCCP)
You just studied the way members do, in the same lesson interface. Full access unlocks every lesson, the question bank and flashcards for a full year.
One payment · 1 year of access · No auto-renewal